
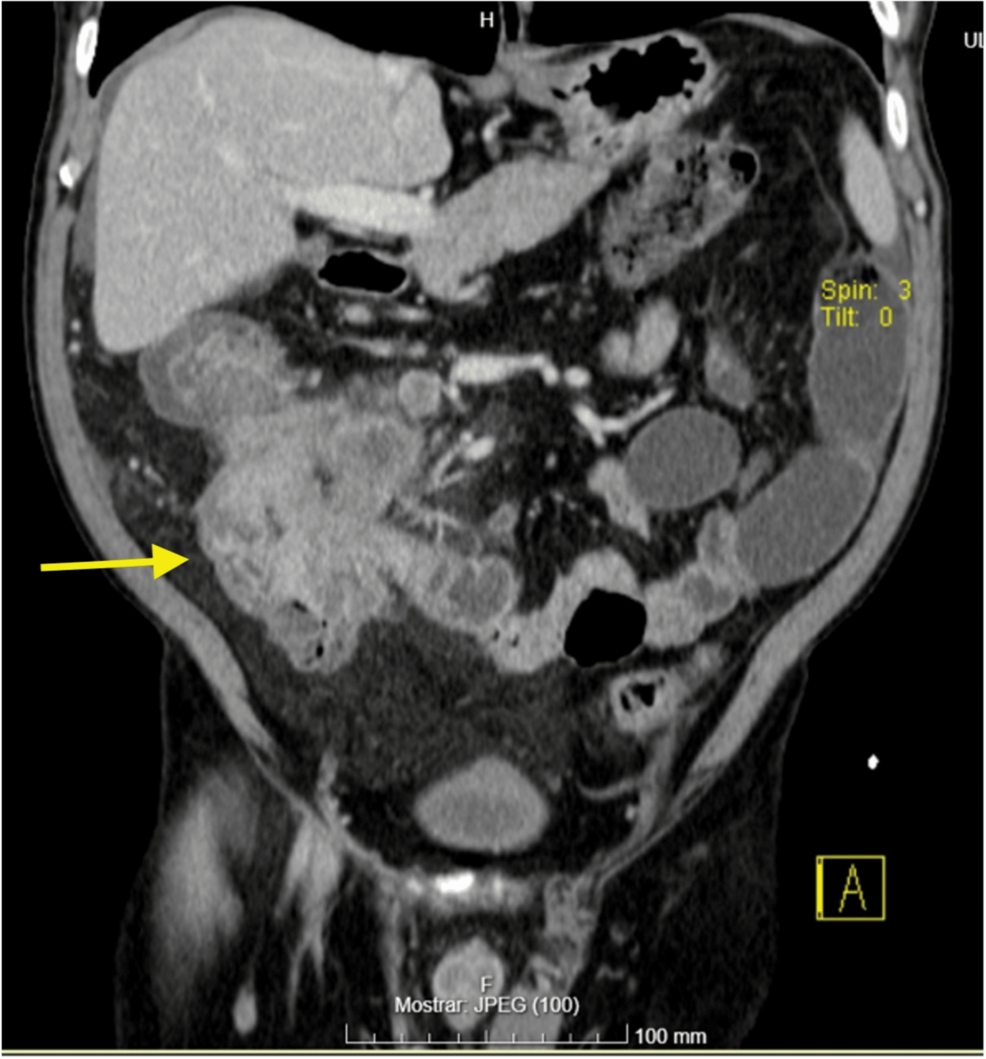
A 59-year-old man presented to an emergency department with a two-week history of abdominal pain, weight loss, and subocclusive symptoms, ultimately diagnosed with a perforated, poorly differentiated large-cell neuroendocrine carcinoma of the colon with peritoneal implants.
Colonic neuroendocrine carcinomas are rare, highly aggressive neoplasms that account for a fraction of colorectal malignancies. Because these tumors are typically non-functional, they frequently evade early detection, leading to advanced-stage presentation and emergency surgical complications like bowel perforation.
Contraindications Prohibit Certain Medical or Surgical Interventions
- Contraindications: Conditions or patient states—such as severe sepsis or hemodynamic instability—that prohibit a specific medical or surgical intervention, like sewing a bowel back together during an emergency.
Emergency Surgery and Pathological Findings for the Ascending Colon Mass
When the patient arrived at the hospital, diagnostic imaging revealed marked irregular thickening of the ascending colon extending to the hepatic flexure. A contrast-enhanced computed tomography scan showed a 4 cm localized abscess, small-volume ascites, and upstream small bowel dilation reaching 44 mm in caliber. Given the acute abdomen and systemic inflammatory response, clinicians performed an urgent exploratory laparotomy.
During the procedure, the patient required intraoperative vasopressor support due to hemodynamic instability. Surgeons identified a large obstructive neoplasm of the right colon with localized perforation, a right upper quadrant abscess, and widespread peritoneal implants. To achieve source control and establish a definitive diagnosis, a right hemicolectomy was performed. Because of active infection and instability, primary anastomosis—connecting the remaining ends of the intestine—was avoided in favor of an end ileostomy and a colonic mucous fistula.
Histological Distinction Between Neuroendocrine Carcinomas and NET G3
Postoperative analysis of the 9 cm resected specimen established the definitive diagnosis. Histopathology demonstrated a poorly differentiated large-cell neuroendocrine carcinoma with frequent mitotic figures and apoptotic bodies. Immunohistochemical staining showed strong diffuse positivity for CK8/18 and focal positivity for synaptophysin, while being negative for chromogranin A and CD56. The Ki-67 proliferation index reached 90%, with a mitotic count of 34 per 10 high-power fields.
Pathologists emphasize that a high Ki-67 index alone does not differentiate poorly differentiated neuroendocrine carcinomas from well-differentiated neuroendocrine tumors grade 3. Tumor morphology remains the critical diagnostic factor. Eighteen of 19 regional lymph nodes contained metastatic deposits, and a harvested peritoneal implant confirmed stage IVC disease. Following an uneventful recovery from the initial resection, the patient underwent successful restoration of intestinal continuity on postoperative day 31 before relocating abroad.
References
- Perforated Poorly Differentiated Large-Cell Neuroendocrine Carcinoma of the Colon With Peritoneal Implants: A Case Report.
- World Health Organization classification of tumours: digestive system tumours (6th edition).
- American Joint Committee on Cancer (AJCC) Cancer Staging Manual (8th edition).
