
Histopathological Overlap and the Modern Classification of Phyllodes Tumors
Phyllodes tumors of the breast are rare fibroepithelial growths that make up about 0.3% to 1% of all breast neoplasms and 2.5% of fibroepithelial lesions, whereas fibroadenomas account for the remaining 97.5%. These biphasic neoplasms consist of both neoplastic stromal components and a non-neoplastic epithelial component. Their hallmark microscopic characteristic is a leaf-like, intracanalicular structure featuring stromal projections that create cleft-like cavities enclosed by a double layer of epithelium. The World Health Organization in 2003 classified these tumors as benign, borderline, and malignant.
Global epidemiological data indicates that these neoplasms primarily affect women aged 35 to 55, with a peak incidence between 40 and 50 years and an average age at diagnosis of 45 years. These tumors can occur at any age, affecting patients from the prepubertal range to the elderly. Phyllodes tumors represent 0.3% to 1.0% of all primary breast neoplasms and 2% to 3% of fibroepithelial lesions in Western countries, with an estimated annual incidence of 2.1 cases per million women.
Diagnostic Limitations of Imaging and Core Needle Biopsy
Clinically, these tumors typically present as a palpable, painless breast mass. Phyllodes tumors originate from the intralobular and periductal stroma of the breast, probably in the terminal duct lobular unit. Unlike breast carcinoma, they belong to the group of fibroepithelial lesions.
Preoperative detection via imaging presents significant challenges. Mammographic evaluation typically reveals dense, round or oval masses with lobulations and margins that are either well-defined or partially obscured. Ultrasonographic findings generally show a solid, hypoechoic oval lesion with margins that are either well-demarcated or slightly blurred, while roughly half exhibit lobulation and frequently display posterior acoustic enhancement. On MRI evaluations, these growths manifest as oval or round lobulated nodules featuring sharp borders and reduced signal intensity on T1-weighted sequences.
Core needle biopsy is a tool for managing fibroepithelial lesions. The investigation concluded that CNB has restricted diagnostic precision for PTs, underscoring the necessity for physicians to combine CNB outcomes with histological, clinical, and imaging information to achieve a better diagnosis.
Historical Roots and Pathophysiological Context
Historical documentation traces the classification of these lesions across centuries. The tumor was first described in 1774 as a type of giant fibroadenoma, and in 1838, it was named “cystosarcoma phyllodes” by the German Johannes Müller. The World Health Organization (WHO) formally accepted this nomenclature in 1982 by labeling it a phyllodes tumor, followed by its 2003 categorization into benign, borderline, and malignant variants. Virchow characterized this tumor as having limited malignancy, capable of metastasizing in 1867, while Cooper and Ackerman confirmed the malignant potential of these neoplasms in 1943.
Etiological factors remain largely undefined, though genetic predispositions appear in patients with Li-Fraumeni syndrome and occasional mother-daughter pairs. The somatic p.R337H mutation was detected in 5.4% of subjects examined in a retrospective Brazilian investigation. Within a group of North American patients diagnosed with phyllodes tumors, genomic screening via a multi-cancer panel revealed a 7.7% rate of pathogenic or likely pathogenic germline mutations. Rare cases in men are often associated with gynecomastia, suggesting a role for hormonal imbalance. Latina, Hispanic, and Asian women have a higher incidence of the disease, with Asian women being diagnosed with phyllodes tumors at a younger age compared to Caucasians.
Current Diagnostic and Treatment Challenges
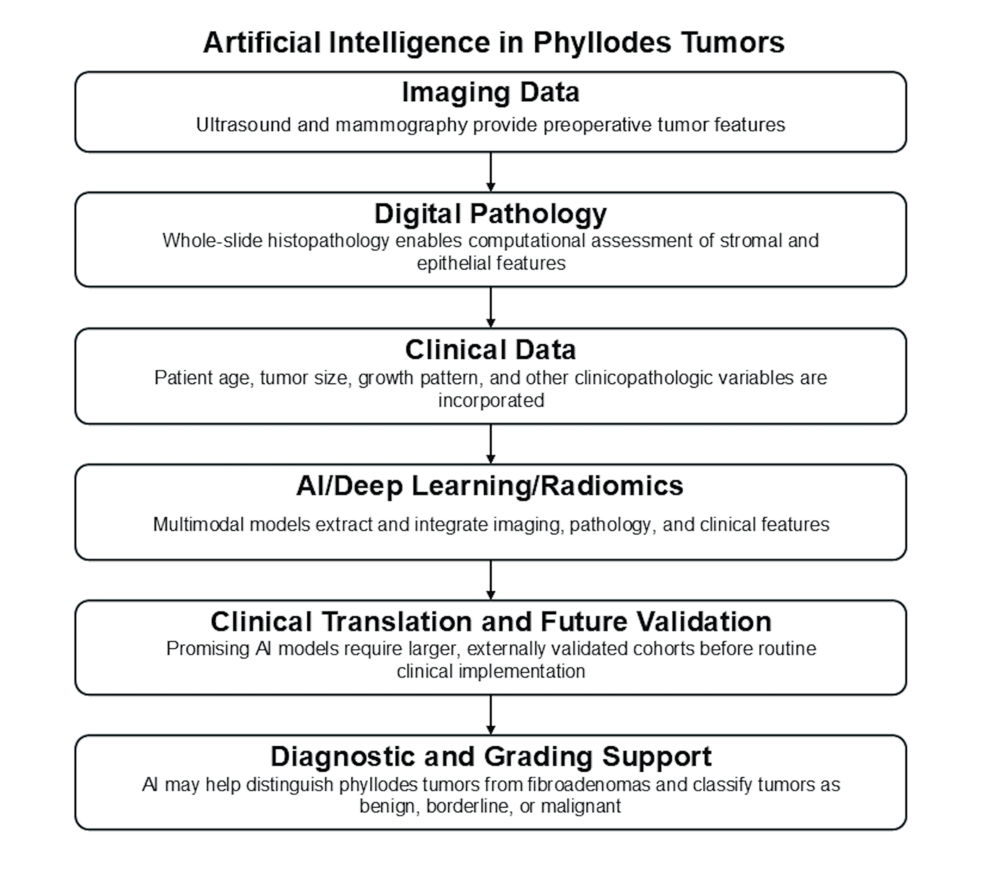
The persistent difficulty in distinguishing preoperatively between benign, borderline, and malignant lesions continues to drive research into advanced molecular pathology. Morphological overlap with cellular fibroadenomas complicates histopathological evaluation. While local recurrence and metastatic potential vary widely depending on the histological subtype, the integration of clinical risk factors offers pathways toward more personalized therapeutic strategies.
The clinical course requires careful balancing of surgical margins and adjuvant treatments to mitigate local recurrence. Open questions remain regarding optimal systemic therapies for metastatic disease and the precise molecular drivers that trigger malignant transformation in borderline and benign fibroepithelial lesions.
