
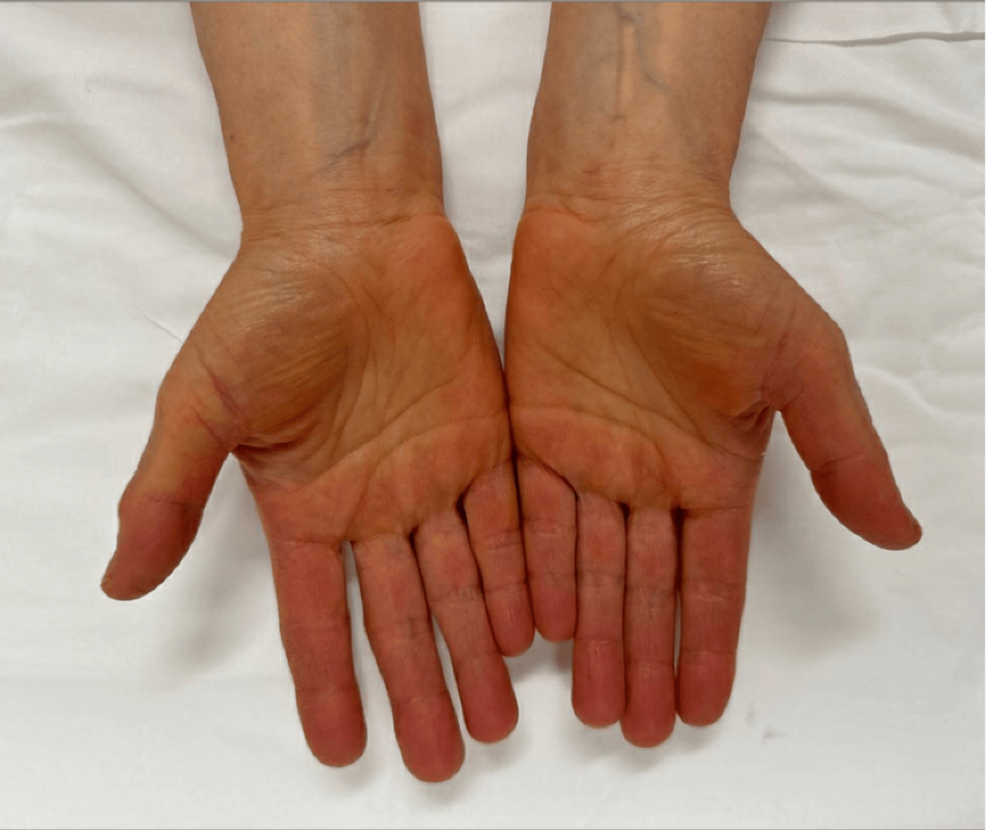
A 57-year-old female patient in her 50s developed diet-induced hypercarotenemia and carotenoderma after consuming at least one cup of shredded carrots daily and carrying baby carrots as a snack over eight years to treat chronic constipation, as reported this week in Cureus. Her case highlights the unrecognized clinical risks of unmonitored dietary fiber reliance.
In Plain English: The Clinical Takeaway
- Hypercarotenemia: A benign medical condition characterized by elevated levels of carotene in the blood, usually triggered by consuming large amounts of yellow, orange, or red vegetables.
- Carotenoderma: The visible yellow-orange skin discoloration that occurs when excess fat-soluble carotene pigments accumulate in the stratum corneum—the outermost layer of the skin.
- Mechanism of Action: Dietary carotenoids are absorbed in the proximal small intestine and converted into vitamin A. When intake overwhelms metabolic processing, excess pigments deposit in lipid-rich skin structures like the palms and soles while sparing the sclera (whites of the eyes).
Eight Years of Carrot-Based Fiber Therapy and Unintended Cutaneous Discoloration
Chronic constipation following a severe motor vehicle accident left the patient pursuing gastrointestinal management for over eight years. Repeated nonspecific clinical advice to increase dietary fiber led her to alter her daily intake. While initial efforts incorporated a varied produce selection, carrots gradually became her predominant dietary fiber source.
Upon presentation to an outpatient gastroenterology clinic, physical examination revealed a striking yellow-orange discoloration of her bilateral palms. Crucially, her sclera and mucous membranes showed no discoloration, distinguishing the presentation from hepatic jaundice, which affects the eyes due to bilirubin accumulation. Laboratory evaluation confirmed the diagnosis of diet-induced hypercarotenemia, showing an elevated serum carotene concentration of 539 mcg/dL against a reference range of 60 to 200 mcg/dL. Her liver enzymes, including aspartate aminotransferase (AST) and alanine aminotransferase (ALT), remained entirely within normal limits at 19 unit/L and 15 unit/L respectively, ruling out secondary hepatobiliary disease.
Differential Diagnosis and Metabolic Markers Supporting Diet-Induced Etiology
Differentiating primary hypercarotenemia from secondary metabolic disorders requires targeted laboratory screening. Secondary drivers of elevated serum carotene include hypothyroidism, diabetes mellitus, anorexia nervosa, and renal dysfunction, all of which alter carotenoid metabolism or clearance. Further investigation in this patient yielded normal baseline parameters, confirming an isolated dietary etiology.
| Laboratory Parameter | Patient Presentation | Three-Month Follow-Up | Reference Range |
|---|---|---|---|
| Carotene | 539 mcg/dL (High) | Not collected | 60–200 mcg/dL |
| AST | 19 unit/L | 29 unit/L | 9–40 unit/L |
| ALT | 15 unit/L | 39 unit/L | 0–40 unit/L |
| Bilirubin | 0.4 mg/dL | 0.5 mg/dL | 0.2–1.3 mg/dL |
| TSH | Not collected | 2.87 uIU/mL | 0.27–4.20 uIU/mL |
| HbA1c | Not collected | 5.5% | <5.7% |
Following dietary counseling to reduce carrot consumption and broaden her fiber sources, the patient returned for a three-month follow-up. Her palmar discoloration had completely resolved. Repeat laboratory testing demonstrated that her thyroid-stimulating hormone (TSH at 2.87 uIU/mL), hemoglobin A1c (5.5%), and estimated glomerular filtration rate (eGFR at 96 mL/min/1.73m²) remained well within normal limits. Although her bowel regularity improved to one daily bowel movement, persistent sensations of incomplete evacuation prompted further diagnostic workup. Anorectal manometry identified underlying dyssynergic defecation, leading to a targeted referral for biofeedback physical therapy.
Contraindications & When to Consult a Doctor
Patients attempting to manage chronic gastrointestinal motility disorders through dietary interventions must exercise caution against single-food fixations. Individuals with baseline liver disease, hypothyroidism, or kidney dysfunction should avoid excessive, unmonitored intake of single carotenoid-heavy produce items, as impaired metabolic conversion can exacerbate systemic accumulation. Clinicians advise professional medical evaluation whenever unexplained skin pigmentation arises, particularly to differentiate benign carotenoderma from systemic pathologies like jaundice or severe endocrine disturbances.
Dietary fiber remains a foundational pillar for treating gastrointestinal disorders, but this case underscores that broad, non-individualized directives to “eat more fiber” carry unintended physical consequences when patients rely exclusively on a single food item. Emphasizing dietary diversity protects against the overaccumulation of fat-soluble compounds while ensuring a balanced micronutrient profile.
References
- Cureus. Diet-Induced Hypercarotenemia in a Patient With Chronic Constipation: A Case Report.
- PubMed. Carotenoderma: Diagnosis, Causes, and Clinical Presentation.
- The Lancet. Management of Chronic Constipation and Dietary Interventions.
