
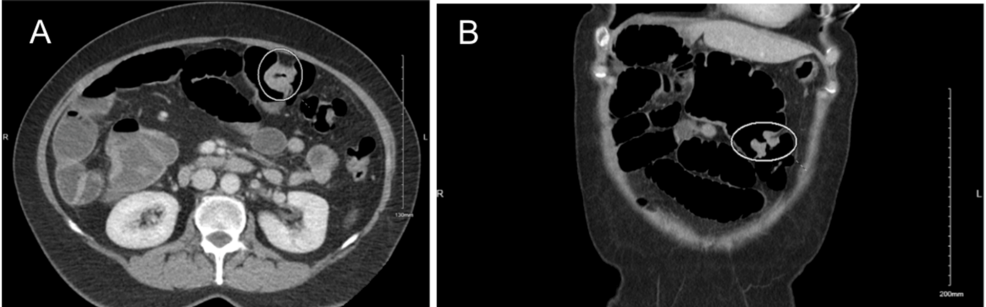
A 54-year-old female patient presenting with acute large bowel obstruction was diagnosed with synchronous colorectal cancer—the simultaneous occurrence of two primary malignant tumors—after a computed tomography (CT) scan identified a single stricture in the transverse colon, while a subsequent colonoscopy revealed distinct, separate masses at both the hepatic and splenic flexures.
In Plain English: The Clinical Takeaway
- Synchronous Colorectal Cancer: An uncommon presentation where a patient develops two or more separate primary cancers in the colon or rectum at the same time, accounting for roughly 3.5% of all colorectal malignancies.
- Diagnostic Discrepancy: Initial CT imaging successfully flagged a bowel obstruction and one distal transverse colon lesion, but failed to identify the concurrent hepatic and splenic flexure masses, which were only caught via colonoscopy.
- Surgical Resolution: Despite elevated tumor markers—such as Carcinoembryonic Antigen (CEA) at 22.9 ng/mL—subtotal colectomy with lymphadenectomy successfully removed both invasive adenocarcinomas with negative margins and no lymph node metastasis (T4aN0M0).
Diagnostic Discrepancies Between Computed Tomography and Colonoscopy
The clinical puzzle began when the 54-year-old patient arrived at the hospital suffering from progressively worsening abdominal pain, nausea, vomiting, and a three-day history of no bowel movements or passing gas. An initial contrast-enhanced CT scan of the abdomen and pelvis exposed a focal stricture and apple core lesion in the distal transverse colon, causing diffuse dilation of the small bowel and right hemicolon. This imaging pointed toward a large bowel obstruction secondary to a colonic mass.
However, once the acute obstruction subsided, clinicians administered 4 L of polyethylene glycol and performed a diagnostic colonoscopy. The endoscopic view altered the surgical roadmap. Rather than a single focal lesion, the procedure exposed a circumferential, ulcerated mass at the hepatic flexure that could not be traversed by the scope, alongside a half-circumferential, polypoid-shaped mass at the splenic flexure.
Pathological Findings and Molecular Biomarkers
Serum tumor marker evaluations revealed significant elevations: Carcinoembryonic Antigen (CEA) reached 22.9 ng/mL against a normal ceiling of 3 ng/mL, while Carbohydrate Antigen 19-9 (CA 19-9) registered at 88 U/mL against a normal ceiling below 34 U/mL. A thoracic CT scan ruled out distant thoracic metastasis. Pathological examination of the biopsy specimens identified a well-differentiated invasive adenocarcinoma at the hepatic flexure and a complex tubulovillous adenoma with severe dysplasia at the splenic flexure.
Subsequent microscopic analysis of the resected tissues following subtotal colectomy mapped out the precise disease stage. The hepatic flexure mass measured 5 cm by 3 cm, showing moderately differentiated invasive colonic adenocarcinoma involving the mucosa, submucosa, and muscularis propria. The splenic flexure mass measured 5 cm by 2.5 cm by 0.5 cm, demonstrating moderately differentiated invasive colonic adenocarcinoma extending through the muscularis propria with microscopic serosal involvement, though no invasion through the serosa was noted. Crucially, all 14 harvested lymph nodes tested negative for malignancy, resulting in a final TNM staging of T4aN0M0.
| Clinical Parameter | Patient Value | Reference Range / Normal Limit |
|---|---|---|
| Carcinoembryonic Antigen (CEA) | 22.9 ng/mL | 0–3 ng/mL |
| Carbohydrate Antigen 19-9 (CA 19-9) | 88 U/mL | <34 U/mL |
| Mismatch Repair (MMR) Status | Negative for deficiency | Normal expression |
| Lymph Node Involvement | 0/14 resected nodes positive | Negative |
Molecular Genetics
Synchronous colorectal cancer represents approximately 3.5% of all colorectal malignancies, showing a male-to-female predominance of 1.8:1. Patients with underlying inflammatory bowel disease, hereditary nonpolyposis colon cancer (Lynch syndrome), familial adenomatous polyposis, or serrated polyposis syndromes face elevated risks. The underlying cellular damage often stems from chromosomal instability, microsatellite instability (MSI), and genetic methylation pathways.
Interestingly, both tumor samples in this patient’s case tested negative for mismatch repair (MMR) protein deficiency. Clinicians should be aware of SCC, as colonoscopy can identify tumors not visualized on computed tomography (CT), and early surgical intervention can ultimately be curative for patients.
When to Consult a Doctor
Patients undergoing diagnostic evaluation for persistent abdominal pain, unexplained weight loss, or changes in bowel habits should recognize that standard cross-sectional imaging like computed tomography may fail to visualize all concurrent mucosal lesions. Colonoscopy remains the clinical tool for direct visualization, precise tumor localization, and tissue biopsy. Individuals with a personal history of inflammatory bowel disease, known hereditary cancer syndromes, or those reaching the recommended screening age of 45 should follow screening recommendations. Immediate medical evaluation is warranted if red-flag symptoms arise.
The patient recovered steadily following the subtotal colectomy with ileosigmoid anastomosis, successfully managing postoperative complications like non-bloody diarrhea with banana flakes (transgalactooligosaccharides) before being discharged in stable condition on postoperative day 8.
