
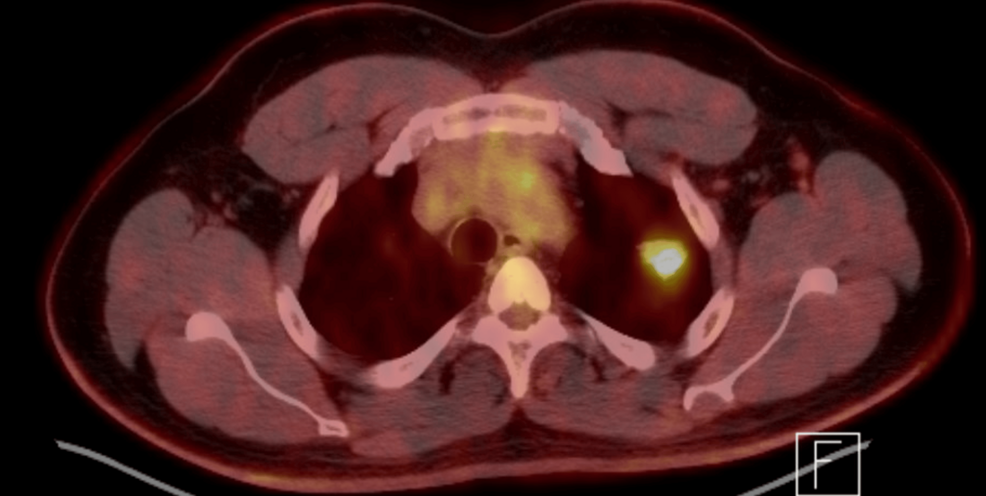
A 41-year-old African American male diagnosed with a typical carcinoid tumor of the lung manifested an aggressive Stage IIIA clinical profile, featuring multi-station mediastinal lymph node metastasis and lymphovascular invasion. Published in Cureus, the case study contrasts standard low-grade histological expectations with intermediate- or high-grade biological behavior.
In Plain English: The Clinical Takeaway
- Typical Carcinoid Tumor: A well-differentiated, low-grade neuroendocrine neoplasm that usually exhibits slow growth and a favorable long-term prognosis.
- Lymphovascular Invasion: The presence of cancer cells within blood vessels or lymphatic channels, indicating a higher potential for the disease to spread.
- pT2a N2 M0 Staging: A clinical classification system indicating a primary tumor size between 3 and 4 centimeters (T2a), spread to ipsilateral mediastinal lymph nodes (N2), and no distant metastases (M0).
Diagnostic Complexities of an Aggressive Lung Neoplasm
Subsequent magnetic resonance imaging of the abdomen and pelvis incidentalized a lung nodule, prompting a dedicated computed tomography scan of the chest. The imaging identified a 2.4 by 2.7 centimeter lobulated, pleura-based lesion located in the left lung apex, alongside a 1.4 centimeter enlarged node in the left aortopulmonary window.
A positron emission tomography scan confirmed high metabolic activity, or hypermetabolism, within both the left upper node and the aortopulmonary window lymph nodes. Despite the high radiological likelihood of malignancy, preoperative diagnostic procedures—including fiberoptic bronchoscopy, bronchoalveolar lavage, endobronchial ultrasound-guided transbronchial needle aspiration, and transthoracic needle biopsy—yielded non-diagnostic or negative cytologic evaluations. As noted in the Cureus report, carcinoids frequently display a dense stromal and desmoplastic composition, resulting in low cellularity within small core needle biopsies.
Detailed Pathological Findings
To secure a definitive diagnosis, the patient underwent a robot-assisted video-assisted thoracoscopic surgery. Intraoperative findings revealed markedly enlarged and bulky lymph node stations, which prompted the precautionary placement of a venous access port for anticipated systemic chemotherapy. Frozen section analysis confirmed neoplastic involvement within the nodes.
Final pathological evaluation classified the resected primary tumor as a 3.8 centimeter typical carcinoid with negative surgical margins, satisfying an R0 resection after a left upper lobe segmentectomy. However, the analysis also confirmed adverse prognostic features, including lymphovascular invasion, perineural invasion, and direct phrenic nerve involvement. Multi-station metastasis was confirmed in lymph node stations 5 and 6, establishing the final pathological staging as pT2a N2 M0, or Stage IIIA.
| Pathological Feature | Observed Finding | Standard Prognostic Expectation |
|---|---|---|
| Tumor Histology | Typical Carcinoid (G1) | Low mitotic rate, absence of necrosis, 5-year survival 87% to 100% |
| Lymph Node Status | Multi-station N2 Disease | Prevalent in atypical carcinoids; diminishes 5-year disease-free survival |
| Invasion Metrics | Lymphovascular & Perineural | Suggestive of intermediate-grade (G2) biological behavior |
Multidisciplinary Management and Surveillance Protocols
Following resection, the multidisciplinary tumor board evaluated the patient’s case against current international consensus guidelines, including those established by the National Comprehensive Cancer Network. Because all gross disease was successfully resected, the tumor board recommended against adjuvant chemotherapy or radiation therapy, aligning with guidelines that advise close observation over postoperative cytotoxic therapy for resected bronchial neuroendocrine tumors.
Given the documented phenomenon of late recurrences in bronchopulmonary neuroendocrine neoplasms, lifelong oncological surveillance remains mandatory. The surveillance strategy incorporates contrast-enhanced computed tomography scans of the chest at six-month intervals for the first two years, alongside plans for a gallium-68 DOTATATE positron emission tomography scan to detect early local recurrence or occult distant metastases.
Contraindications & When to Consult a Doctor
Adjuvant systemic chemotherapy and routine locoregional radiation are not recommended by current National Comprehensive Cancer Network guidelines in the absence of residual gross disease.
References
- Kulkarni N, Albrecht R. Typical Carcinoid Tumor of the Lung: A Case Report Demonstrating Surveillance, Epidemiology, and End Results Database Analysis. Cureus. 2026;18(10):e117647.
- World Health Organization. WHO Classification of Tumours: Thoracic Tumours. 5th ed. International Agency for Research on Cancer; 2021.
- National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology: Neuroendocrine and Adrenal Tumors. Version 2.2024.
