
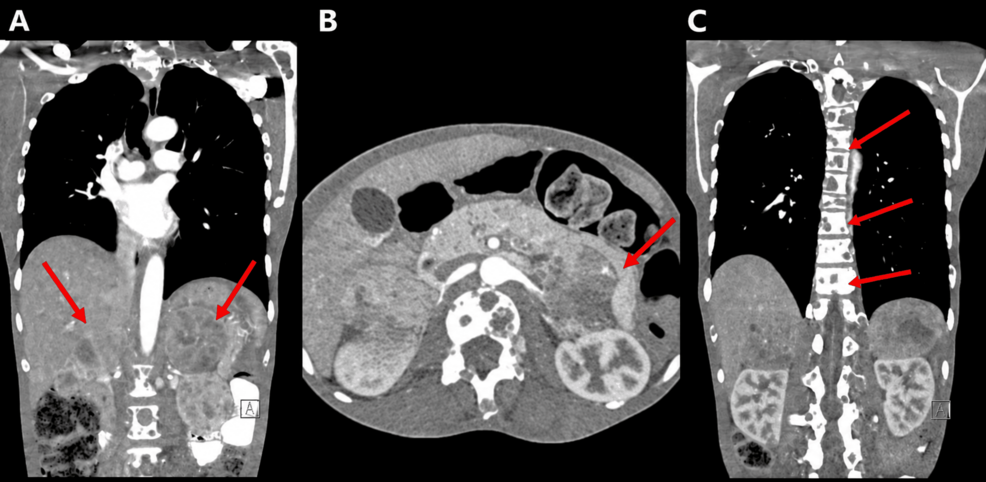
A 40-year-old man presented with back pain, urinary retention, mild unilateral weakness, and weight loss, later developing severe labile hypertension reaching 225/106 mmHg, large bilateral adrenal masses, and extensive skeletal metastases.
In Plain English: The Clinical Takeaway
- Extreme Hormonal Overproduction: The patient’s urine tests showed massive elevations in catecholamines—hormones produced by the adrenal glands—indicating a severe underlying tumor burden.
- Diagnostic Discordance: While biochemical tests strongly pointed toward pheochromocytoma (a catecholamine-secreting tumor), tissue biopsies from skeletal metastases revealed a well-differentiated neuroendocrine tumor without clearly establishing the primary organ of origin.
- Rapid Clinical Decline: Despite interventions including alpha-blockade, palliative radiotherapy, and chemotherapy, the patient experienced multiple systemic failures—including infections and hemorrhages—ultimately resulting in death.
Clinical Findings and Extreme Catecholamine Excess
Initial evaluations at presentation revealed a blood pressure reading of 158/104 mmHg, which quickly escalated to severe, volatile spikes surpassing 180/110 mmHg and peaking at 225/106 mmHg. Contrast-enhanced computed tomography scans demonstrated approximately 10-cm bilateral heterogeneous adrenal masses alongside diffuse lytic skeletal metastases.
Biochemical analysis confirmed profound catecholamine excess. The patient’s urine metanephrine-to-creatinine ratio reached 42,040 µg/g against a reference range of 29 to 158 µg/g. Normetanephrine levels measured 6,079 µg/g creatinine (reference range 53–659 µg/g), and vanillylmandelic acid registered 212 mg/g creatinine (reference range 1.1–4.1 mg/g). Furthermore, serum calcitonin was markedly elevated at 4,680 pg/mL (reference ≤8.4), and carcinoembryonic antigen (CEA) stood at 239 ng/mL against a non-smoker reference of less than 3.8 ng/mL.
Histopathology and Diagnostic Challenges
An expert review of a bone biopsy identified a metastatic well-differentiated neuroendocrine tumor, classified as WHO grade 3 (2017) with a Ki-67 proliferation index of approximately 40%. Immunohistochemical staining showed the tumor expressed chromogranin, synaptophysin, pancytokeratin, thyroid transcription factor 1 (TTF-1), CEA, paired box 8 (PAX8), and cytokeratin 7. However, it tested negative for calcitonin, thyroglobulin, CK20, GATA3, and S100.
Physical examinations also revealed small polypoid lesions at the tip of the tongue, interpreted as possible mucosal neuromas. Combined with thyroid calcifications, these findings raised clinical suspicion for multiple endocrine neoplasia type 2B (MEN2B). However, definitive diagnostic confirmation via thyroid fine-needle aspiration, RET testing, and functional imaging could not be completed prior to the patient’s rapid clinical deterioration.
Therapeutic Interventions and Fatal Complications
The patient received targeted medical and oncological management, including alpha-blockade to control blood pressure volatility, palliative spinal radiotherapy to address impending spinal cord compression, and systemic chemotherapy utilizing carboplatin and etoposide.
The clinical course was severely complicated by profound pancytopenia and extended-spectrum beta-lactamase (ESBL)-producing Escherichia coli bacteremia. Despite aggressive medical management, the patient suffered progressive respiratory and renal failure, gastrointestinal bleeding, and an intracranial hemorrhage, culminating in death.
