
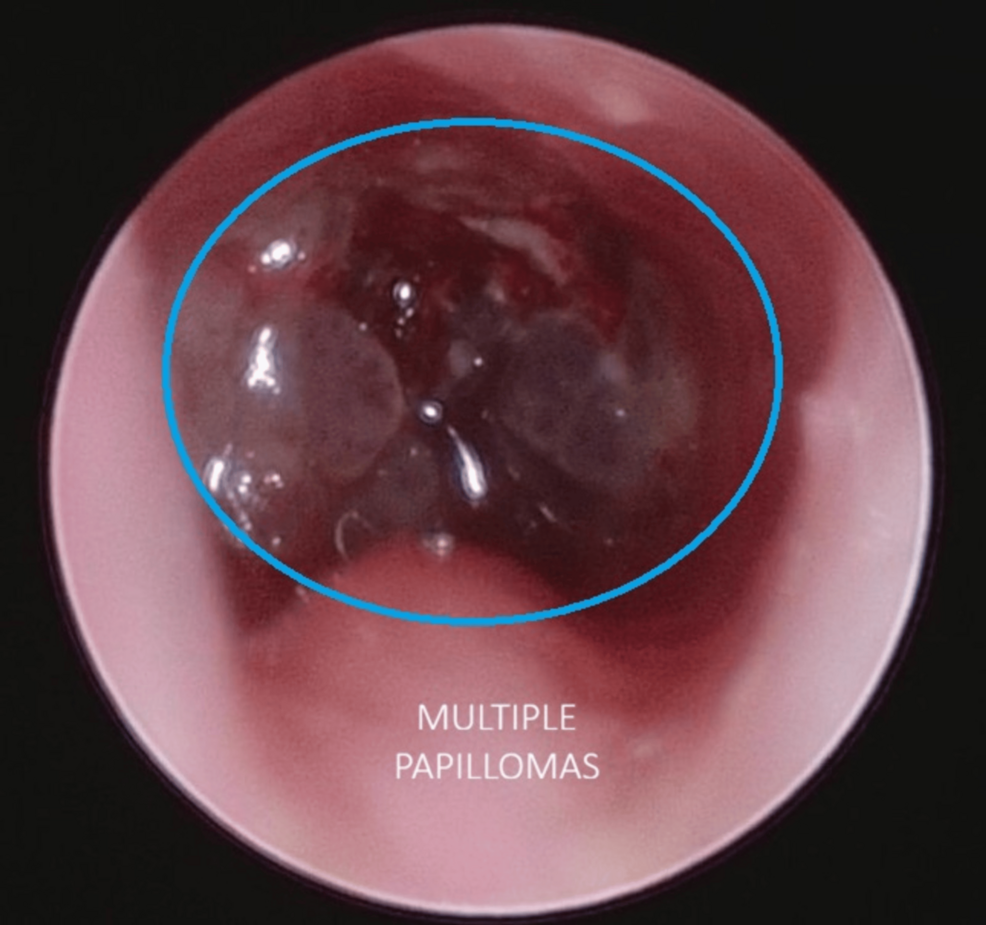
A two-year-old boy with juvenile-onset recurrent respiratory papillomatosis underwent complex dynamic airway management during a 180-minute surgical debulking, as reported in a case study. The procedure balanced spontaneous ventilation with specialized tube exchanges and transnasal humidified rapid-insufflation ventilatory exchange to address extensive lesions obstructing both the upper airway and the tracheobronchial tree.
Juvenile-onset recurrent respiratory papillomatosis is a chronic disease driven predominantly by human papillomavirus types 6 and 11. It creates recurring growths in the respiratory tract that often demand repeated surgical debulking. Managing anesthesia in these pediatric cases is notoriously difficult because clinicians must share the airway with the surgical team while navigating friable, bleeding lesions and a constant risk of obstruction.
In Plain English: The Clinical Takeaway
- Airway Management: Doctors had to continuously switch breathing tubes and oxygen techniques as surgeons removed growths that were blocking the child’s windpipe.
- Coblation Safety: Surgeons used a specialized radiofrequency tool called coblation to remove the papillomas.
- Laryngospasm Response: When the child’s vocal cords temporarily spasmmed during tubeless oxygen delivery, the medical team deepened anesthesia and applied topical local anesthetic to restore normal breathing within a minute.
Managing a Failed Decannulation and an Unstable Airway
The patient, a 15-kg toddler, was admitted for evaluation after multiple attempts to remove a long-term tracheostomy failed. Although the child breathed adequately through a metallic Jackson tracheostomy tube, examination suggested that papillomatous growths sitting above the stoma had caused near-complete obstruction of the upper airway. Because the existing metallic tube lacked a universal connector and could not attach directly to the anesthesia circuit, clinicians induced anesthesia via a facemask using sevoflurane in a 50:50 oxygen-nitrous oxide mixture while the tube was temporarily corked.
Once deep anesthesia was achieved, the metallic tube was removed and successfully exchanged for a 4.0-mm internal-diameter cuffed flexometallic tube through the tracheostomy stoma. To protect against airway swelling and manage pain, the care team administered dexamethasone at 0.2 mg/kg and paracetamol at 15 mg/kg. A bispectral index monitor was kept between 40 and 60 to track depth of anesthesia. Clinicians also applied 10% lignocaine spray—delivering 10 mg per puff via a 6-fr infant feeding tube attached to the nozzle—directly to the vocal cords every 30 minutes to suppress perioperative respiratory events.
Transitioning Between Tube Exchanges and Tubeless Oxygenation
Anesthesia was maintained using a propofol target-controlled infusion with the Eleveld pharmacokinetic model, targeting an effect-site concentration of 3.5 to 4.5 µg/mL in an oxygen-air mixture. Spontaneous ventilation was supported using a continuous positive airway pressure and pressure support ventilation mode. Surgeons utilized the Smith & Nephew Coblation II system, which operates via controlled ablation using bipolar radiofrequency plasma at low temperatures.
| Airway Strategy Phase | Device or Technique | Key Clinical Purpose |
|---|---|---|
| Induction | Facemask with corked metallic tracheostomy tube | Maintained spontaneous ventilation during volatile gas induction. |
| Initial Excision | 4.0-mm cuffed flexometallic tube | Secured airway and provided ventilation during upper lesion removal. |
| Mid-Procedure | 4.0-mm microlaryngeal surgery tube | Restored tracheal seal after infraglottic lesions were excised and an air leak developed. |
| Distal Excision | Tubeless THRIVE (10–20 L/min) | Allowed unobstructed surgical access to lesions located at and beyond the carina. |
As surgeons excised infraglottic lesions, the natural seal created by the growths disappeared, causing a drop in tidal volume down to roughly 4 mL/kg. Clinicians rapidly exchanged the flexometallic tube for a 4.0-mm microlaryngeal surgery tube, whose larger cuff restored an effective tracheal seal. To reach distal lesions located near the carina and mainstem bronchi, the microlaryngeal tube was removed entirely. The tracheostomy stoma was sealed with gauze and an adhesive bandage, and tubeless oxygenation was instituted using transnasal humidified rapid-insufflation ventilatory exchange at flows of 10 to 20 L/min.
Resolving Laryngospasm During Distal Airway Resection
During the 38-minute tubeless ventilation phase, the patient experienced a single episode of laryngospasm marked by breath-holding and an oxygen saturation drop to 85%. Surgical stimulation was immediately paused, and the anesthesia depth was increased by raising the propofol concentration. Additional topical lignocaine was applied to the vocal cords, safely resolving the spasm within a minute while remaining below the calculated toxic dose of 75 mg (5 mg/kg) for this 15 kg child. At the end of the 180-minute procedure, an uncuffed tracheostomy tube was reinserted, and the child maintained hemodynamic stability during emergence.
