
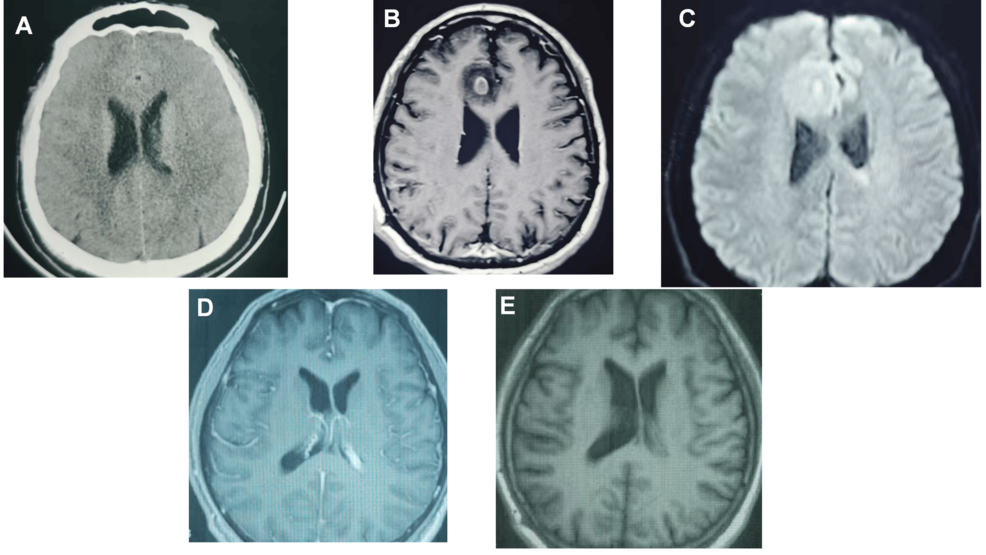
A 48-year-old man developed a brain abscess and radiologically suspected ventriculitis approximately two weeks after self-extracting a carious tooth. Following sequential antimicrobial therapy without surgical drainage at Beijing Tiantan Hospital, his clinical symptoms and neuroimaging abnormalities resolved.
In Plain English: The Clinical Takeaway
- Brain Abscess: A focal collection of pus inside the brain tissue that causes swelling and neurological deficits.
- Ventriculitis: An infection of the fluid-filled cavities (ventricles) inside the brain, which increases procedural hazards and clinical complexity.
- Non-Surgical Management: In specific cases evaluated closely by clinicians, targeted intravenous antibiotics can resolve intracranial infections without invasive drainage or surgery.
Admission to Beijing Tiantan Hospital After Unsuccessful Local Treatment
The patient initially experienced a headache, fever, and chills roughly 17 days after pulling out a decayed tooth on his own without dental evaluation or antibiotics. He also reported swimming in a public pool, though the exact timing remained unclear. Non-contrast cranial computed tomography (CT) performed on Day 4 at Yuxi People’s Hospital showed no obvious brain parenchymal abnormalities. However, subsequent magnetic resonance imaging (MRI) revealed abnormal signals near the right frontal lobe and left lateral ventricle.
After failing to improve on local antimicrobial regimens that included meropenem, doxycycline, cefoperazone-sulbactam, and ceftazidime-avibactam, he transferred to Beijing Tiantan Hospital on Day 11. Testing of the cerebrospinal fluid obtained via lumbar puncture on Day 8 revealed a lactate concentration of 8.1 mmol/L, a glucose concentration of 1.27 mmol/L, an opening pressure of 230 mmH₂O, a protein concentration of 226.9 mg/dL, and a white blood cell count of 2,108/μL containing 83.2% polymorphonuclear cells. These findings indicated marked cerebrospinal fluid inflammation, although blood and cerebrospinal fluid cultures remained negative following prior antibiotic exposure.
Radiological Findings and the Decision to Avoid Surgical Intervention
Brain MRI on Day 22 confirmed a well-defined nodular lesion measuring approximately 12 by 10 millimeters in the right frontal lobe. T1-weighted imaging showed low signal intensity within the lesion, T2-weighted and fluid-attenuated inversion recovery (FLAIR) scans revealed mildly increased signal intensity, and examinations also demonstrated prominent ring enhancement alongside restricted diffusion. Separate abnormalities involved the left lateral ventricular region, including thickening and enhancement of the left ventricular wall and choroid plexus, suggestive of ventricular infection with possible intraventricular empyema.
Attending physicians and senior clinicians at Beijing Tiantan Hospital held detailed discussions and decided against stereotactic aspiration, ventricular sampling, or craniotomy. Instead, the patient received intravenous meropenem at 2 grams every eight hours and vancomycin at 1 gram every 12 hours for 16 days.
| Clinical Parameter | Initial Presentation / Finding | Follow-Up Status |
|---|---|---|
| Right Frontal Lesion Size | ~12 × 10 mm ring-enhancing lesion (Day 22) | Markedly decreased enhancement and resolution of surrounding edema (Day 56) |
| Cerebrospinal Fluid WBC | 2,108/μL (83.2% polymorphonuclear cells) | Improved inflammatory indices alongside clinical recovery |
| Ventricular Status | Left ventricular wall thickening and suspected intraventricular empyema | Improvement of left ventricular and ependymal abnormalities on follow-up MRI |
| Surgical Intervention | None performed (no abscess aspiration or ventricular drainage) | Complete resolution achieved via sequential antimicrobial therapy |
Contraindications & When to Consult a Doctor
Invasive surgical drainage remains mandatory in many cases characterized by significant mass effect, neurological deterioration, or failure to respond to empirical antimicrobial therapy.
Resolution and Diagnostic Limitations in Odontogenic Intracranial Spread
Follow-up MRI examinations, including imaging performed on Day 56, demonstrated significant reduction in the right frontal lesion size, markedly decreased contrast enhancement, and regression of the left ventricular and ependymal abnormalities. The patient’s fever, headache, and agitation resolved completely without surgical drainage.
Investigators emphasized important diagnostic limitations. Neither the temporal association with the self-extracted tooth nor the public pool swimming exposure established definitive causality, as microbiological confirmation was absent due to prior antibiotic administration and the omission of surgical tissue acquisition.
