
Between 27 November 2024 and 31 January 2025, a remote clinical pathway evaluated digital-first delivery of GLP-1 receptor agonist therapy to 8,127 adult women. Prescribed primarily tirzepatide, participants achieved a mean weight reduction of 16.1 kg at six months, demonstrating substantial cardiometabolic improvements across diverse demographic and socioeconomic groups.
In Plain English: The Clinical Takeaway
- What was studied: A fully remote healthcare model provided GLP-1 receptor agonist medications—specifically tirzepatide—to 8,127 adult women, tracking their weight and blood test results over six months.
- The core finding: The vast majority of participants with follow-up data lost weight, achieving an average reduction of 15.5% of their starting body weight alongside significant improvements in blood sugar and cholesterol levels.
- Why it matters: The data shows that digital-first clinical delivery can administer advanced metabolic therapies, maintaining retention rates and consistent clinical outcomes across various age and socioeconomic groups.
Digital Onboarding and Baseline Characteristics of the Cohort
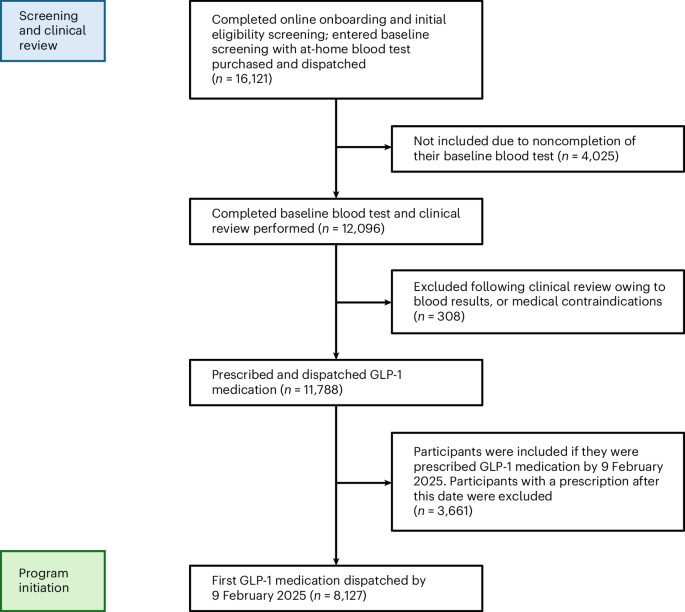
The program was structured exclusively for adult women, with sex at birth confirmed via supervised identity verification during remote onboarding. Out of 16,121 individuals meeting initial screening criteria, 4,025 did not complete required baseline blood testing, and 308 were excluded after clinical review revealed abnormal laboratory findings or medical contraindications. The final analytic cohort comprised 8,127 participants who were prescribed and dispatched therapy before the administrative cutoff.
Participants presented with a mean baseline weight of 104.2 kg and a mean body mass index of 38.2 kg/m², with 95.5% meeting criteria for class I through III obesity. The cohort spanned ages 18 to 79, with 82.1% falling between 30 and 60 years old. Baseline biochemical profiles showed a mean total cholesterol of 5.7 mmol/l, low-density lipoprotein cholesterol of 3.8 mmol/l, and glycated hemoglobin (HbA1c) of 36.2 mmol/mol, aligning with community populations with obesity free of established cardiovascular disease.
Dosing Trajectories and Six-Month Weight Outcomes
Treatment initiation relied heavily on tirzepatide 2.5 mg weekly, administered to 99.6% of the cohort, while semaglutide accounted for a minimal fraction of initial prescriptions. Dose escalation followed clinical licensing guidelines but remained individualized based on weight trajectory and patient tolerability. Clinicians deferred escalation for participants demonstrating adequate weight loss of at least 2 kg per month or reporting clinically meaningful side effects. By the six-month mark, mean tirzepatide exposure rose to 9.5 mg weekly.
Among the 7,297 participants with available six-month weight measurements, 99.3% experienced weight reduction. Mean absolute weight dropped by 16.1 kg, translating to a 15.5% decrease from baseline. Clinically meaningful thresholds were widespread: 96.1% achieved at least 5% weight loss, 83.1% reached 10%, 53.5% hit 15%, and 22.4% attained a 20% reduction. Temporal analysis revealed that 58.0% of total six-month weight reduction occurred within the first three months of therapy.
Glycemic Normalization and Cardiometabolic Biomarkers
Parallel improvements emerged in glycemic control and lipid profiles among participants with paired biochemical assessments. Mean HbA1c decreased from 36.3 to 33.0 mmol/mol, representing a shift from approximately 5.5% to 5.2% on the National Glycohemoglobin Standardization Program scale. At baseline, 155 participants presented with values in the diabetic range, while 567 fell into the prediabetic category. Following six months of therapy, HbA1c normalized in 84.5% of those with baseline diabetes and 96.3% of those with prediabetes. Progression from normoglycemia to dysglycemia occurred in only 0.3% of participants.
Subgroup evaluations demonstrated consistent negative weight-change estimates across baseline weight, age, and deprivation strata, confirming the broad efficacy of the intervention. Adjusted linear regression modeling further indicated that each 10-kg greater weight reduction corresponded to a 1.3 mmol/mol greater decrease in HbA1c, linking structural weight loss directly to improved metabolic regulation.
References
- Nature Medicine: Real-world digital-first delivery of GLP-1 receptor agonist therapy in women.
- National Glycohemoglobin Standardization Program (NGSP): Standardization of hemoglobin A1c measurements.
- Clinical guidelines on the pharmacological management of obesity and type 2 diabetes.
