
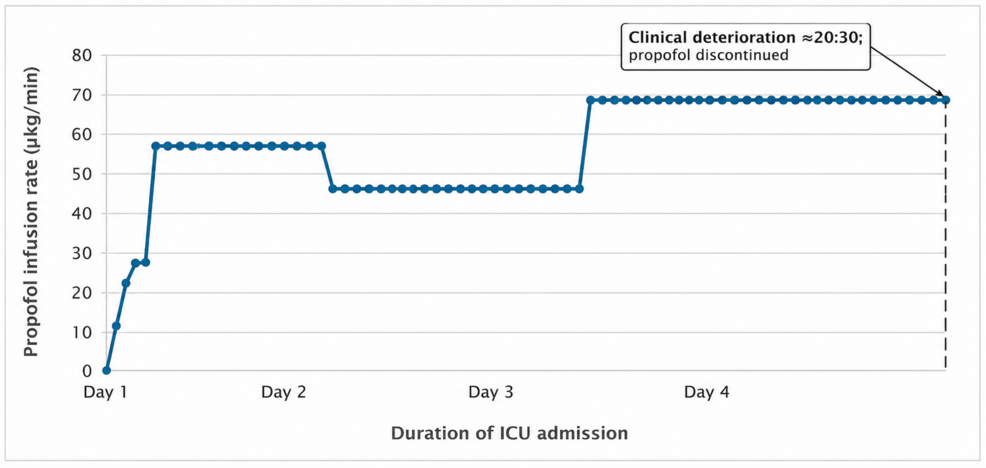
A 21-year-old man in refractory status epilepticus developed severe propofol infusion syndrome (PRIS) following four days of mechanical ventilation and escalating sedation, marked by acute cardiovascular collapse, severe metabolic acidosis, and profound rhabdomyolysis.
Understanding the Clinical Presentation and Immediate Intervention
The patient, who had a previous traumatic brain injury, presented with refractory status epilepticus. To manage his condition, clinicians administered propofol. After four days of continuous infusion—culminating in a final rate of 68.5 micrograms per kilogram per minute for the 35 hours preceding clinical decline—the patient deteriorated abruptly at approximately 20:30 on intensive care unit day four.
The acute presentation included profound bradycardia, rapidly progressive shock, pyrexia, and dark brown urine signaling severe muscle breakdown. Laboratory evaluations revealed a soaring creatine kinase level that initially hit 62,600 International Units per liter at the time of deterioration and ultimately peaked at 931,000 International Units per liter on unit day six. Additional findings featured hypertriglyceridemia at 11.5 millimoles per liter, hyperkalemia at 6.7 millimoles per liter, and acute kidney injury with serum creatinine rising sharply from 89 to 497 micromoles per liter.
Bedside transthoracic echocardiography confirmed global left ventricular dysfunction with an estimated ejection fraction of 20 percent. Serial electrocardiograms tracked rapid electrical deterioration, showing QRS widening, T-wave abnormalities, and a corrected QT interval exceeding 500 milliseconds. Medical teams immediately discontinued propofol within five to ten minutes of the instability, initiating aggressive hemodynamic support with noradrenaline, adrenaline, dobutamine, and vasopressin.
Multimodal Organ Support and Extracorporeal Blood Purification
To combat the multi-organ failure characteristic of severe PRIS, physicians deployed an aggressive, multimodal critical care strategy.
Enteral L-carnitine was administered at 500 milligrams three times daily to address suspected mitochondrial dysfunction, compounded by concurrent valproate exposure. Hemodynamic and metabolic stabilization became evident roughly six hours after propofol cessation, allowing the clinical team to bypass extracorporeal membrane oxygenation or plasma exchange.
Clinical Parameters at Admission and Acute Deterioration
| Clinical Parameter | ICU Admission Value | Day 4 Deterioration Value | Standard Reference Range |
|---|---|---|---|
| Arterial Blood Gas pH | 7.25 | 7.17 | 7.35–7.45 |
| Arterial Bicarbonate (mmol/L) | 21 | 12 | 21–28 |
| Anion Gap (mmol/L) | 16 | 26 | 7–17 |
| Serum Potassium (mmol/L) | 3.9 | 6.7 | 3.5–5.2 |
| Serum Lactate (mmol/L) | 5.4 | 10.3 | <2.0 |
| Triglycerides (mmol/L) | Not Measured | 11.5 | <2 |
In Plain English: The Clinical Takeaway
- What PRIS Is: Propofol infusion syndrome is a potentially fatal condition caused due to prolonged exposure to propofol for sedation, primarily marked by severe cardiorespiratory depression along with a high level of metabolic acidosis.
- Warning Signs: The condition triggers rapid multi-organ breakdown, including sudden heart failure, extreme muscle deterioration, dangerous electrolyte imbalances, and severe blood acidity.
- The Response: Immediate withdrawal of the sedative drug paired with advanced life support, dialysis, and metabolic therapies can yield successful recovery in severe cases.
Contraindications & When to Consult a Doctor
Propofol requires strict administration by trained professionals in monitored hospital environments. Clinicians must weigh risks carefully in patients with acute neurological injuries or compromised mitochondrial fatty acid oxidation. Immediate medical intervention is mandatory if unexplained metabolic acidosis, acute muscle pain, dark urine, or rapid cardiovascular instability occurs during sedative therapy.
