
Patients receiving pacemakers for atrioventricular block faced a lower combined risk of adverse events when treated with left bundle branch pacing rather than standard right ventricular pacing on November 8, 2026, at the American Heart Association Scientific Sessions in Chicago.
The international OptimPacing trial tracked 685 adults across 17 centers in mainland China, Hong Kong, the United Kingdom, Poland, and the United States between June 2021 and January 2025. Investigators randomized patients with an indication for a permanent pacemaker and a high ventricular pacing burden to either left bundle branch pacing or traditional right ventricular pacing.
Overall, 685 patients were randomized and underwent device implantation across the 17 participating centers.
The primary composite endpoint of all-cause mortality, heart failure hospitalization, or pacing-induced cardiomyopathy occurred in 8.5% of the LBBP group compared with 19.2% of the RVP group, as Jiangang Zou reported at the annual meeting. At a median follow-up of 35.1 months, the rate yielded a hazard ratio of 0.41 with a 95% confidence interval ranging from 0.23 to 0.75. The study was simultaneously published in The New England Journal of Medicine.
“LBBP demonstrated superiority over RVP in preserving cardiac function and reducing composite clinical outcomes for atrioventricular block,” said Zou, professor of cardiology at the First Affiliated Hospital, Nanjing Medical University in China.
Zou said that the team expected the left bundle group to do better, but the difference between the two groups was greater than expected.
The divergence between the two treatment arms stemmed primarily from the incidence of pacing-induced cardiomyopathy, which reached 11.7% in the conventional RVP group but remained at 0% among patients who received LBBP. Heart failure hospitalizations occurred in 1.5% of the LBBP cohort and 2.9% of the RVP group, while all-cause mortality rates were 7.4% and 7.7%, respectively.
Conventional RVP implants an active lead in the right ventricular septum or apex. That method can force the lower chambers of the heart to beat out of sync and weaken cardiac muscle over time.
In contrast, among those randomized to left bundle branch pacing, a SelectSecure Model 3830 lumenless lead from Medtronic was placed into the interventricular septum until the left ventricular subendocardium was reached and left bundle branch capture criteria were met.
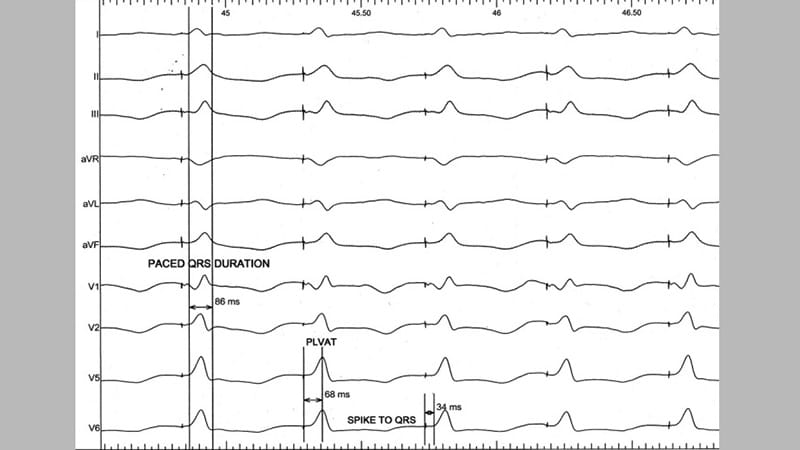
Left bundle branch pacing was successfully implanted in 96.8% of patients. Left bundle branch capture was confirmed in 87.6% of patients, and the final analysis included 331 patients in whom left bundle branch pacing was successful. The average left ventricular activation time reached 70.2 plus or minus 11 milliseconds, and the ventricular pacing burden exceeded 90% in both study groups.
Elaine Wan, a cardiologist, discussed the results of OptimPacing after the presentation.
An independent data monitoring committee reviewed the results of the planned interim analysis after the median follow-up. Key limitations of the OptimPacing trial include its early termination, which may have led to an overestimation of treatment effects.
Zou acknowledged four specific limitations with the study, saying that early termination can lead to an overestimation of treatment effects. A 2023 Heart Rhythm Society guideline on physiologic pacing already addresses conduction system pacing as a way to prevent pacing-related heart failure.
Jiangang Zou said that the results mean left bundle branch pacing should be the first choice for patients with heart block.
Zou and Najm reported no relevant conflicts of interest in connection with the research.
“We need to still follow that,” Najm said.
Earlier coverage: Ambulatory ECG Monitoring Reveals Ventricular Standstill in LBBB Patient
