
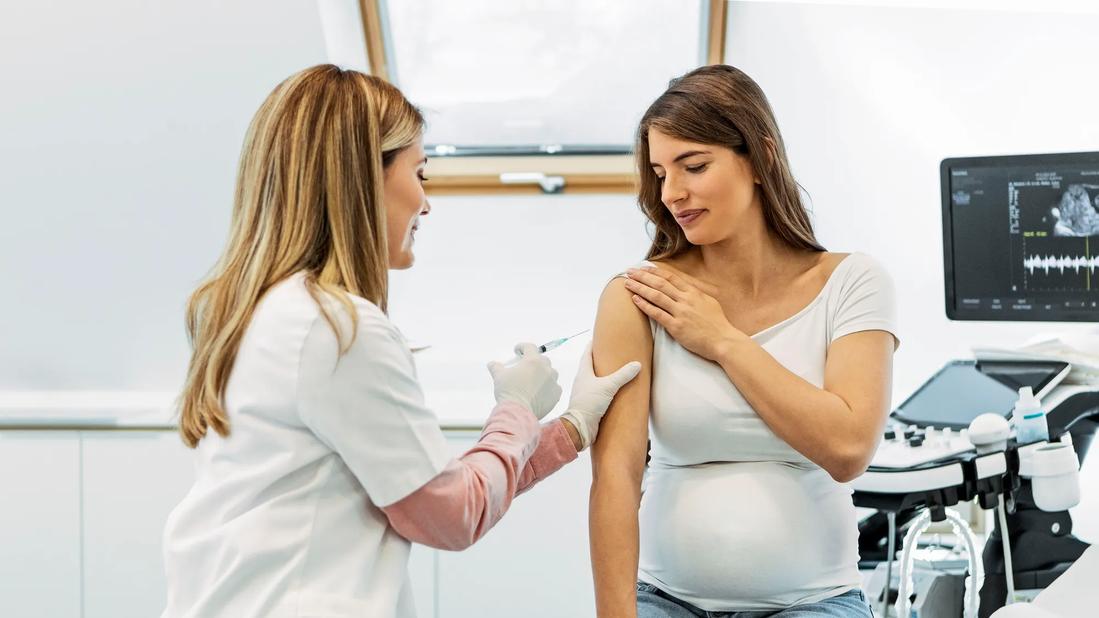
Pediatrician Kristin Barrett, MD, from Cleveland Clinic outlines comprehensive respiratory syncytial virus protection pathways for high-risk infants under 18 months, combining maternal immunization during pregnancy with post-birth monoclonal antibody injections like nirsevimab and clesrovimab to reduce the severity of their symptoms and complications.
Monoclonal Antibodies and Maternal Immunization Protocols for Preterm Infants
Respiratory syncytial virus poses severe health risks to young children, with nearly every child contracting the virus by age 2 according to pediatric data from Cleveland Clinic. High-risk infants face significantly elevated vulnerabilities to severe respiratory distress. To combat this, pediatricians recommend two distinct pharmaceutical defense windows: pre-natal and post-natal.
During pregnancy, administering the Abrysvo (RSVpreF) injection between 32 and 36 weeks—at least 14 days before the expected delivery date—transfers vital maternal antibodies to the fetus. This placental transfer supplies the newborn with sufficient immunological defense for the first six months of life.
Following birth, infants can receive synthetic proteins designed to neutralize the pathogen. Pediatricians administer either nirsevimab (marketed as Beyfortus) or clesrovimab (marketed as Enflonsia) during their initial or second respiratory season. These monoclonal antibodies—laboratory-produced molecules engineered to act as substitute antibodies—actively boost the infant’s immune response throughout their first 18 months.
According to the American Academy of Pediatrics, infants whose mothers received the Abrysvo injection during gestation should still receive monoclonal antibodies if they enter a second high-risk respiratory season.
In Plain English: The Clinical Takeaway
- Maternal Vaccination: Getting the Abrysvo shot late in pregnancy passes protective proteins directly to the baby before birth.
- Monoclonal Protection: Post-birth injections give babies ready-made defense proteins to fight off severe winter infections.
- Targeted Defense: These preventive steps are especially critical for babies born prematurely or with underlying chronic medical conditions.
High-Risk Pediatric Demographics and Environmental Prevention
Certain medical profiles and developmental conditions elevate an infant’s susceptibility to severe respiratory illness. Pediatric specialists urge parents of vulnerable children to adhere strictly to preventive immunization schedules and targeted environmental safety measures.
Infants who benefit most from pre-birth maternal vaccination and post-birth monoclonal therapies include those born preterm before 32 weeks of gestation, immunocompromised infants, and children of American Indian or Alaska native descent. Other qualifying profiles involve chronic lung disease, congenital heart conditions, neuromuscular disorders such as Duchenne muscular dystrophy, and genetic anomalies like Down syndrome or Klinefelter syndrome.
Beyond immunizations, environmental mitigation remains vital. Because the virus transmits via respiratory droplets, infected individuals must wear masks and maintain physical distance from vulnerable infants. Pediatricians advise families to limit large social gatherings during a high-risk infant’s first year of life alongside rigorous hand hygiene.
Contraindications & When to Consult a Doctor
Even with comprehensive pre-natal vaccination and post-birth antibody administration, infants can still contract common winter pathogens. Parents must closely monitor clinical warning signs and seek immediate medical evaluation if critical respiratory distress manifests.
Emergency medical care is required immediately if an infant exhibits blue lips, fingers, or skin; flared nostrils during inhalation; severe retractions of the ribs, neck, or shoulders; fast or shallow breathing; wheezing or gasping; noticeable pauses in breathing; dry diapers or a dry mouth; or difficulty waking and sudden energy changes.
Clinical settings provide necessary round-the-clock supportive care, including intravenous hydration, supplemental oxygen, and medical-grade suctioning to clear obstructed mucus from the infant’s upper airway.
References
- American Academy of Pediatrics: Guidance on Monoclonal Antibody Administration and Maternal Immunization.
