
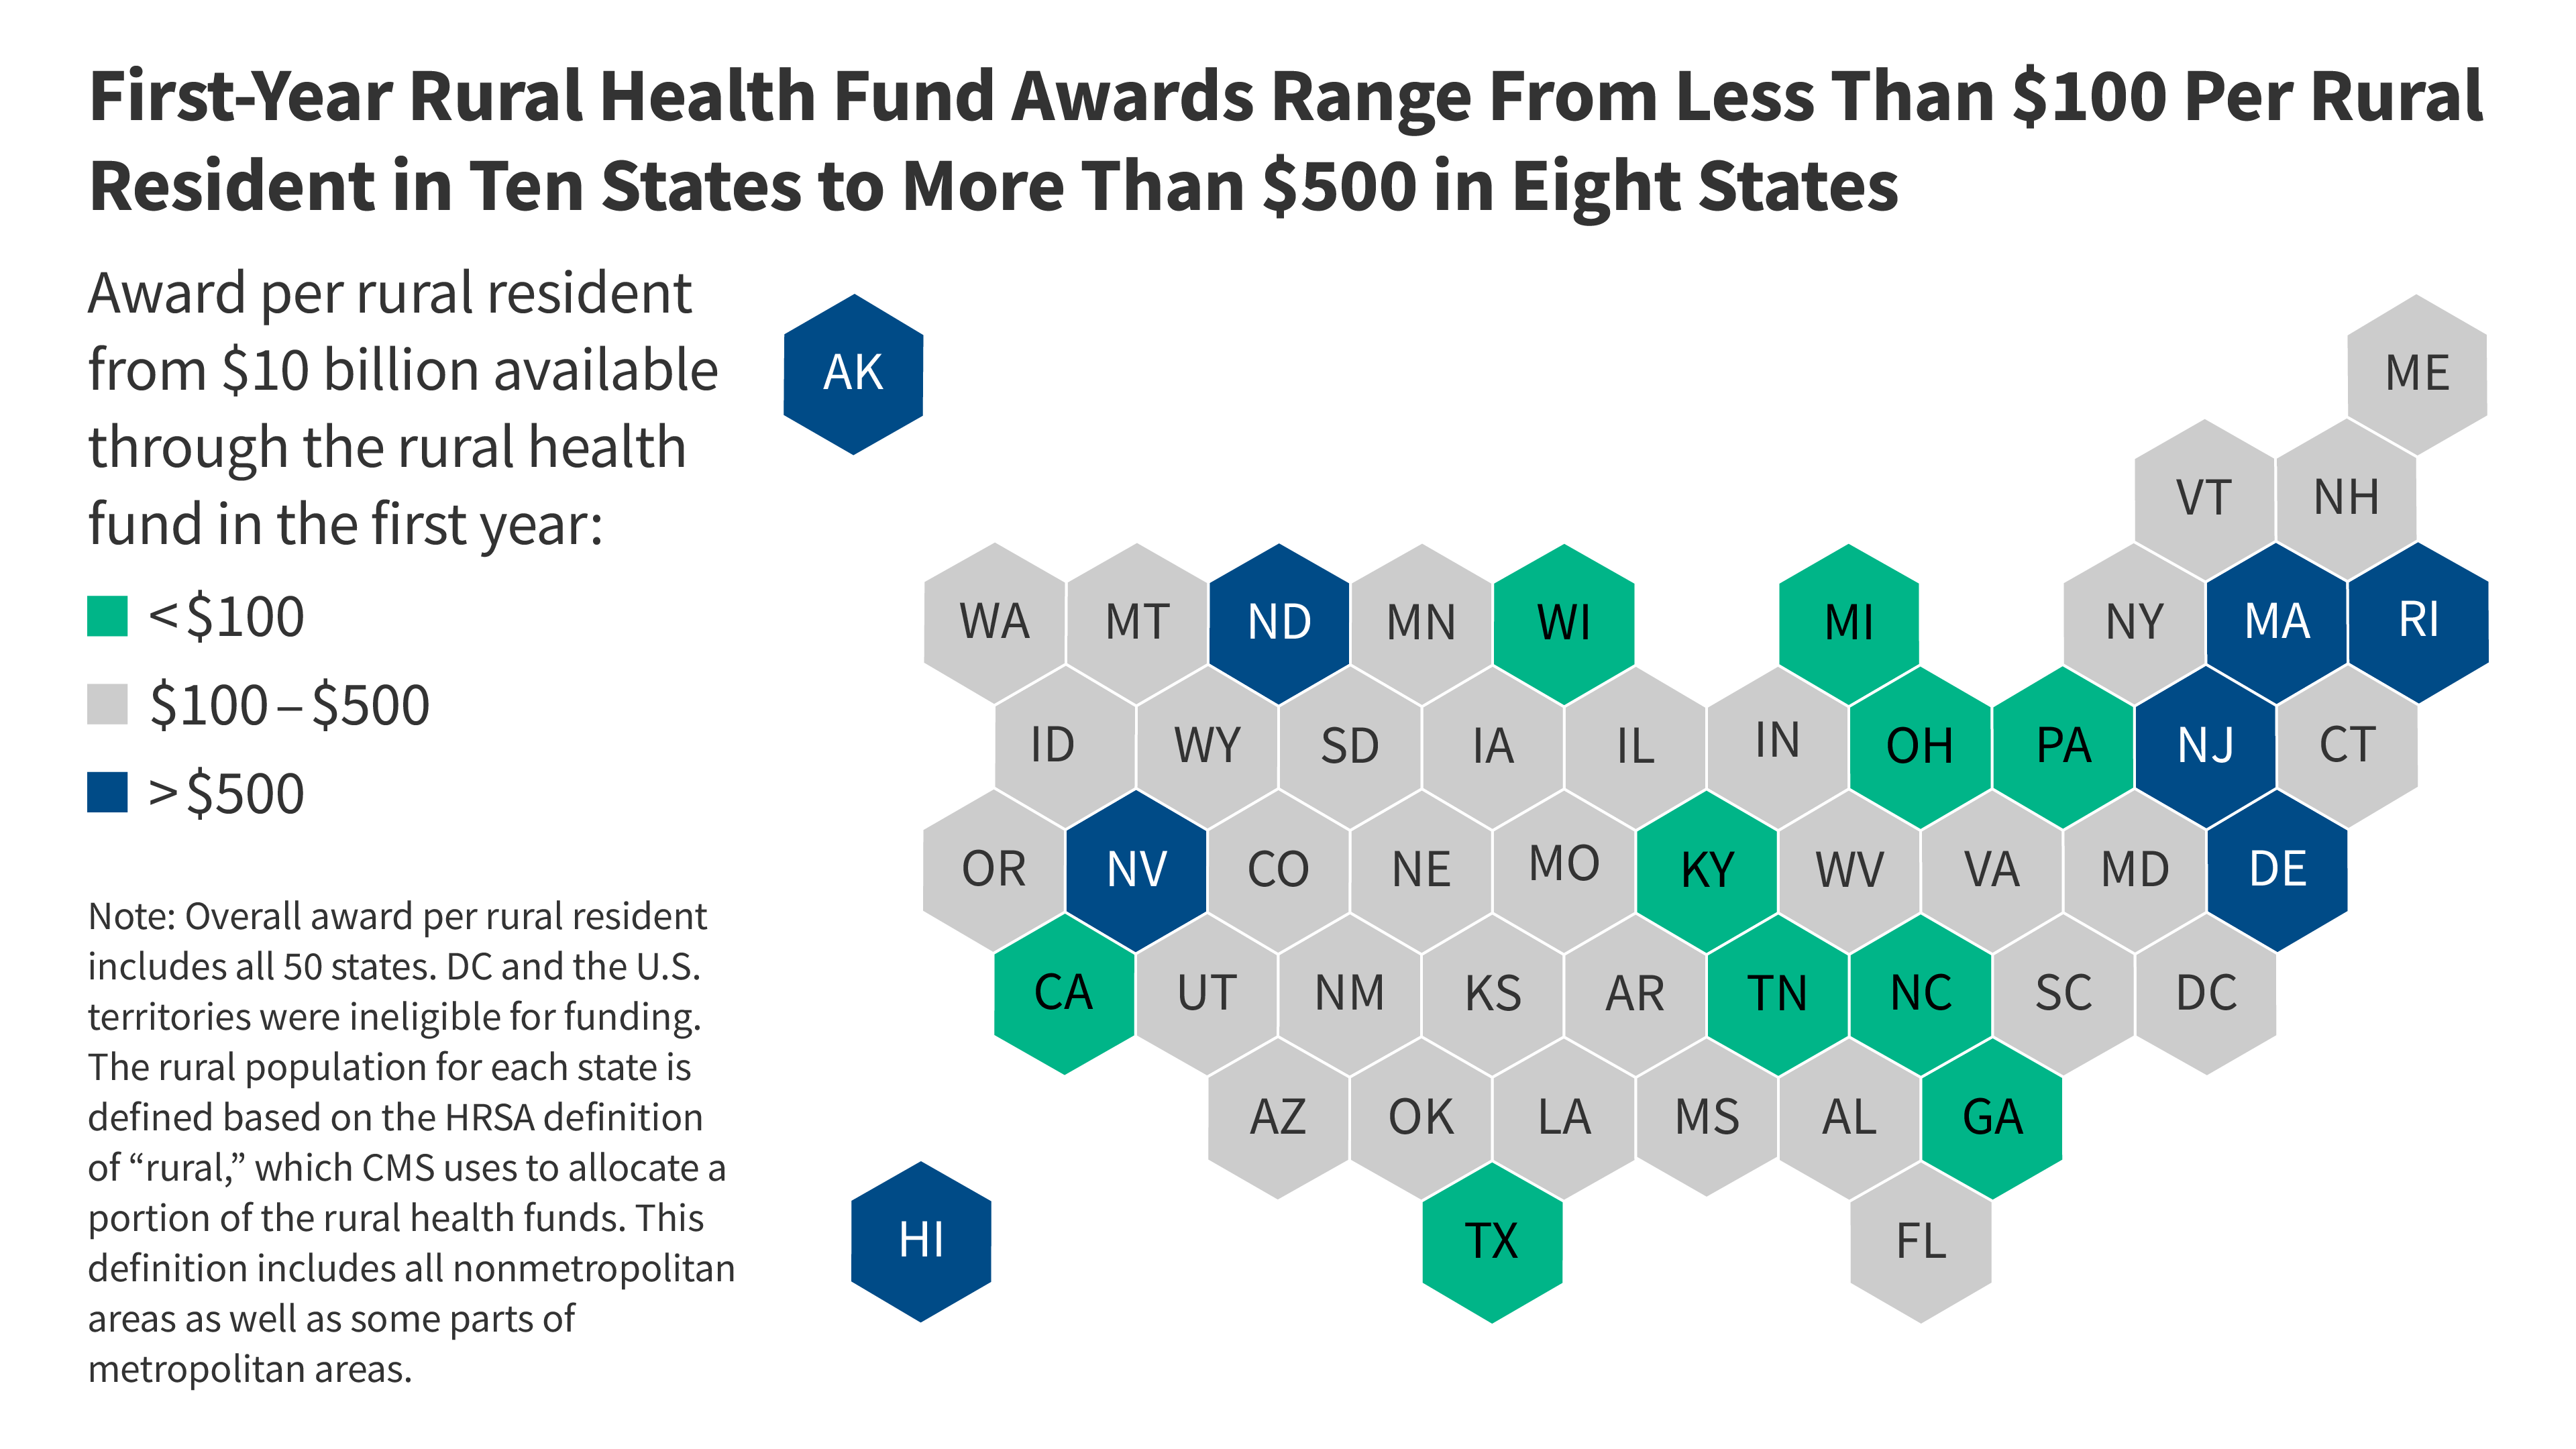
The $50 billion Rural Health Transformation Program, established under the 2025 reconciliation law, provides five years of federal state grants managed by the Centers for Medicare & Medicaid Services (CMS). Created as a political compromise during Senate negotiations, the program addresses concerns over Medicaid spending reductions by funding a broad array of rural health initiatives through fiscal year 2030.
One year into the initiative, the $50 billion federal effort faces acute questions regarding transparency, oversight, and execution. Enacted as part of the 2025 budget reconciliation law, the program was forged during late-stage Senate negotiations. Congressional Republicans introduced the funding as a political compromise to soften the blow of sweeping federal healthcare spending cuts, notably projected reductions of more than $900 billion in Medicaid spending over a decade. While designed to alleviate the strain on rural medical infrastructure, the program’s strict federal timelines, cooperative agreement structures, and highly variable state-level implementation have created a complex landscape for public health oversight.
Structure, Funding Mechanics, and Federal Oversight
Under the statutory framework overseen by CMS, the program distributes $10 billion annually across approved states from fiscal years 2026 to 2030. Rather than issuing standard categorical grants, CMS administers the funding via cooperative agreements. According to federal guidelines, these agreements require substantial CMS project involvement after an award is made, granting the agency leeway to modify permitted uses, terms, and conditions.
All states applied during a fast-paced application window following the release of the Notice of Funding Opportunity on September 15, 2025, with a submission deadline of November 5, 2025. CMS announced the first-year awards on December 29, 2025. States must obligate their first-year funding by October 30, 2026, and submit their initial annual progress reports by August 31, 2026. While states have flexibility to spend allocated funds through the end of the subsequent fiscal year, all program outlays must conclude by the end of fiscal year 2032, with unspent monies subject to CMS redistribution.
In Plain English: The Clinical Takeaway
- Cooperative Funding: Federal dollars are distributed through agreements that give CMS direct oversight in shaping how state health programs operate.
- Broad Medical Scope: Funds are not restricted solely to keeping rural hospitals afloat; they support a wide variety of localized healthcare delivery and public health activities.
- Strict Deadlines: States face tight federal milestones for obligating money and reporting progress, directly influencing their eligibility for subsequent funding years.
Transparency Gaps and State-Level Variability
A primary friction point in the program’s inaugural year involves public transparency and accountability. According to KFF Health News reporting, neither CMS nor several state governments are proactively disclosing comprehensive details regarding funding recipients, approved project budgets, or localized deployment plans. While CMS spokesperson Timothy Foster stated that the agency will publish an annual report on state progress, individual state reports submitted to federal regulators are only intended to be shared upon formal request and are not proactively published.
This lack of proactive data sharing places the burden of oversight squarely on state governments, where reporting transparency varies wildly. Certain states actively engage with lawmakers and public forums, whereas others maintain closed advisory proceedings. Document requests often face months-long delays, complicating timely independent oversight. In Mississippi, the governor vetoed a transparency-related bill, and West Virginia maintains closed-door advisory meetings. Meanwhile, nonprofit entities and journalistic organizations are stepping in to independently collect and repository state applications to track fund distribution.
Comparative Funding Mechanics
| Program Parameter | Rural Health Transformation Program | Medicaid Spending Adjustments |
|---|---|---|
| Total Financial Scope | $50 billion over five years ($10 billion annually) | Projected reductions exceeding $900 billion over a decade |
| Legislative Vehicle | 2025 reconciliation law (Senate political compromise) | 2025 reconciliation law (Federal healthcare spending cuts) |
| Primary Oversight Agency | Centers for Medicare & Medicaid Services (CMS) | CMS and State Medicaid Agencies |
| Distribution Mechanism | Cooperative agreements with substantial federal involvement | Statutory federal-state matching fund formulas |
Contraindications & When to Consult a Doctor
Future Outlook and Accountability
As states approach their impending reporting deadlines, the long-term success of the Rural Health Transformation Program hinges on balancing rapid federal disbursement with rigorous public oversight. With bipartisan concern mounting over administrative secrecy in several jurisdictions, health policy experts emphasize that robust data sharing is essential to protect program integrity. Ensuring that these federal dollars successfully reinforce vulnerable clinical networks will require sustained transparency from both statehouses and federal regulators through the conclusion of the funding cycle in 2032.

References
- Centers for Medicare & Medicaid Services (CMS). Notice of Funding Opportunity: Rural Health Transformation Program. September 2025.
- Bipartisan Policy Center. Policy Analysis, 2026.
- KFF Health News. $50B Rural Health Transformation Program Needs More Transparency. September 2026.
