
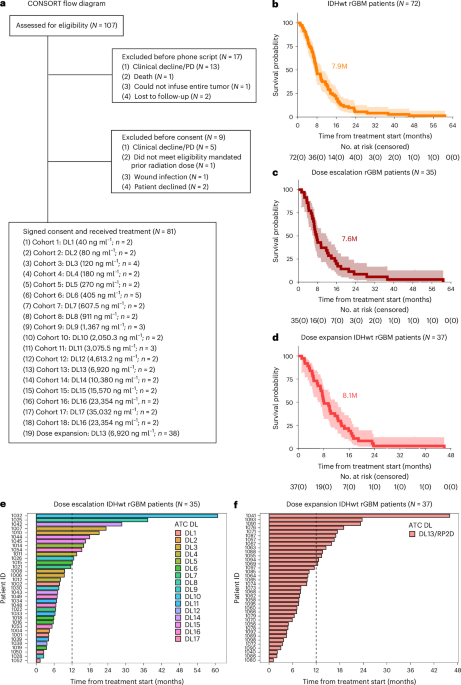
An experimental antibody-toxin conjugate targeting the epidermal growth factor receptor (EGFR) is being evaluated for patients with recurrent malignant glioma. Developed to address aggressive brain tumors expressing wild-type and variant III EGFR mutations, this targeted therapy aims to overcome the severe limitations of systemic drug delivery across the blood-brain barrier.
Decoding the Clinical Mechanism in Recurrent Glioma
Malignant gliomas, particularly glioblastoma, remain among the most lethal central nervous system tumors. Standard front-line therapy established by Stupp and colleagues relies on maximal surgical resection followed by radiation therapy and concurrent temozolomide chemotherapy. Yet, recurrence is nearly universal, and treatment options for relapsed disease are profoundly limited. According to epidemiological data from the Central Brain Tumor Registry of the United States (CBTRUS), primary brain and central nervous system tumors present persistent clinical challenges due to their infiltrative growth patterns and therapeutic resistance.
A primary driver of this resistance is genetic alteration within the epidermal growth factor receptor pathway. Amplifications and mutations of EGFR—most notably the constitutively active mutant known as EGFRvIII—are frequently expressed in high-grade gliomas. These alterations stimulate unchecked cellular proliferation and correlate with rapid early disease progression. Traditional small-molecule inhibitors and monoclonal antibodies have struggled in clinical evaluations against glioblastoma, often hindered by heterogeneous drug distribution and the selective permeability of the blood-brain barrier.
To bypass these physical hurdles, translational researchers engineered specialized immunotoxins and antibody-drug conjugates, such as the D2C7-based constructs and prior iterations like depatuxizumab mafodotin. These agents utilize precise targeting mechanisms to bind both wild-type and mutant EGFR proteins on tumor cells. Once bound, the antibody-toxin complex internalizes, delivering a cytotoxic payload directly into the malignant cell to induce apoptosis while sparing surrounding healthy neural parenchyma. Clinical exploration via convection-enhanced delivery—a technique utilizing positive-pressure micro-infusion directly into the tumor interstitium—has been studied to improve local drug distribution within the brain.
In Plain English: The Clinical Takeaway
- Targeted Payload Delivery: The therapy links an antibody that specifically recognizes mutated tumor proteins with a cell-killing toxin, reducing collateral damage to healthy brain tissue.
- Overcoming Anatomical Barriers: Because systemic chemotherapy often fails to cross into the central nervous system effectively, these trials investigate specialized local administration routes to maximize drug concentration at the tumor site.
- Clinical Investigation: Medical objectives center on establishing safety parameters, determining dosages, and monitoring adverse event profiles in patients with recurrent disease.
Evaluating these immunotoxins requires rigorous monitoring of safety endpoints, as localized central nervous system administration carries risks of peritumoral edema, localized inflammation, and neurotoxicity. Investigators continue to analyze pharmacokinetic profiles and patient-specific biomarker expression to identify which cohorts derive the most benefit from targeted antibody-toxin conjugates.
Contraindications & When to Consult a Doctor
Patients with recurrent malignant glioma being evaluated for clinical trials must undergo rigorous screening by neuro-oncology specialists. Contraindications typically include active systemic infection, severe unmanaged organ dysfunction, multifocal disease dissemination beyond the reach of local infusion catheters, or a lack of confirmed EGFR pathway alterations upon pathological review.
References
- Ostrom, Q. T. et al. CBTRUS statistical report: primary brain and other central nervous system tumors diagnosed in the United States in 2016–2020. Neuro-Oncology, 25, iv1-iv99 (2023).
- Stupp, R. et al. Radiotherapy plus concomitant and adjuvant temozolomide for glioblastoma. N. Engl. J. Med. 352, 987–996 (2005).
- Chandramohan, V. et al. Construction of an immunotoxin, D2C7-(scdsFv)-PE38KDEL, targeting EGFRwt and EGFRvIII for brain tumor therapy. Clin. Cancer Res. 19, 4717–4727 (2013).
- Ezzati, S. et al. Epidermal growth factor receptor inhibitors in glioblastoma: current status and future possibilities. Int. J. Mol. Sci. 25, 2316 (2024).
