
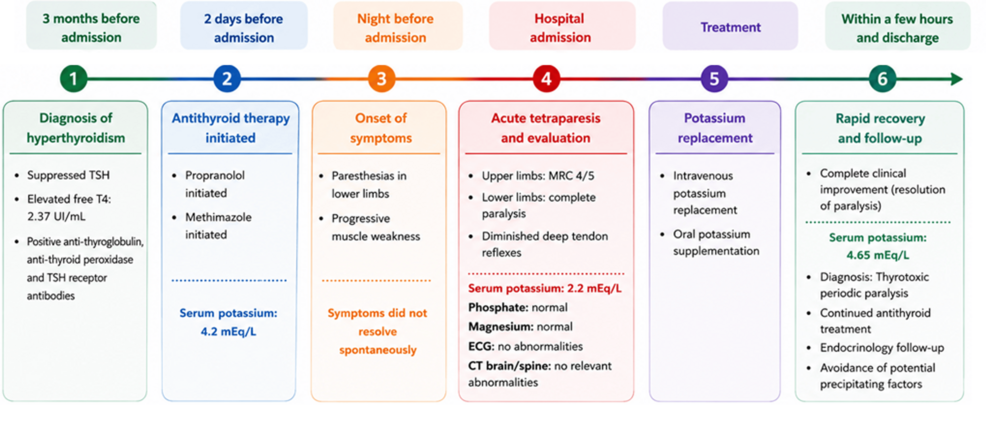
A 29-year-old man recently developed acute flaccid tetraparesis associated with severe hypokalemia, stemming from a rare and potentially life-threatening complication of hyperthyroidism documented in Cureus. The patient presented with the condition known as thyrotoxic hypokalemic periodic paralysis (TPP), which is usually associated with Graves’ disease.
Prompt potassium replacement resulted in rapid clinical and biochemical improvement for the patient. Medical literature notes that TPP is characterized by the triad of acute muscle weakness, hypokalemia, and thyrotoxicosis. The hypokalemia in these cases results primarily from a rapid intracellular shift of potassium rather than true depletion of total-body potassium. Excess thyroid hormone increases Na⁺/K⁺-ATPase activity and enhances β-adrenergic sensitivity, while genetic susceptibility involving genes such as KCNJ18, CACNA1S, and SCN4A also contributes to the condition.
Clinical Presentation and Diagnosis
Abnormal skeletal muscle ion channel function underlies periodic paralysis, an uncommon condition marked by repeated, temporary spells of muscle weakness or loss of function. While hereditary forms of hypokalemic periodic paralysis typically present during late childhood or adolescence with a mean age of onset of approximately 14 years, acquired forms like TPP predominantly affect young adult men. TPP is particularly prevalent in East and Southeast Asian populations, where its prevalence among patients with hyperthyroidism has been estimated at approximately one in 50, compared to approximately one in 500 to one in 1,000 in other populations.

Clinically, TPP presents with acute, transient, and typically reversible muscle weakness that is usually symmetrical and predominantly affects proximal muscles. The lower limbs are generally more severely affected than the upper limbs, and respiratory and ocular muscles are usually spared. However, severe attacks may result in respiratory failure or life-threatening cardiac arrhythmias. Because standard signs of thyrotoxicosis can occasionally be understated or completely missing, diagnosing the primary endocrine problem may be delayed.
Management and Differential Diagnosis
Establishing the diagnosis of TPP relies on the clinical presentation, the presence of thyrotoxicosis, severe hypokalemia, and rapid clinical improvement following potassium replacement. Awareness of this condition is essential for early diagnosis and appropriate management, given that delayed recognition may result in potentially life-threatening complications, including cardiac arrhythmias and respiratory failure.
The differential diagnosis for such presentations includes hereditary hypokalemic periodic paralysis and secondary causes of hypokalemia, particularly renal and gastrointestinal potassium losses. Renal tubulopathies such as renal tubular acidosis, Bartter syndrome, and Gitelman syndrome must also be considered, particularly when hypokalemia is persistent rather than associated with acute episodic weakness.
