
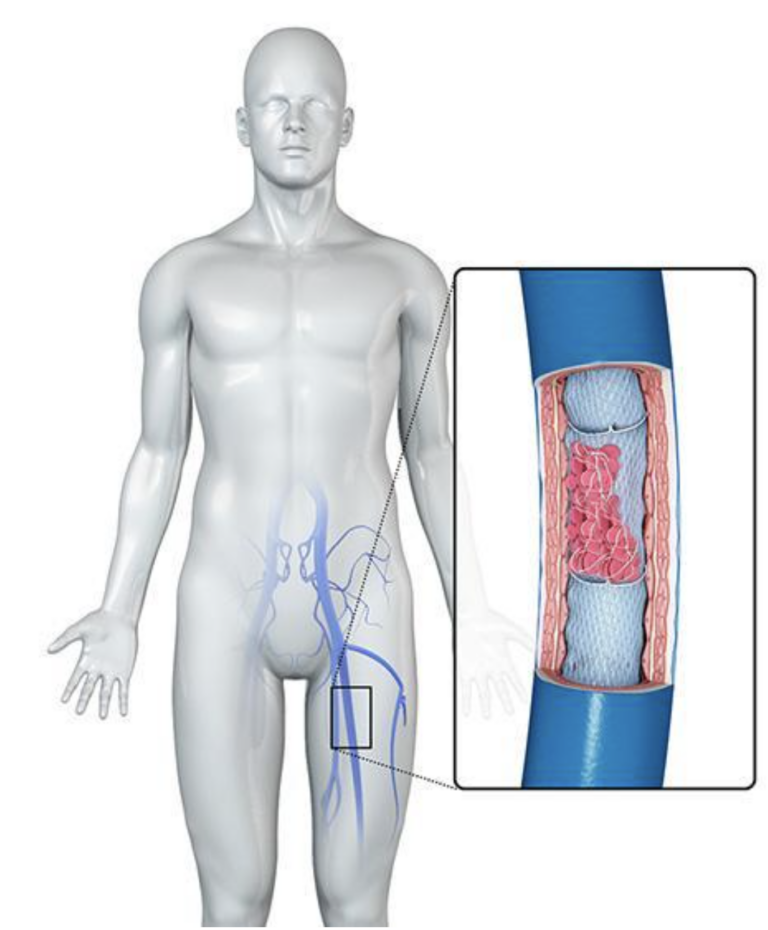
Deep vein thrombosis (DVT) is a potentially life-threatening medical condition affecting more than 300,000 individuals in the United States annually, according to information provided by Vegas Vascular Specialists. Within this category, thrombosis of an iliofemoral vein accounts for approximately 25% of all lower extremity DVTs. Iliofemoral DVT carries an elevated risk of pulmonary embolism (PE), limb malperfusion, and post-thrombotic syndrome (PTS) when compared to DVTs occurring below the knee.
Understanding Iliofemoral Deep Vein Thrombosis and Phlegmasia Cerulea Dolens
The condition typically affects patients who have an anatomic predisposition to venous stasis. A retrospective study of 56 patients presenting with acute iliofemoral DVT found that 45 patients, or 84%, had evidence of iliac vein compression on computed tomography (CT) venography. The most well-described scenario involves May-Thurner syndrome, which is the compression of the left iliac vein situated between the right iliac artery and a vertebral body. However, extrinsic compression can occur in either leg through mechanisms such as pelvic malignancy or trauma.
Virchow’s Triad and Clinical Presentations
In addition to anatomic predisposition, the majority of patients with iliofemoral DVT possess at least one additional risk factor for venous thrombosis. These align with Virchow’s triad of thrombogenesis, which encompasses endothelial injury, hypercoagulability, and stasis. Common clinical examples include the postoperative state, prolonged immobility from travel or hospitalization, malignancy, pregnancy, and inherited hypercoagulable conditions.
Patients with acute DVT commonly present with lower extremity pain and swelling. Physical examinations may reveal a palpable cord, ipsilateral edema, erythema, or venous distension. In rare instances, patients may present with evidence of arterial insufficiency arising from massive iliofemoral DVT. This life-threatening condition is known as phlegmasia cerulea dolens and occurs as a direct consequence of severe venous obstruction. As swelling progresses, compartment syndrome and arterial compromise can ultimately lead to venous gangrene. Medical literature indicates that prompt venous recanalization through catheter-directed thrombolysis and thrombectomy is indicated to prevent limb loss, circulatory collapse, and death.
Long-Term Complications and Diagnostic Strategies
Long-term complications of DVT include persistent lower extremity edema, venous claudication, hyperpigmentation, and ulceration, which are collectively known as post-thrombotic syndrome (PTS). Mediated by venous hypertension and valve incompetence stemming from persistent iliofemoral obstruction, PTS affects up to 50% of patients following an incident iliofemoral DVT. This syndrome is associated with a reduced quality of life and increased health care expenses. A retrospective study of 26,958 patients with DVT or PE demonstrated that the development of PTS was linked to a 32% increase in annualized total health care costs, largely driven by outpatient resource utilization and the management of venous ulcers.

Because many patients presenting with lower extremity pain and swelling do not actually have a DVT, stratifying patients according to their pretest disease likelihood is a fundamental element of a cost-effective diagnostic approach. The Wells score incorporates nine variables to determine whether a patient maintains a low, moderate, or high probability of having a DVT. For patients with a low or moderate pretest probability, a negative D-dimer test effectively rules out the diagnosis. Current guidelines favor D-dimer testing in these populations, although ultrasound may be utilized when comorbid conditions confound the interpretation of a positive result in patients with a high probability of DVT, as outlined by Vegas Vascular Specialists.
Worth a look
- CDC Study: Racial and Ethnic Disparities Persist in Cigarette Smoking Rates
- Porto San Giorgio: Scheduled Environmental Treatment (Sept 22)
- Understanding Infusion Reactions in Cancer Treatment: Common Symptoms, Causes, and Essential Information for Patients – Cancer Treatment Side Effects and Complications (archyworldys.com)
