
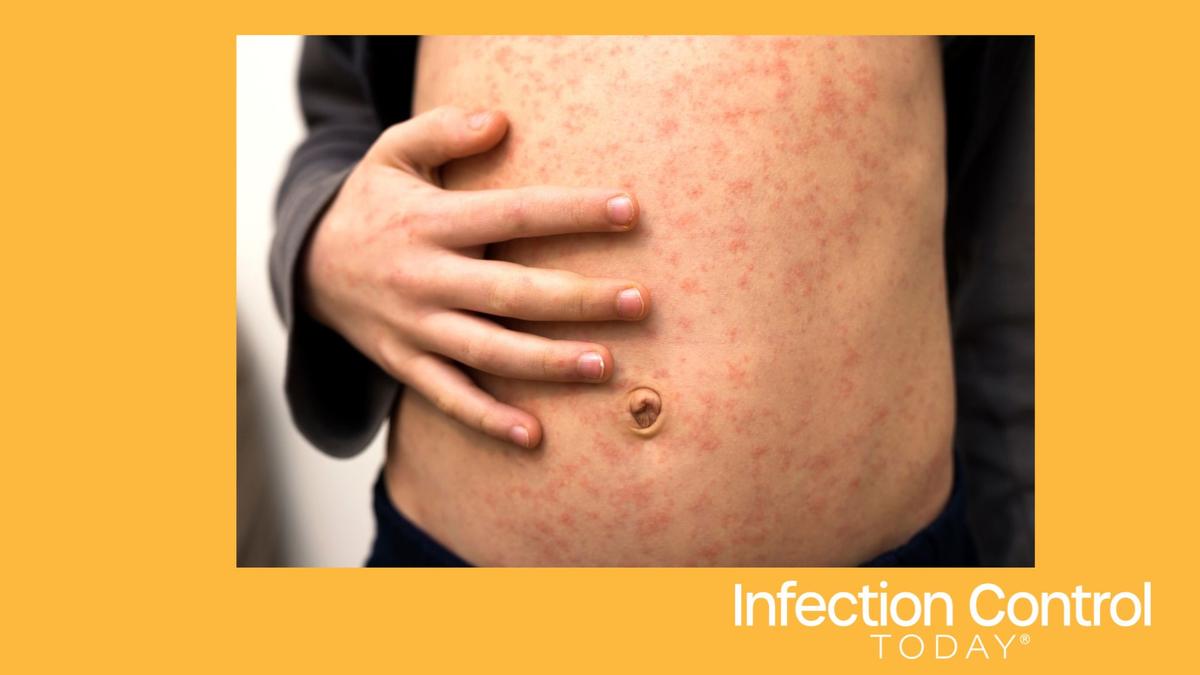
The United States has lost its measles elimination status, triggering widespread public health concern following the loss of this preventative triumph. This resurgence demands urgent community-wide action to close vaccination gaps, address access barriers, and rebuild public trust in the MMR vaccine.
Measles is a highly contagious viral illness, distinct from many other diseases in both its severity and its capacity to spread. One individual can transmit the virus to up to 9 out of 10 susceptible close-contact individuals. This extreme contagiousness means that community immunity—the collective protection offered by high vaccination rates—is the primary defense against outbreaks.
The global public health message is clear: the rate of new infections increases proportionally with the total number of infectious individuals and the total number of susceptible, unvaccinated people in a community. Therefore, community members must recognize that their personal immunization is an act of protecting their neighbors.
#DYK: In 1993, the Clinton administration established the Vaccines for Children program, expanding access to lifesaving vaccines for children across the country. The @NYTimes looks back at the decades of public health work that led to measles elimination in the U. S.:…
Measles Demands 95% Vaccination to Prevent Outbreaks
- Measles is highly contagious: It can spread rapidly, meaning high vaccination rates (about 95%) are required to stop it, which is higher than the coverage needed to control other diseases, like COVID-19 (early estimates of 70 to 80%).
- Gaps cause outbreaks: When vaccination rates drop—even slightly—it creates “susceptible pockets” that allow the virus to find hosts and seed wider outbreaks.
- Trust and Access matter: Solutions to eliminate outbreaks require addressing practical barriers like scheduling, transportation, and misinformation, not just providing the vaccine itself.
Tracking Measles Transmission and Loss of Elimination Status
The loss of measles elimination status is currently a major regional health concern. The Pan American Health Organization (PAHO) announced on November 17, 2026, that measles has reestablished regular transmission in the United States. This follows a period where the virus circulated uninterrupted for 12 months or more, which is the primary criterion for maintaining elimination status within the region, according to PAHO.
“This is a serious warning for our Region, but it is not an irreversible setback,” PAHO Director said.
Saving babies is the lowest common denominator for a civilized society. Babies can’t get vaccinated. When measles surges, they are defenseless. This is what happens when we appoint an anti-science grifter to the highest public health role in the country. https://t.co/skGrIM3JjL
The American experience is particularly stark. Experts report that many US doctors, who remember measles as a historical disease, are now seeing it return. “Measles was like a historical disease, and it was something that you just didn't see in the United States,” Trahern W. Jones, a pediatric infectious disease specialist in Utah, told AFP.
This resurgence has resulted in significant health consequences, including reported permanent, irreversible brain injury that may not be apparent for years, according to Jessica Ericson, a pediatric infectious disease physician in Pennsylvania.
The scale of the problem is evidenced by the total number of cases and deaths. As of 13 November 2026, the Americas have reported 58,213 confirmed measles cases and 82 deaths, compared with 12,806 cases during the same period last year, according to the Pan American Health Organization (PAHO). This alarming trend highlights the urgency of strengthening surveillance and outbreak response across the continent.
The U. S. has officially lost its status as a country where #measles is eliminated 😔https://t.co/MHMEwYuEU5 via @KFFHealthNews with #MeaslesCollaborative Executive Director @InfectiousPS
Logistical Friction and Trust Issues Hinder MMR Uptake
Closing vaccination gaps is not merely a medical issue; it is a complex public health challenge rooted in social structures and practical life hurdles. Researchers have identified several friction points that prevent individuals from completing their required two doses of the MMR (measles, mumps, and rubella) vaccine.
One critical barrier is the logistical friction: work schedules, childcare availability, and transportation issues. Second doses that go uncompleted suggest emerging obstacles to getting vaccinated (eg, due to busy schedules or accessing new information).
Trust is another profound issue. Social networks and past healthcare experiences heavily influence vaccine-seeking behavior. When public health messaging is not open and ongoing, or when conflicting information is present, people rely on their families and friends to shape their decision-making. Experts note that misinformation, including concerns tied to the initial vaccine rollout, can deeply affect public health trust.
For instance, when the COVID-19 vaccines first became available, the practical obstacles to getting vaccinated produced visible effects, including a lack of options for individuals to pick the vaccine type they preferred and lengthy waits in line.
People split into 2 groups: those who remained at home until they could pick their vaccine, and those who pursued every available strategy to get a dose as fast as possible. This demonstrates how the perceived control over the healthcare process directly impacts compliance.

| Metric | Measles Immunity Target | COVID-19 Initial Target (Early) | US Current Vaccination Rate (2025-26 School Year) |
|---|---|---|---|
| Required Coverage for Herd Immunity | ~95% | 70-80% | 92.4% (National Low) |
| Reported Annual Cases (2025-26) | High/Increasing | Specific to Variant | Reported Outbreaks in 46 US States |
Strategies for Closing Measles Vaccination Gaps
Public health teams must look beyond broad national averages and instead identify specific, high-risk populations and geographical pockets. As the Pan American Health Organization (PAHO) recommends, countries must use risk assessment tools to pinpoint high-risk municipalities and populations, prioritizing the most vulnerable communities.
To combat logistical barriers and address community-specific preferences, health systems should offer temporal flexibility. If a community prefers pharmacies to hospitals due to easier access, supply must be strategically located to meet that demand. Hybrid options—such as allowing individuals to choose between their preferred vaccine type and the earliest available dose—have been shown to increase per-capita vaccination rates in certain trials.
The U. S. has lost its measles elimination status. Swipe to learn what this means for LA County and what you can do to keep yourself and your family protected. Learn more about measles at: https://t.co/kZEc5168rX pic.twitter.com/LxpU38yNJ0
Effective strategies must also target missed dose opportunities. For example, when a second dose is missed, it often signals new frictions, such as busy schedules. The response to this is targeted outreach that explains the critical need for the about 95% community coverage needed for measles relative to most other diseases.
Conversely, identifying missed first doses is the domain of community leaders, who can implement interventions like integrating vaccination checks into routine entry points like school registration or sick visits.
- Special Consideration: Individuals who are pregnant should not receive the MMR vaccine, as it is a live, attenuated virus. Guidance for pregnant individuals regarding immunity status must come from a healthcare professional.
- When to Consult: If you or your child develops a rash, fever, cough, runny nose, or red eyes, and you are in an area with known measles transmission, contact a healthcare provider immediately. Do not self-diagnose or wait for symptoms to worsen.
Monitoring Success Through Granular Data
To ensure that efforts to close vaccination gaps produce sustained, equitable improvements, communities must move past aggregate data. They must track coverage at a socioeconomic and geographical level—by “pockets.” This ensures that improvement is not just generalized, but that the gap between target groups is narrowing.
The ultimate measure of success is epidemiological. The signal that public health efforts have genuinely worked is a decline in the number of new infections and a reduction in the size of the susceptible, unvaccinated population.
The tracking of measles titers in older adults, as analyzed by Truveta Research, shows a massive spike in testing rates—peaking at 734% in 2025—indicating high public concern and a need for clarity on immunity status.
The path back to elimination, which was successfully achieved in the Americas in 2024 after addressing endemic transmission in Venezuela and Brazil, requires a sustained commitment to both vaccination and strong surveillance. This commitment involves actively engaging in grassroots trust-building and ensuring that clinical science is translated into clear, accessible public health intelligence for every community, as asserted by the Pan American Health Organization (PAHO).
US loses measles-free status after continued spread of the disease, WSJ reports https://t.co/8A40pAcWmv
References
- Pan American Health Organization (PAHO): Regional monitoring and re-verification commissions, 2026.
- Infection Control Today: Analysis of vaccination barriers and community immunity targets.
- KFF Health News: Reporting on the loss of US measles elimination status in 2026.
- Contagion Live: Data analysis of measles immunity testing among adults over 50, 2026.
More on Pan American Health Organization
We eliminated measles in the U. S. in 2000. Now, we've officially lost that status. Here's what happened, why it matters and what you can do about it. 🧵
The United States has lost its measles elimination status, the Pan American Health Organization formally announced on Tuesday. PAHO, a part of the World Health Organization, made the decision after reviewing evidence and determining that the measles virus has been continuously… pic.twitter.com/f1s6VHkRzz
📣As of Nov 17, 2026, the U. S. no longer holds measles elimination status. Measles cases are at a 30-year high, with outbreaks, hospitalizations, and deaths occurring across the country. Learn more https://t.co/yuIPqGkXrd 1/7#MMRVaccine #VaccinesSaveLives #WeArePublicHealth pic.twitter.com/1SzIU37KFN
