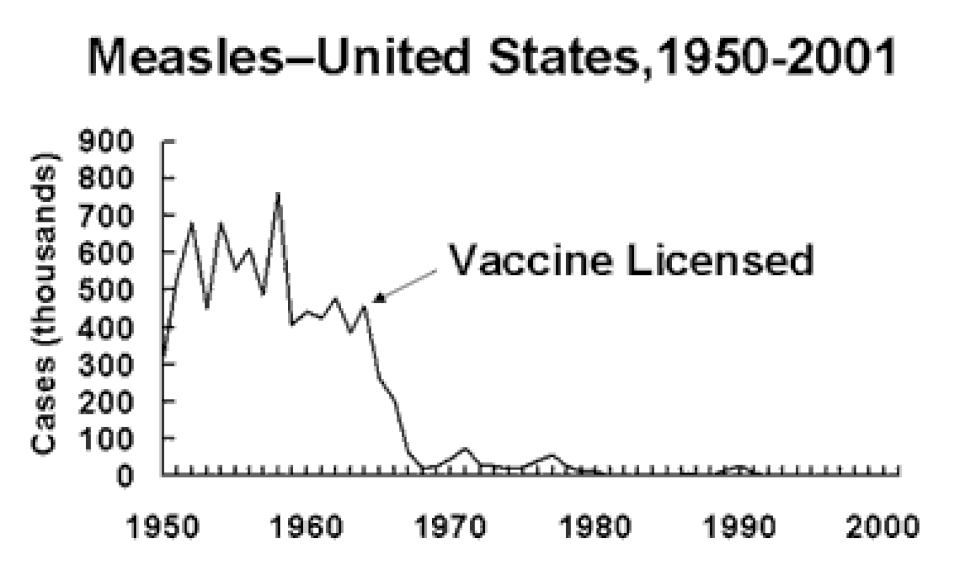
The United States lost its 26-year measles-free status after the Pan-American Health Organization revoked it on November 14. Driven by declining vaccine uptake and changing immunization schedules, health experts warn that the airborne viral disease is now spreading because community immunity programs have faltered.
The United States has had its measles-free status officially revoked by the Pan-American Health Organization, marking the end of a 26-year streak. Measles is a highly contagious and airborne viral disease with no standard treatment, leaving modern medicine largely dependent on supportive care when severe symptoms arise.
The response to the virus has historically been one of public health’s greatest success stories. Two doses of MMR vaccines administered in early childhood provide lifetime protection for the vast majority of the population against the measles virus.
U.S. loses measles-elimination status, WSJ reports — NBC News
How the MMR Vaccine Works
Mechanism of Action: The MMR vaccine trains the immune system to recognize and neutralize the measles virus safely without causing the actual disease.
Herd Immunity Threshold: High community vaccination rates are required to protect vulnerable infants who are too young to receive their first shot.
Supportive Care Limits: Because no antiviral treatment cures active measles, prevention through vaccination remains the only reliable defense against brain inflammation and death.
Vaccine Schedules Have Changed
Dr. Aaron Milstone, a professor of Pediatrics at Hopkins specializing in infectious disease, discussed the current crisis in an interview with The Johns Hopkins News-Letter
. As a member of the American Academy of Pediatrics, Milstone highlighted how institutional guidance has fractured in recent years.
“The American Academy of Pediatrics now provide the vaccine schedule that many states are pointing to since the CDC’s CHIP schedule has… diverted from other recommended schedules over the last two years, so that’s the first time in decades where our schedules have been different. And since it’s changed, I think people are now referring to some of the professional societies for vaccine recommendations instead of the CDC,” Milstone told The Johns Hopkins News-Letter.
Milstone pointed to confusion introduced by the Trump administration regarding necessary vaccination schedules and procedures. He explained that decades of measles elimination resulted from consistent program implementation.
US loses its measles elimination status — WKYC Channel 3
“The reason we didn’t have measles in the U.S. for decades was because of the success of the vaccine program. The reason that we are having sustained spread now is because that program has faltered. So this is completely due to decay in vaccine uptake in the United States,” Milstone told The Johns Hopkins News-Letter
.
Vulnerable Populations and the New Landscape
School-age children form the primary demographic affected by the current uptick, though resistance to vaccination poses a broader community risk. No viable curative treatments exist, leaving clinicians reliant on hydration and supportive care as they face potential neurological complications like brain inflammation.
Milstone said that medical professionals are confronting an unfamiliar epidemiological environment in the United States. Historically, widespread childhood contraction meant young adults rarely caught the virus.
United States loses measles elimination status after more than 20 years — CBS Philadelphia
“I think we’re unfortunately going to learn more from measles now because historically… we didn’t have lots of young adults getting measles infections. They had it as kids because everyone got measles. So now we’re kind of at a new time where we’re going to be learning more about measles in the 21st century in a country like the United States, as opposed to in a low and middle income country where we still see measles spreading,” Milstone told The Johns Hopkins News-Letter.
Metric
Historical Standard
Current Status (2026)
US Measles Status
Eliminated (26-year streak)
Revoked by PAHO (Nov. 14)
Primary Prevention
Two-dose MMR schedule
Faltering uptake in isolated pockets
Target Demographics
Historically young children
Expanded risk across under-vaccinated groups
Targeting Resources and Community Advocacy
Parents of infants too young for inoculation face rising exposure risks during travel and daily activities. Addressing these gaps will require sustained effort rather than short-term fixes.
“It’s gonna be a marathon. It’s gonna be the long process of trying to increase vaccine uptake among the population. And I think what’s important to note is if you look in Maryland, the rates of the vaccine in kids entering kindergarten is still very high. Those numbers don’t capture kids who are homeschooled or kids in communities that are more isolated… We have to figure out how we can target resources and effort towards communities that we know have a higher proportion of under vaccinated people because that’s where the biggest risks are right now,” Milstone told The Johns Hopkins News-Letter
.
Milstone urged students and community members to actively engage in vaccine advocacy and education. He emphasized that combating misinformation requires everyday ambassadors willing to listen and have constructive dialogues.
“Hopkins is filled with students that are young and idealistic and are interested in public health. A lot of people hear about measles and think, ‘oh, this isn’t there’s nothing I can do because I’ve gotten my vaccine, I am protecting my community’ but I think that what all people have to start remembering is that anyone can be an advocate for vaccine education… try to listen, actively listen, and have dialog with people in their community or in other communities that are concerned about vaccines with measles, and serve as everyday ambassadors… They don’t all have to be people like me. You know, the people that spread misinformation are not scientists… We need an army of people to combat misinformation about vaccines and anti-science,” Milstone told The Johns Hopkins News-Letter
.
When to Seek Medical Help
Patients exhibiting early symptoms—including high fever, cough, coryza, conjunctivitis, and a characteristic maculopapular rash—must contact a healthcare provider immediately before visiting a clinic or hospital waiting room.
References
Pan-American Health Organization (PAHO) / World Health Organization
Centers for Disease Control and Prevention (CDC) – Measles Vaccination Guidelines
The Johns Hopkins News-Letter – Interview with Dr. Aaron Milstone
Priya Deshmukh
Senior Editor, Health
Deshmukh is a practicing physician and renowned medical journalist, honored for her investigative reporting on public health. She is dedicated to delivering accurate, evidence-based coverage on health, wellness, and medical innovations.