
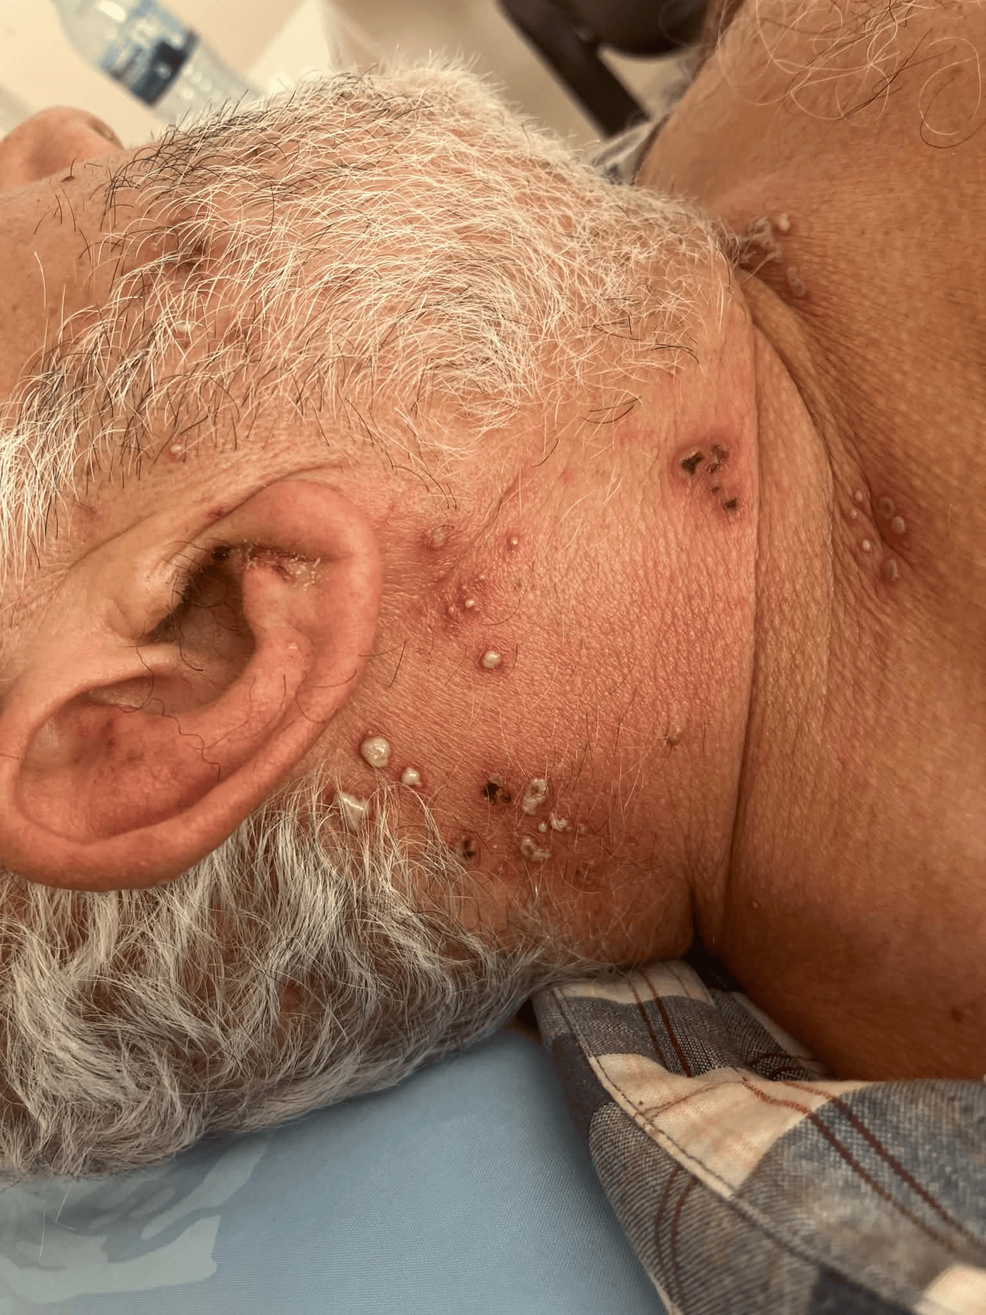
A 67-year-old man developed severe primary varicella-zoster virus meningitis accompanied by dual cranial neuropathies, including right peripheral facial nerve palsy and right hypoglossal nerve palsy.
In Plain English: The Clinical Takeaway
What happened: A 67-year-old man developed chickenpox that spread to his central nervous system, causing meningitis and paralyzing nerves controlling his face and tongue.
Why it was dangerous: Because he had post-traumatic asplenia, his immune system struggled to clear the virus, leading to severe inflammation.
Clinical Presentation and Emergency Department Admission
The patient presented to the emergency department on the fifth day of his illness exhibiting a severe headache, progressive facial asymmetry, speech difficulty, and a widespread skin eruption. His medical history included secondary post-traumatic asplenia and essential hypertension. Five days prior to admission, he experienced a sudden, severe headache initially blamed on cold air exposure. By the second day, a polymorphic vesicular rash appeared on his neck before spreading to his scalp, face, chest, and upper extremities. By days three and four, he developed acute facial asymmetry and mild dysarthria, prompting emergency medical services activation.
Upon admission, the patient had a body temperature of 38.3°C, a heart rate of 105 beats per minute, a blood pressure of 140/75 mmHg, and an oxygen saturation of 95% on ambient air. A neurological examination revealed an obtunded state with delayed responsiveness, pronounced nuchal rigidity, and positive Kernig’s signs bilaterally. Cranial nerve evaluations uncovered a right-sided peripheral facial nerve palsy characterized by lagophthalmos and sluggish corneal reflexes, alongside soft palate weakness. Tongue protrusion showed a distinct rightward deviation, indicating a concurrent right hypoglossal nerve palsy.
Diagnostic Imaging and Cerebrospinal Fluid Analysis
An initial non-contrast computed tomography scan of the head ruled out acute intracranial hemorrhages or space-occupying lesions. A brain magnetic resonance imaging scan without contrast revealed a small, non-specific gliotic focus in the right frontal lobe without acute parenchymal lesions. Contrast-enhanced magnetic resonance imaging of the brain revealed localized leptomeningeal enhancement without brainstem or parenchymal involvement.
A lumbar puncture yielded clear cerebrospinal fluid showing moderate lymphocytic pleocytosis with 267 cells per microliter and an elevated protein level of 1.74 grams per liter, with normal glucose concentration. Cerebrospinal fluid multiplex polymerase chain reaction testing confirmed varicella-zoster virus DNA while ruling out herpes simplex virus types 1 and 2.
| Parameter | Admission (Day 5) | Treatment Day 10 | Clearance (Day 14) | Discharge (Day 19) | Reference Range |
|---|---|---|---|---|---|
| CSF White Blood Cells | 267 cells/µL | 100 cells/µL | 52 cells/µL | — | <5 cells/µL |
| CSF Protein | 1.74 g/L | 1.15 g/L | 0.65 g/L | — | 0.15–0.45 g/L |
| CSF Glucose | Normal | Normal | Normal | — | 2.2–3.9 mmol/L |
| Serum Creatinine | 102.9 µmol/L | 156.0 µmol/L | 79.24 µmol/L | 107.7 µmol/L | 62–115 µmol/L |
Antiviral Therapy and Inpatient Recovery
Short-term adjunctive corticosteroids were added to mitigate neuroinflammatory and meningeal edema, while blood pressure was closely regulated using his baseline antihypertensive regimen. Clinical improvement became evident as headache intensity decreased by days seven to eight, meningeal signs resolved by day 10, and cutaneous lesions fully crusted over by day 19.
Parenteral therapy was followed by oral valacyclovir at 1,000 milligrams three times daily for an additional two weeks to complete a four-week course. Follow-up cerebrospinal fluid analysis on treatment day 10 showed a 2.5-fold reduction in pleocytosis down to 100 cells per microliter, and a final control puncture on day 14 confirmed marked inflammatory clearance with pleocytosis decreasing to 52 cells per microliter.
Contraindications & When to Consult a Doctor
Patients with underlying renal impairment, immunosenescence, or asplenia who present with acute headache, unexplained focal neurological deficits, or a progressive vesicular rash must seek emergency medical evaluation immediately. Delayed antiviral intervention in immunocompromised individuals significantly increases the risk of permanent cranial nerve damage and prolonged subacute neuropathic pain.
Discharge Status and Persistent Neuralgia Management
Prolonged inpatient management remained necessary due to the patient’s high-risk status with post-traumatic asplenia and severe neuroinvasive disease involving dual cranial neuropathies. By day 19, systemic parameters stabilized, cutaneous lesions crusted over completely, and meningeal signs disappeared. Residual right facial asymmetry and rightward tongue deviation persisted alongside localized right-sided facial neuropathic pain. Oral pregabalin was initiated and titrated for neuralgia control, and the patient was discharged home in stable condition with scheduled outpatient follow-up.
