
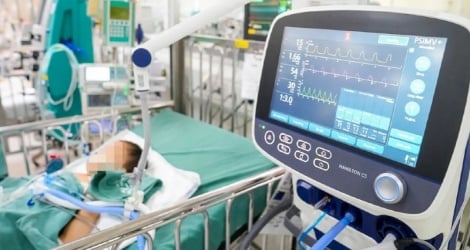
An otherwise healthy four-year-old girl has died from acute necrotizing encephalopathy linked to Influenza A just two days after symptom onset, highlighting severe neurological risks that can emerge rapidly in children, the National Children’s Hospital reported.
In Plain English: The Clinical Takeaway
- Acute Necrotizing Encephalopathy (ANE): A rare, fast-moving brain disease triggered by certain viral infections, including the flu, that causes severe tissue damage.
- Blood-Brain Barrier: A protective biological wall that shields the brain from harmful substances in the blood. A hyperactive immune response can damage this barrier, leading to dangerous swelling.
- Neurological Red Flags: Sudden lethargy, severe drowsiness, disorientation, behavioral changes, or seizures in a child with the flu require immediate emergency medical care rather than waiting for a fever to break.
Fatal Neurological Complications in a Healthy Four-Year-Old
The four-year-old patient initially presented with a two-day history of high fever, cough, and a sore throat. Her condition deteriorated rapidly, plunging her into a coma shortly after admission. Despite intensive clinical intervention, the brain injury progressed unchecked, and she died two days later.
This case highlights that influenza in pediatric populations is not strictly confined to the respiratory tract. Severe complications can manifest very early in the course of the illness, striking children with no prior underlying medical conditions. While respiratory issues like secondary bacterial infections and pneumonia are standard clinical concerns, viral pathogens can occasionally trigger catastrophic central nervous system events.
Understanding Acute Necrotizing Encephalopathy
Acute necrotizing encephalopathy has been recognized in medical literature since 1995. It typically develops several days following the onset of a fever and advances with alarming speed. Clinical data indicate a mortality rate of approximately 30% to 40% among affected children.
| Clinical Feature | Medical Observation |
|---|---|
| Primary Pathogen | Influenza A virus |
| Condition Identified | Acute Necrotizing Encephalopathy (ANE) |
| Mortality Rate | 30% to 40% in diagnosed pediatric cases |
| Long-Term Risks | Motor deficits, cognitive impairment, loss of self-care capacity |
The underlying mechanism of action driving these rapid brain injuries remains under active investigation. A leading hypothesis points toward a cytokine storm—an overactive immune response following viral entry that floods the body with inflammatory mediators. These molecules compromise the integrity of the blood-brain barrier, triggering cerebral edema and tissue destruction.
Contraindications & When to Consult a Doctor
Virostatika (antiviral medications) should only be administered under strict medical supervision, particularly for toddlers, children with pre-existing chronic illnesses, or severe presentations.
Parents and caregivers must seek immediate emergency evaluation if a child with the flu exhibits neurological warning signs. These include extreme lethargy, difficulty waking up, confusion, unusual behavioral shifts, focal limb weakness, an abnormal gait, or seizures. Respiratory distress, persistent chest pain, bluish discoloration of the lips, and signs of severe dehydration warrant urgent medical intervention.
Preventative Strategies and Vaccination Protocols
Transmission occurs primarily via respiratory droplets and secretions, making close-quarters environments like classrooms and daycare centers high-risk vectors. Vulnerable populations include children under five, adults over sixty-five, pregnant women, and individuals with chronic conditions or compromised immune systems.
Beyond rigorous hand hygiene and avoiding shared drinking utensils, annual seasonal influenza vaccination remains a primary defense against severe hospitalizations and mortality. According to medical professionals at the Long Chau Immunization Center, current formulations protect against dominant strains including A/H1N1, A/H3N2, and lineage B strains. Pediatric doses are recommended starting at six months of age, with a two-dose primary series required for young children receiving their initial immunization.
References
- Clinical case reports on pediatric influenza complications.
- Long Chau Immunization Center. Seasonal influenza vaccine strain coverage and administration guidelines.
- Infectious Diseases Association of Ho Chi Minh City. Clinical guidance on neurological complications of influenza in children.
