
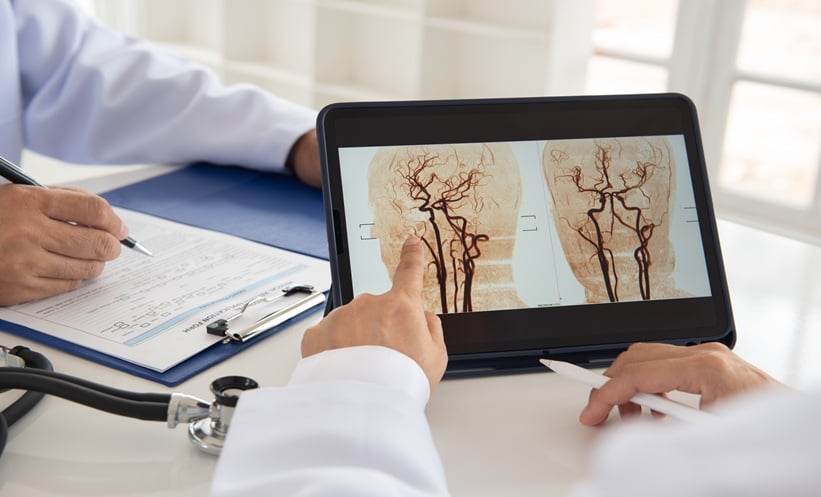
Recent clinical findings regarding unruptured intracranial aneurysms indicate that immediate intervention does not necessarily confer a superior protective benefit over carefully monitored conservative management. Published in this week's medical literature, the data forces a critical re-evaluation of surgical versus watchful-waiting strategies in neurovascular care.
In Plain English: The Clinical Takeaway
- Watchful Waiting: For many patients with small, unruptured brain aneurysms, closely monitoring the condition with regular imaging may be just as safe as immediate surgery.
- Risk Evaluation: The physical risks associated with invasive preventive procedures sometimes outweigh the statistical likelihood of the aneurysm rupturing.
- Personalized Care: Treatment decisions now require a deeply individualized approach, weighing aneurysm size, anatomical location, and patient age rather than relying on a universal timeline.
Re-evaluating Neurovascular Intervention Protocols
Managing unruptured brain aneurysms has long presented a delicate clinical dilemma for neurosurgeons and vascular specialists. The primary objective is preventing subarachnoid hemorrhage, a catastrophic event associated with high mortality rates. Yet, surgical clipping and endovascular coiling carry their own procedural morbidity and mortality risks. According to recent data highlighted in the European Medical Journal (EMJ), rushing into intervention based strictly on a rigid timeline fails to demonstrate a definitive statistical advantage for every patient demographic.
This insight shifts the conversation from immediate action to risk stratification. Clinical trials evaluating long-term outcomes show that patient selection remains the cornerstone of modern neurovascular medicine. Anatomical factors such as the aspect ratio of the sac, wall irregularity, and hemodynamic stress must be balanced against the inherent risks of vascular access and craniotomy.
Epidemiological Data and Regulatory Landscape
Unruptured intracranial aneurysms affect an estimated 3% to 5% of the global population, though the vast majority never rupture during a person’s lifetime. Regulatory bodies like the U.S. Food and Drug Administration (FDA) and the European Medicines Agency (EMA) continuously monitor the safety profiles of endovascular devices, flow diverters, and microcoils used in these interventions. However, regulatory approval of a medical device does not dictate the optimal therapeutic window for its deployment.
Funding transparency is vital in interpreting these findings. Large-scale neurovascular registries and trial cohorts are frequently supported by a combination of public health grants—such as those from the National Institutes of Health (NIH)—and institutional research funding from medical device manufacturers. Maintaining strict methodological independence ensures that clinical evaluations of treatment timing remain objective, uninfluenced by commercial pressures.
| Management Strategy | Primary Clinical Advantage | Associated Primary Risk |
|---|---|---|
| Conservative Surveillance (Watchful Waiting) | Avoids immediate procedural complications; preserves vessel integrity | Anxiety regarding potential rupture; requires strict follow-up compliance |
| Immediate Endovascular Coiling | Minimally invasive approach; shorter initial recovery time | Potential need for retreatment; coil compaction over time |
| Surgical Clipping | High long-term durability; eliminates the aneurysm sac permanently | Invasive craniotomy; higher short-term perioperative risk |
Contraindications & When to Consult a Doctor
Decisions regarding aneurysm treatment must be made in consultation with a qualified neurosurgeon or vascular neurologist. Patients with severe systemic comorbidities, unmanaged coagulopathies, or unfavorable vascular anatomy may have strict contraindications for elective surgical or endovascular interventions. Furthermore, any sudden onset of a “thunderclap headache”—described as the worst headache of one’s life—alongside neurological deficits, visual disturbances, or acute neck stiffness, warrants emergency medical evaluation regardless of prior monitoring status.
The Future of Individualized Patient Care
Ultimately, the latest data emphasizes that timing is only one variable in a complex equation. As imaging modalities improve and predictive algorithms become more refined, clinical practice is moving steadily away from one-size-fits-all timelines. By integrating rigorous peer-reviewed evidence with personalized patient risk profiles, medical teams can better navigate the fine line between preventive intervention and conservative observation.
References
- European Medical Journal (EMJ): Clinical updates on neurovascular interventions and aneurysm management timelines.
- The Lancet Neurology: Longitudinal studies on the natural history of unruptured intracranial aneurysms.
- Journal of Neurosurgery: Comparative outcomes of endovascular coiling versus microsurgical clipping.
- Centers for Disease Control and Prevention (CDC): Public health data on cerebrovascular incidents and risk factor management.
Disclaimer: Dr. Priya Deshmukh and Archyde provide this report for informational and educational purposes only. It does not constitute formal medical diagnosis, treatment advice, or a substitute for professional clinical consultation. Always seek the advice of your physician or qualified health provider with any questions regarding a medical condition.
