
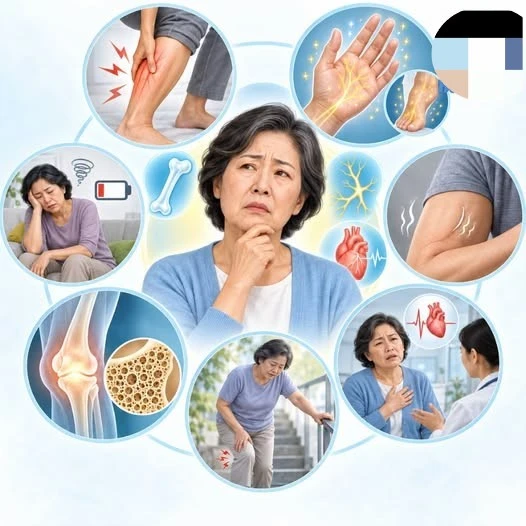
Persistent fatigue, numbness or tingling in the hands and feet, and painful muscle spasms are classic physiological indicators of hypocalcemia, or low blood calcium levels. When systemic calcium drops below normal physiological thresholds, neuromuscular excitability spikes, triggering these distinct clinical symptoms that require timely medical evaluation.
Recent public health discussions and clinical observations highlight a growing need for greater awareness regarding how subtle nutritional and metabolic imbalances manifest physically. While many individuals brush off occasional muscle cramps or daytime exhaustion as mere stress or dehydration, these signs can point toward an underlying disruption in mineral homeostasis regulated by the parathyroid glands and vitamin D pathways.
In Plain English: The Clinical Takeaway
- Neuromuscular Signalling: Calcium ions are essential for muscle contraction and nerve signal transmission; a deficit causes nerves to misfire, resulting in spasms and the sensation of “pins and needles” (paresthesia).
- Systemic Fatigue: Chronic low calcium forces cellular energy systems to work harder, translating to pervasive, unrelenting exhaustion that sleep alone cannot fix.
- Diagnostic Necessity: Self-diagnosing mineral deficiencies with over-the-counter supplements can mask serious endocrine or renal issues; a definitive serum blood test is always required.
The Cellular Mechanism of Paresthesia and Spasms
To understand why a lack of calcium causes physical distress, we must look at the cellular level. Calcium acts as a crucial gatekeeper for voltage-gated sodium channels in nerve membranes. According to physiological research published in the National Institutes of Health PubMed database, extracellular calcium stabilizes these channels.
When serum calcium levels decline—a state known clinically as hypocalcemia—this stabilizing effect diminishes rapidly. As a result, motor and sensory neurons become hyperexcitable, firing spontaneously without proper central nervous system commands. This uncontrolled neuronal discharge manifests clinically as tetany, involuntary muscle contractions, and paresthesia, which patients commonly describe as numbness or a prickly sensation in the extremities.
Epidemiological Context and Regulatory Oversight
Mineral deficiencies do not occur in a vacuum. Public health agencies, including the Centers for Disease Control and Prevention (CDC), track nutritional intake across demographics to identify vulnerable populations. Dietary surveys indicate that individuals with restricted diets, malabsorption syndromes like celiac disease, or chronic kidney disease face significantly higher risks of developing subclinical or acute hypocalcemia.
Regulatory bodies such as the U.S. Food and Drug Administration (FDA) and the European Medicines Agency (EMA) closely monitor dietary supplement safety and prescription calcium formulations. Clinical guidelines emphasize that treating hypocalcemia requires addressing the root cause—such as vitamin D deficiency or hypoparathyroidism—rather than simply overloading the patient with elemental calcium, which carries its own physiological risks.
| Symptom | Clinical Term | Underlying Physiological Mechanism |
|---|---|---|
| Numbness in Hands/Feet | Paresthesia | Increased neuronal membrane excitability due to reduced extracellular calcium ions. |
| Muscle Cramps/Spasms | Tetany | Spontaneous, repetitive motor nerve discharges affecting skeletal muscle groups. |
| Pervasive Exhaustion | Chronic Fatigue | Disrupted cellular energy metabolism and secondary endocrine regulation failure. |
Contraindications & When to Consult a Doctor
Self-prescribing high-dose calcium or vitamin D supplements without medical supervision is strongly discouraged. Excessive calcium intake can lead to hypercalcemia, which causes severe complications including cardiac arrhythmias, renal calculi (kidney stones), and vascular calcification.
Patients experiencing persistent numbness, severe muscle cramps, or debilitating fatigue should schedule an immediate evaluation with a primary care physician or endocrinologist. Diagnostic workups typically include a serum total or ionized calcium test, parathyroid hormone (PTH) assay, and a 25-hydroxyvitamin D panel to establish an accurate diagnosis before initiating any therapeutic intervention.
References
- National Institutes of Health (NIH) Office of Dietary Supplements. Calcium Fact Sheet for Health Professionals.
- Centers for Disease Control and Prevention (CDC). Nutritional Status and Data Tables.
- World Health Organization (WHO). Guideline: Mineral and Vitamin Requirements in Human Nutrition.
Disclaimer: This article is for informational purposes only and does not substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition.
