
A confirmed measles exposure tied to an unvaccinated passenger aboard a California train threatens to spread the highly contagious viral infection across six counties, according to regional public health alerts. State and local health agencies are actively tracking potential transmission vectors among commuters as medical authorities urge immediate immunization verification.
In Plain English: The Clinical Takeaway
- Measles Transmission: The measles virus spreads easily through the air when an infected person breathes, coughs, or sneezes, remaining viable in shared indoor air spaces for up to two hours.
- Incubation and Immunity: Symptoms typically appear 10 to 14 days after exposure. Individuals with documented double-dose MMR (Measles, Mumps, and Rubella) vaccination retain robust cellular and humoral immunity.
- Critical Action: Unvaccinated passengers sharing transit routes with the index case must monitor for prodromal symptoms—including high fever, coryza, cough, and conjunctivitis—and contact healthcare providers before visiting clinics to prevent exposure to vulnerable populations.
Epidemiological Dynamics and Transit Vectors
The latest public health alert highlights the vulnerability of mass transit systems during infectious disease outbreaks. Because the measles virus exhibits an exceptionally high basic reproduction number ($R_0$)—often estimated between 12 and 18—a single infectious individual in a confined rail car can expose dozens of susceptible passengers. According to the Centers for Disease Control and Prevention (CDC), the virus targets the respiratory epithelium before systemic dissemination via the lymphatic system.
Regional health jurisdictions spanning the six affected California counties are coordinating contact tracing efforts. Healthcare systems have activated triage protocols established by the U.S. Food and Drug Administration (FDA) to manage potential clinical presentations. Clinicians emphasize that early identification remains the most effective containment strategy against community-acquired clusters.
Clinical Characteristics and Comparative Prevention Metrics
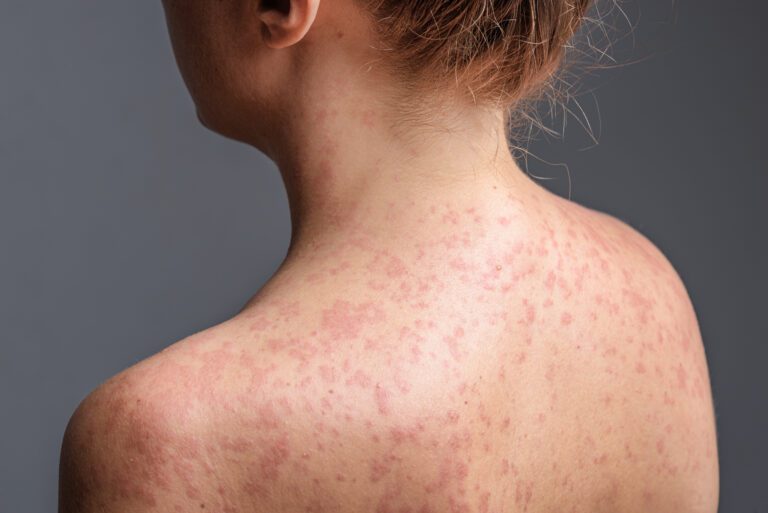
Understanding the clinical progression of measles helps differentiate it from other common viral upper respiratory infections. The disease initiates with a characteristic prodrome characterized by high fever, cough, runny nose, and red watery eyes, followed days later by the classic maculopapular rash.
| Metric / Parameter | Unvaccinated Individual | Fully Vaccinated (2-Dose MMR) |
|---|---|---|
| Infection Risk Upon Exposure | Exceeds 90% among susceptible contacts | Approximately 3% to 5% risk of breakthrough infection |
| Symptom Severity | High risk of complications (otitis media, pneumonia, encephalitis) | Typically asymptomatic or mild, self-limiting course |
| Public Health Protocol | Mandatory 21-day quarantine if unvaccinated and exposed | No quarantine required; routine monitoring advised |
According to data published in The Lancet, maintaining high population-level vaccine uptake remains vital for herd immunity, shielding infants too young to receive the MMR vaccine and immunocompromised patients who possess medical contraindications.
Contraindications & When to Consult a Doctor
Individuals uncertain of their vaccination status should review their immunization records with a primary care provider immediately. The live-attenuated MMR vaccine is contraindicated for pregnant individuals, severely immunocompromised patients, and those with a history of life-threatening anaphylactic reactions to neomycin or a previous dose of the vaccine.
Anyone who develops a fever accompanied by a rash within three weeks of potential exposure must isolate immediately. Patients are strictly advised to call ahead before arriving at an emergency department, urgent care clinic, or physician’s office so medical staff can implement airborne isolation precautions prior to entry, minimizing further transmission within healthcare facilities.
Future Trajectory and Public Health Preparedness
As state health departments continue monitoring the six-county footprint, containment relies heavily on prompt post-exposure prophylaxis. Administering the MMR vaccine within 72 hours of initial exposure or providing immunoglobulin within six days can modify or prevent clinical disease in susceptible contacts, as outlined in guidelines from the World Health Organization (WHO). Public health officials underscore that widespread adherence to vaccination schedules remains the singular clinical defense against resurgence.
References
- Centers for Disease Control and Prevention (CDC). Measles Transmission and Clinical Overview. Available from: CDC Measles Guidance
- World Health Organization (WHO). Measles Fact Sheet and Immunization Strategies. Available from: WHO Measles Overview
- The Lancet. Global Vaccine Immunity and Epidemiological Trends in Measles Outbreaks. Available from: The Lancet Archives
- U.S. Food and Drug Administration (FDA). MMR Vaccine Safety and Regulatory Information. Available from: FDA MMR Portal
