
An 81-year-old man presenting with a one-year history of right-sided cervicalgia and hemicranial headache has become the subject of a medical case study published in Cureus, detailing the first known instance of lesser occipital neuralgia directly attributed to continuous positive airway pressure (CPAP) mask headgear.
Diagnostic Overlap and the Cervical Spondylosis Mask
When the patient first sought medical attention at Physical Medicine and Rehabilitation, his chronic pain was initially attributed to underlying spinal pathology. Imaging had confirmed multilevel cervical degenerative disc-osteophyte disease accompanied by severe foraminal stenosis. Given these structural findings, clinicians initially presumed his symptoms stemmed from cervical spondylosis and myofascial aetiology.
Treatments including pregabalin, physiotherapy, and localized mesotherapy offered limited relief.
A closer re-evaluation of the clinical history shifted the diagnostic trajectory. Reviewers noted a precise temporal link between the onset of the patient’s symptoms and his initiation of nocturnal CPAP therapy for obstructive sleep apnoea. Furthermore, hyperalgesia was sharply confined to the anatomical territory of the lesser occipital nerve, and axial rotation consistently reproduced the pain.
Anatomical Mechanics and Device-Related Entrapment
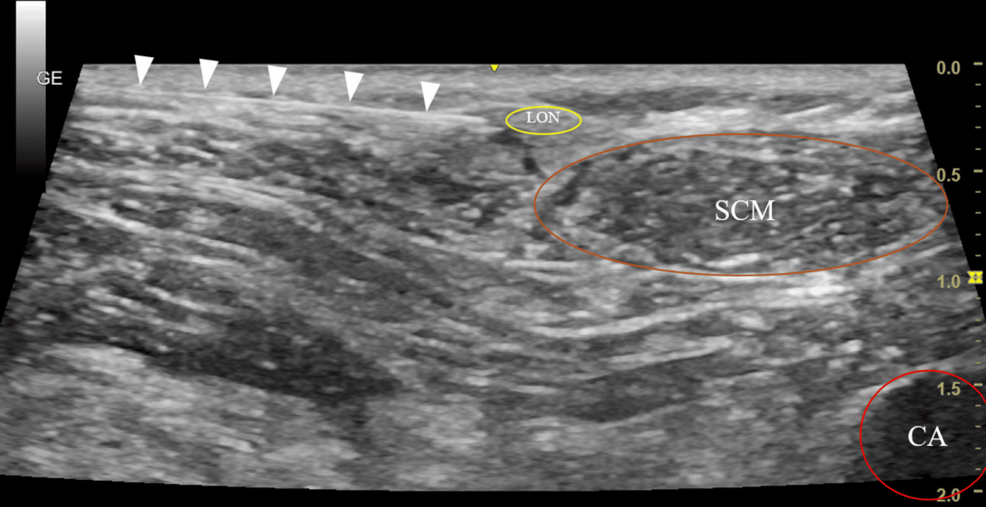
The lesser occipital nerve functions as a cutaneous branch of the cervical plexus, typically originating from C2 and occasionally C3. The nerve hooks around the accessory nerve and ascends along the posterior border of the sternocleidomastoid muscle before piercing the deep fascia near the occiput. Because of this proximity, movements involving the contraction of the sternocleidomastoid muscle can dynamically compress or traction the nerve along its path.
Continuous positive airway pressure treatment relies on a mask secured by multi-point headgear designed to maintain airtight seals through sustained circumferential tension around the occiput and mastoid region. In this patient, that mechanical footprint coincided directly with the pathway of the lesser occipital nerve, resulting in repetitive strap-related compression and traction that was further aggravated by cervical rotation.
Ultrasound-Guided Confirmation and Clinical Implications
To test the mechanical entrapment hypothesis, clinicians performed an ultrasound-guided anaesthetic block of the right lesser occipital nerve under aseptic technique. The intervention produced immediate and complete resolution of pain upon cervical rotation, confirming the diagnosis of device-related lesser occipital neuralgia rather than pure cervical spondylosis.
The Cureus report notes that external headwear such as helmets, goggles, and tight headbands are recognized triggers of pericranial pain, formally classified by the International Classification of Headache Disorders as external-compression or external-traction headaches. N95 respirator straps have also been linked to similar entrapment phenomena.
This case expands that clinical framework to nocturnal respiratory equipment, indicating that clinicians should evaluate CPAP users presenting with cervicogenic-type headaches for device-related nerve irritation, even when confounding degenerative spine disease is present on imaging.
