
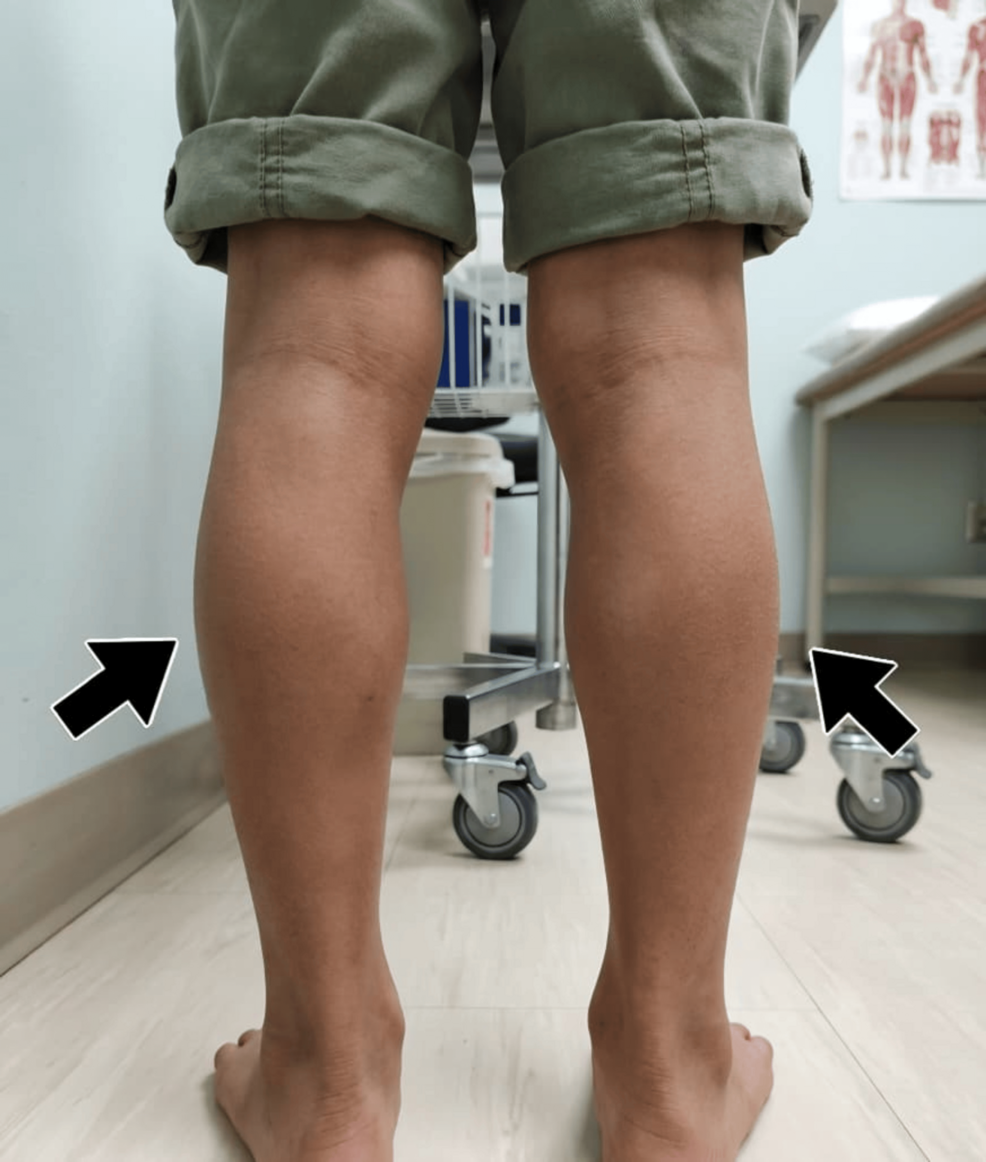
An eleven-year-old boy presenting with severe acute hypoxemic respiratory illness and fever was diagnosed with Duchenne muscular dystrophy after clinicians identified longstanding motor delays, calf pseudohypertrophy, and a serum creatine kinase level of 8,500 U/L, as detailed in a recent case report published in Cureus.
In Plain English: The Clinical Takeaway
- What was found: A routine medical evaluation for a severe lung infection uncovered a chronic, inherited muscle-wasting disease that had gone undiagnosed for over a decade.
- Key diagnostic clues: The patient exhibited significant calf enlargement caused by fat and connective tissue replacing healthy muscle (pseudohypertrophy), alongside the distinctive “Gowers maneuver,” where a person uses their hands to push up off their legs when standing due to weak hip and thigh muscles.
- Genetic confirmation: Molecular testing confirmed a pathogenic hemizygous deletion of exons 45-50 on the DMD gene, bypassing the need for a more invasive muscle biopsy.
Diagnostic Obstacles During Acute Pulmonary Presentation
The patient arrived at the clinic presenting with a seven-day productive cough, yellow sputum, fever with chills, and a peripheral oxygen saturation level dropping between 88% and 90% on room air. Clinical examinations confirmed mild respiratory distress accompanied by bilateral end-inspiratory crackles. Concurrently, blood tests revealed a neutrophilic leukocytosis—an elevated white blood cell count indicating an active infection—alongside an elevated C-protein level of 66 mg/L, signaling acute systemic inflammation.
However, these acute pulmonary findings risked masking underlying chronic abnormalities. Parents noted that the boy had experienced progressive lower-extremity weakness over several months, particularly when rising from a seated position. Furthermore, a detailed neurological assessment demonstrated marked symmetric proximal weakness, hypotonia, and diminished deep tendon reflexes in the lower limbs, contrasting sharply with normal upper-extremity strength graded at 5/5 on the Medical Research Council scale. The concurrence of these chronic neuromuscular indicators with an acute lower respiratory tract infection forced clinicians to evaluate overlapping acute and chronic pathologies simultaneously.
Molecular Pathology and Serum Enzymology
To investigate the etiology of the progressive motor impairment, physicians ordered a comprehensive metabolic and enzymatic panel. The serum creatine kinase (CK) concentration registered at 8,500 U/L, which stands at approximately 34 times the upper reference limit of 250 U/L. Mild elevations in aspartate aminotransferase (50 U/L) and alanine aminotransferase (55 U/L) were also recorded, aligning with skeletal muscle injury rather than primary hepatobiliary disease.
Multiplex ligation-dependent probe amplification (MLPA) followed by confirmatory next-generation sequencing identified a hemizygous deletion of exons 45-50 at locus Xp21.2. This genetic variant disrupts the reading frame of the dystrophin gene, preventing the production of functional dystrophin—a critical protein required to maintain structural stability in muscle cell membranes. Because this molecular deletion is localized within a region targeted by specific genetic therapies, the finding immediately qualified the patient for specialized multidisciplinary evaluations.
| Biomarker / Test | Patient Result | Reference Interval |
|---|---|---|
| Creatine Kinase (CK) | 8,500 U/L | 40–250 U/L |
| White-Cell Count | 28.4 × 10⁹/L | 4.0–11.0 × 10⁹/L |
| C-Reactive Protein | 66 mg/L | <5 mg/L |
| Alanine Aminotransferase (ALT) | 55 U/L | ≤40 U/L |
Multidisciplinary Management and Exon-Skipping Surveillance
Following the stabilization of his respiratory illness with supplemental oxygen and empiric intravenous broad-spectrum antibiotics, the patient received a comprehensive referral network. Care was transitioned to pediatric neurology, pulmonology, cardiology, rehabilitation medicine, and genetic counseling services. Long-term therapeutic strategies include the introduction of corticosteroid therapy to preserve muscle function, regular physical therapy, and targeted cardiac and respiratory surveillance.
Because the identified deletion affects exons 45 through 50, clinicians noted potential eligibility for mutation-specific therapies such as exon-skipping drugs, specifically treatments designed to skip exon 51 or adjacent segments to restore reading frames. Final administration depends heavily on regulatory criteria, individual clinical status, and geographic treatment availability.
Contraindications & When to Consult a Doctor
Any persistent presentation of delayed motor milestones, unexplained frequent falls, difficulty climbing stairs, or visible calf enlargement warrants immediate CK screening. Professional medical evaluation should be sought immediately if a child demonstrates progressive proximal muscle weakness or utilizes a Gowers maneuver when rising from the floor.
References
- Cureus. “Delayed Recognition of Duchenne Muscular Dystrophy During an Acute Respiratory Illness in an 11-Year-Old Boy: A Case Report.”
- Medical Research Council. “Manual of Muscle Testing and Grade Classifications.”
Worth a look
- How the Medical Treatments of 1799 Killed George Washington
- ACA Marketplace Enrollment Drops in 2026: By State and Congressional District
- Delayed Diagnosis of Duchenne Muscular Dystrophy in an 11-Year-Old Boy Presenting with Acute Respiratory Illness: A Case Report (newsdirectory3.com)
- 11-Year-Old Boy Diagnosed With Duchenne Muscular Dystrophy (time.news)
