
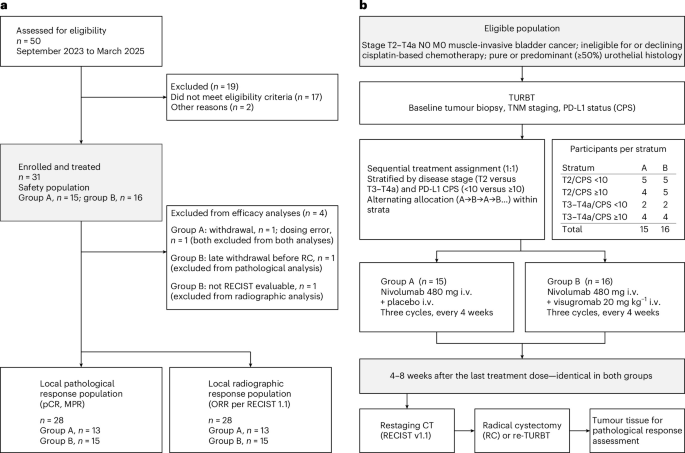
The exploratory phase 2a GDFATHER-NEO trial evaluates neoadjuvant nivolumab with or without visugromab in patients with muscle-invasive bladder cancer who are ineligible for or decline cisplatin chemotherapy. Sponsored by CatalYm GmbH, the trial utilizes a participant-blinded, parallel-group design to measure pathologic complete response and radiographic response rates.
Immunotherapy Drugs Shrink Bladder Cancer Tumors
- What is being tested: A combination of two immunotherapy drugs (nivolumab and visugromab) given before bladder cancer surgery to shrink tumors.
- Who qualifies: Adults with newly diagnosed muscle-invasive bladder cancer who cannot take or choose not to receive standard cisplatin chemotherapy.
- How it works: Nivolumab unleashes the immune system against cancer cells, while visugromab neutralizes a specific protein (GDF-15) that normally suppresses immune responses in the tumor microenvironment.
Trial Investigators Stratify Participants by Tumor Stage
GDFATHER-NEO (NCT06059547; EudraCT 2022-002816-22; EU CT 2024-513957-55-00) investigates neoadjuvant PD-1 blockade combined with GDF-15 neutralization. Before allocation, trial investigators stratified participants by clinical tumor stage—specifically T2 versus T3 to T4a—and by programmed death-ligand 1 (PD-L1) expression on tumor and immune cells. PD-L1 expression was categorized using a combined positive score of either 10 or greater, or less than 10. This sorting established four distinct clinical strata: T2 with a combined positive score under 10, T2 with a score of 10 or higher, T3–T4a with a score under 10, and T3–T4a with a score of 10 or higher.
Within each stratum, patients underwent a 1:1 allocation to receive either nivolumab plus visugromab (group B) or nivolumab plus placebo (group A). Because individual strata contained small patient numbers, researchers chose sequential allocation with participant blinding rather than standard randomization. This method prevented baseline imbalances between treatment arms for this evaluation of combined GDF-15 and PD-1 blockade in early-stage disease treated with curative intent. Investigators and sponsor staff maintained open knowledge of treatment assignments, while patients remained blinded. Local pathologists alongside independent central reviewers evaluated surgical specimens and imaging without knowledge of treatment allocations.
Evaluating Efficacy Endpoints and Surgical Protocols
The trial’s primary objectives centered on measuring antitumor activity through two core endpoints: the pathologic complete response rate determined by blinded local pathologists, and the radiographic response rate assessed via Response Evaluation Criteria in Solid Tumors version 1.1 by investigators. Secondary endpoints encompassed safety and tolerability, pharmacokinetics, pharmacodynamics, antidrug antibody development, event-free survival, and overall survival. The clinical cutoff date for the reported analyses fell on 15 July 2026, supplemented by central review and translational datasets managed under the oversight of Munich-based sponsor CatalYm GmbH.
| Trial Parameter | Specification |
|---|---|
| Trial Design | Exploratory, stratified, participant-blinded, parallel-group phase 2a |
| Target Population | cT2–T4a N0 M0 Muscle-Invasive Bladder Cancer (Cisplatin-ineligible or declining) |
| Intervention Arms | Group B: Nivolumab + Visugromab | Group A: Nivolumab + Placebo |
| Regulatory & Ethics Approvals | Comitato Etico Territoriale Lombardia 1 & Italian Medicines Agency (AIFA) |
Eligible participants aged 18 and older with newly diagnosed clinical stage T2 to T4a, node-negative, metastasis-free muscle-invasive bladder cancer underwent a core treatment phase lasting 19 weeks. This phase incorporated three 4-week immunotherapy cycles followed by a 4-to-8-week window before scheduled radical cystectomy or maximal transurethral resection of bladder tumor. Visugromab (CTL-002) was administered intravenously at 20 milligrams per kilogram every four weeks, while nivolumab was administered at 480 milligrams on the same four-weekly schedule.
Contraindications & When to Consult a Doctor
This investigational neoadjuvant protocol carries strict exclusion criteria. Patients who received prior systemic anticancer therapy, prior radiotherapy to the bladder tumor, or partial cystectomy were excluded from participation. Additional contraindications include active autoimmune disease, clinically significant cardiovascular disease, chronic high-dose systemic corticosteroid treatment, and documented hypersensitivity to visugromab or nivolumab. Patients with type 2 diabetes mellitus were required to discontinue metformin—which alters circulating GDF-15 concentrations—and switch to alternative antidiabetic agents before treatment initiation.
Regulatory Oversight and Translational Tracking
The trial protocol secured approval from the competent ethics committee of the coordinating center, Comitato Etico Territoriale Lombardia 1, and the Italian regulatory authority, the Agenzia Italiana del Farmaco. Operations adhered strictly to the Declaration of Helsinki and International Council for Harmonisation Good Clinical Practice guidelines. Four formal protocol amendments refined the trial parameters prior to and during patient enrollment. These adjustments included removing mandatory post-infusion hospitalization during cycle one, extending the screening period to 28 days, incorporating maximal transurethral resection of bladder tumor as a surgical alternative to radical cystectomy, and formally establishing independent central pathology and radiographic reviews as secondary endpoints.
Exploratory biomarker assessments utilized serial serum sampling to track total visugromab concentrations and screen for antidrug antibodies via validated electrochemiluminescence assays. Formalin-fixed, paraffin-embedded tumor tissue obtained at baseline transurethral resection and post-treatment surgery underwent multiplex immunofluorescence using a 6+1-plex OPAL assay.
References
- ClinicalTrials.gov. NCT06059547: Neoadjuvant Nivolumab With or Without Visugromab in Muscle-Invasive Bladder Cancer (GDFATHER-NEO). Available at: ClinicalTrials.gov NCT06059547.
- Geneva: WHO.
- European Association of Urology guidelines recommend chemoradiotherapy as the principal organ-sparing option. Arnhem: EAU.
Worth a look
- Misiones avoids 112 monthly patient transfers with new technology
- Becky Strasburger’s Instagram Diet Culture Skit Sparks Nostalgia
- How Pancreatic Cancer Rewrites Its DNA to Resist Treatment and Spread (world-today-news.com)
- New Drug Combination Extends Survival by Over 8 Months in Aggressive Small-Cell Lung Cancer (newsdirectory3.com)
