
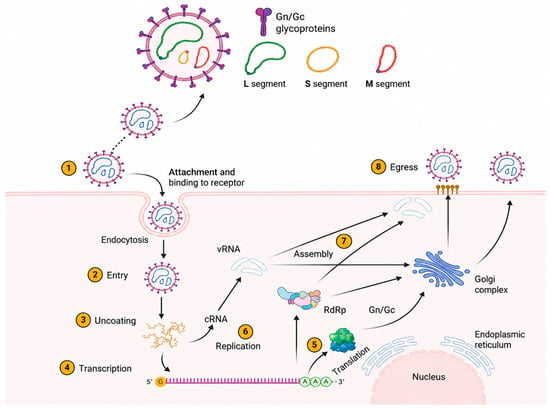
Andes virus, a hantavirus strain responsible for hantavirus pulmonary syndrome in South America, initiates human infection through surface glycoprotein engagement with host receptors like protocadherin-1 and beta-3 integrin, triggering endothelial barrier permeability without causing direct cell lysis, as detailed in peer-reviewed findings.
In Plain English: The Clinical Takeaway
- Vascular Leakage: The virus attacks lung blood vessel linings, forcing gaps between cells that let fluid leak into tissues without destroying the cells outright.
- Delayed Defense: Andes virus proteins actively stall the body’s early alarm system, blocking interferon production so the virus can replicate before the immune system reacts.
- Severe Markers: High levels of specific inflammatory proteins, particularly interleukin-6, closely track with severe disease progression and patient survival outcomes.
Cellular Entry and Endothelial Barrier Disruption
Attachment and receptor engagement mark the beginning of the hantavirus life cycle, steering the virus toward endothelial cells that line blood vessels. Laboratory tests using human umbilical vein endothelial cells and baby hamster kidney cells showed that vitronectin, antibodies against alpha-v beta-3 integrins, and human beta-3-integrin PSI-domain polypeptides suppressed Andes virus infection. Adding the L33P mutation to the human beta-3 PSI domain removed this inhibitory effect, confirming a residue-specific interaction during host cell contact. Subsequent research identified protocadherin-1 as a critical entry factor for pulmonary endothelial cells, as Syrian golden hamsters lacking protocadherin-1 demonstrated strong resistance to a lethal virus assault.
Primary human lung microvascular endothelial cell screens revealed that viral entry depends primarily on clathrin, dynamin, and membrane cholesterol, alongside a clathrin-independent micropinocytosis pathway. Unlike infections that destroy host tissue through cell lysis, Andes virus disrupts signaling pathways that maintain vascular integrity. Replicating virus enhanced monolayer permeability, reduced VE-cadherin levels, and raised vascular endothelial growth factor production.
Another major driver of barrier dysfunction involves RhoA signaling. Andes virus infection or expression of its nucleocapsid protein alone triggered RhoA activation in primary pulmonary microvascular endothelial cells. Knockdown techniques and RhoA/ROCK inhibitors such as fasudil and Y27632 reduced virus-associated permeability by 80 to 90 percent. The viral nucleocapsid protein achieved this by binding and sequestering Rho GDP-dissociation inhibitor, which normally keeps RhoA inactive. Hypoxia and protein kinase C alpha signaling further released RhoA from phosphorylated RhoGDI, driving VE-cadherin internalization and increasing vascular permeability without cell death.
| Cellular Pathway | Primary Viral Mediator | Functional Impact on Endothelium |
|---|---|---|
| VEGF-VEGFR2 Signaling | Replicating Andes Virus | Reduces VE-cadherin and breaks down adherens junctions |
| RhoA/ROCK Pathway | Nucleocapsid Protein | Sequesters RhoGDI, driving 80-90% of permeability changes |
| mTOR-S6K Signaling | Hypoxic Exposure | Multiplies endothelial permeability three to six times |
Evasion of Early Innate Immunity and Interferon Suppression
Andes virus delays the early innate antiviral response rather than completely suppressing it. Compared to the nonpathogenic Prospect Hill virus, Andes virus significantly reduced the early generation of interferon beta, Interferon Regulatory Factor 3 dimerization, and nuclear translocation in primary human pulmonary microvascular endothelial cells.
Mutational studies pinpointed serine 386 on the nucleocapsid protein as essential for this inhibitory activity. Substituting serine with alanine or histidine eliminated interferon induction suppression, while the phosphomimetic S386D substitution restored it. Additionally, the viral nonstructural protein NSs interacted with mitochondrial antiviral-signaling protein to decrease downstream signaling without disrupting the interaction between mitochondrial antiviral-signaling protein and TBK1.
Systemic Inflammatory Dysregulation and Biomarkers
Clinical observations indicate that inflammatory responses during Andes virus infection vary widely, with specific mediators correlating strongly with illness severity. Interleukin-6 concentrations were nearly 40 times higher in severe instances than in moderate ones, separating severe hantavirus cardiopulmonary syndrome from uniform cytokine amplification.
A broader retrospective cohort study of Argentine patients confirmed that interferon gamma, soluble TRAIL, intestinal fatty acid-binding protein, interleukin-6, and interleukin-8 were higher in fatal cases than in survivors. Multivariable analysis identified intestinal fatty acid-binding protein as independently linked with a fatal outcome, and interleukin-6 with disease severity. These indicators point to systemic mechanisms involving intestinal epithelial damage and microbial translocation during severe illness, extending the pathological scope beyond pulmonary inflammation.
