
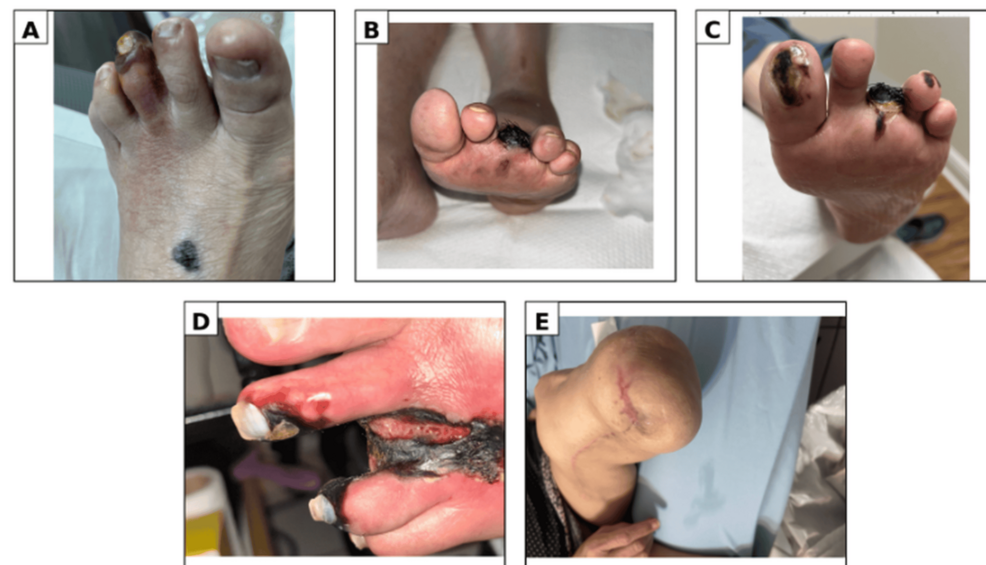
A 72-year-old woman developed atheroembolic blue toe syndrome, progressing to a below-knee amputation despite endovascular aortic repair, revascularization attempts, and multiple limb salvage procedures. Cureus reported that severe distal runoff disease, recurrent infections, and poor wound oxygenation drove the failure of initial source control measures.
Anatomy of an Occlusive Crisis
Blue toe syndrome involves the sudden appearance of painful, dusky-blue, or violaceous toes without major physical trauma or cold injury. In this patient, distal infrarenal aortic soft plaque and distal tibial and pedal arterial disease supplied the embolic material. While proximal pulses often remain palpable—making initial large-vessel imaging appear deceptively normal—smaller digital arteries suffer severe occlusive ischemia.
Cascading Complications and Failed Salvage
Following endovascular aortic source control, the patient experienced progressive dry gangrene in her left third toe. Over subsequent months, her clinical course deteriorated due to secondary infections caused by Pseudomonas aeruginosa and methicillin-resistant Staphylococcus aureus (MRSA), alongside chronic osteomyelitis. Multiple interventions—including angioplasty, common plantar embolectomy, plantar bypass, transmetatarsal amputation, Achilles tendon lengthening, and external fixation—failed to restore viable tissue perfusion.

Contrasting Systemic Versus Localized Presentation
Broader clinical documentation highlights the systemic nature of cholesterol crystal embolization. A separate case reported on sciencedirect.com described a 61-year-old male who developed blue toe syndrome, reticular livedo, and gastrointestinal bleeding one week after aortic interventional therapy for intermittent claudication. That patient exhibited eosinophilia, multiorgan dysfunction, and a cherry-red spot at the macula confirmed via fundoscopic examination.
While the male patient achieved partial renal function recovery from stage 4 to stage 3b chronic kidney disease over three months with conservative management, the 72-year-old female profile detailed by Cureus underscores a localized, refractory extremity outcome. Both cases illustrate that dislodged atherosclerotic plaque fragments initiate microvascular occlusion, but anatomical runoff status and comorbid conditions dictate whether organs recover or tissues undergo necrosis.
Clinical Parameters and Differential Outcomes
Patients with known peripheral arterial disease, diabetes mellitus, or hypercoagulable states like antiphospholipid syndrome face heightened vulnerability to atheroembolic events following endovascular manipulations or spontaneous plaque rupture. Anticoagulation therapy requires careful clinical balancing, as aggressive intervention does not automatically reverse established microvascular bed destruction. Immediate medical evaluation is warranted upon the sudden, unexplained onset of painful digital discoloration, rest pain, or nonhealing wounds, as prompt vascular surgery consultation is critical to assess both proximal sources and distal runoff viability.
