
A twenty-two-year-old man in the United Kingdom presented with an acute ischemic stroke that unmasked a rare case of cerebral neuroschistosomiasis driven by Schistosoma haematobium infection acquired years earlier in Senegal, Cureus reported.
Parasite Infection Triggers Stroke in Young Man
- What happened: A young, healthy man suffered a sudden stroke caused by parasite-induced inflammation restricting his brain’s blood vessels.
- The root cause: An untreated urinary parasite infection from swimming in freshwater lakes years prior triggered an aggressive immune response in his brain.
- The treatment path: Physicians administered targeted steroids to reduce brain swelling before prescribing antiparasitic drugs to prevent a potentially fatal immune shock.
Unusual Neurological Presentation of a Neglected Tropical Disease
Schistosomiasis remains a widespread neglected tropical disease. The World Health Organisation estimated that 253.7 million people required preventive treatment globally. The parasite Schistosoma haematobium classically causes urinary schistosomiasis, marked by terminal hematuria, or blood in the urine, and bladder wall calcification. Neurological complications are rare. While cerebral disease is typically attributed to S. japonicum, spinal cord involvement is more frequently linked to S. mansoni and S. haematobium.
The patient, a resident of the United Kingdom originally from Senegal, arrived via ambulance with sudden left-sided weakness, numbness, speech difficulties, headache, and poor balance. He reported no cardiovascular risk factors but noted intermittent terminal hematuria over the preceding months. He also recalled frequently swimming in freshwater lakes while living in Senegal. Neurological examinations revealed left hemiparesis, sensory disturbances, dysarthria, and cerebellar signs.
Imaging Reveals Acute Infarct and Vascular Narrowing
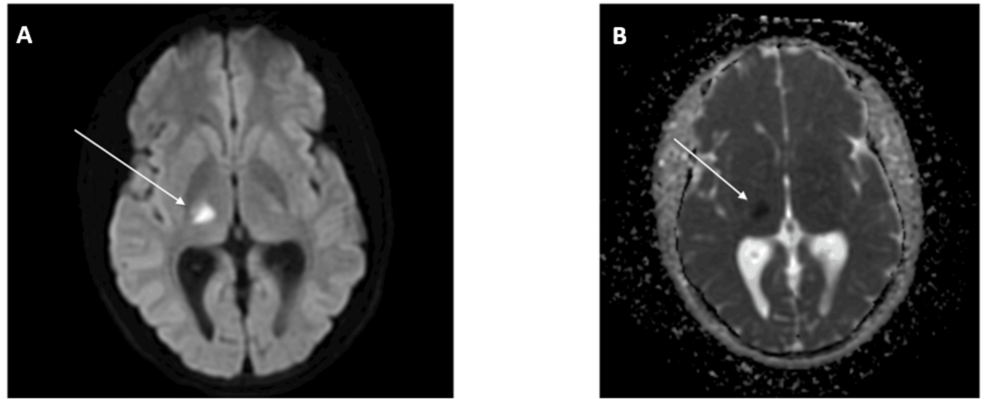
Non-contrast CT imaging revealed a subtle hypodensity in the right thalamus and posterior limb of the internal capsule. Subsequent magnetic resonance imaging confirmed an acute infarct in the right posterior thalamus with true diffusion restriction. CT angiography and MR angiography displayed a multifocal intracranial vasculopathy, showing luminal narrowing in the right terminal internal carotid artery, distal right middle cerebral artery, right P2 segment, and proximal right superior cerebellar artery. Atheroma and vasculitis were initially retained as differential diagnoses.
Laboratory results showed a marked peripheral eosinophilia of 1.4 × 10⁹/L, well above the normal reference range of 0 to 0.5 × 10⁹/L. Comprehensive autoimmune and vasculitis screens—including PR3 antibodies, MPO antibodies, ANA, and complement levels—returned negative results. Further parasitological testing confirmed Schistosoma haematobium ova in the patient’s urine and positive serum schistosomal antibodies via enzyme-linked immunosorbent assay. Urological imaging revealed bladder dome calcification and a pelvic ectopic left kidney.
| Diagnostic Test | Patient Value | Reference Range |
|---|---|---|
| Eosinophil Count | 1.4 x 10⁹/L | 0 – 0.5 x 10⁹/L |
| C-Reactive Protein | <1 mg/L | 0 – 5 mg/L |
| Urine Microscopy | Ova of S. haematobium seen | N/A |
| Schistosomal Antibody (ELISA) | Positive | N/A |
Multidisciplinary Management and Therapeutic Sequencing
Following multidisciplinary review involving stroke, infectious diseases, urology, rheumatology, and neuroradiology teams, clinicians prioritized corticosteroids over immediate antiparasitic administration. This careful sequencing prevented the risk that administering praziquantel first might precipitate severe, life-threatening inflammatory deterioration in acute neuroschistosomiasis. The patient received a six-week tapering course of oral prednisolone, starting at 60 mg daily, alongside a single empirical dose of ivermectin to cover potential strongyloidiasis prior to immunosuppression.
Praziquantel was subsequently administered at 20 mg/kg twice daily for three days during the steroid taper. Follow-up imaging demonstrated a reduction in the nodular enhancing thalamic lesion and surrounding edema. A six-week post-treatment MRI confirmed infarct maturation and stable intracranial vasculopathy without new acute ischemic events. The patient’s eosinophilia normalized, repeat urine microscopy showed no schistosomal ova, and he achieved a good functional recovery with no clinical recurrence over twelve months of follow-up.
Avoid Antiparasitic Drugs During Acute Inflammation
Antiparasitic medications like praziquantel are strictly contraindicated as first-line monotherapy in acute cerebral neuroschistosomiasis, as eliminating the parasites rapidly can trigger a catastrophic immune-mediated inflammatory surge. Anyone experiencing sudden focal neurological deficits, persistent hematuria after freshwater exposure abroad, or unexplained peripheral eosinophilia must seek immediate emergency medical evaluation.
References
- World Health Organization. Schistosomiasis Fact Sheet. Global prevalence and preventive chemotherapy estimates.
- Cureus. Ischaemic Stroke Due to Schistosoma haematobium (Cerebral Neuroschistosomiasis): A Case Report in a Young Man.
- National Institutes of Health.
