
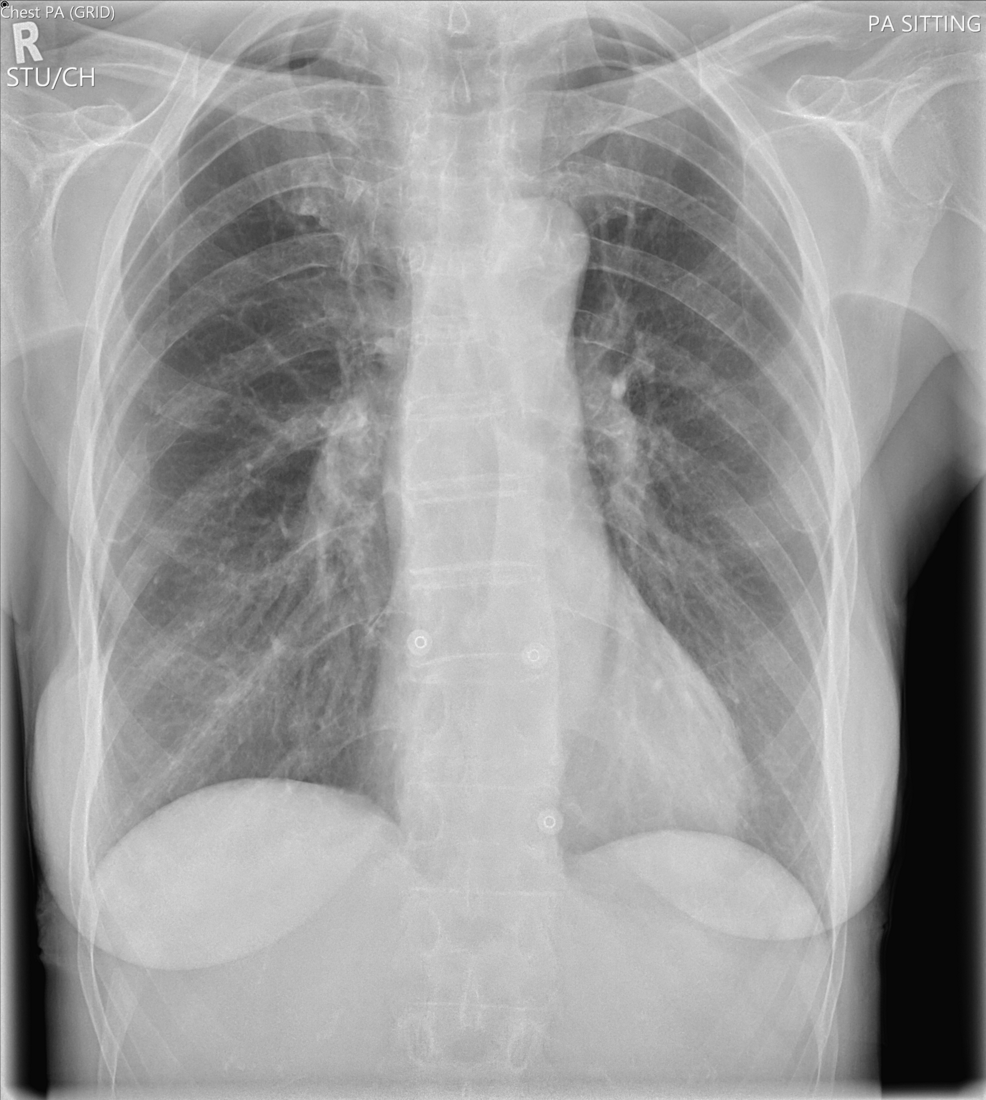
Published in Cureus, a recent medical case study details how respiratory-onset motor neuron disease in a 78-year-old woman was initially masked by suspected obstructive airway disease and lung nodules, resulting in a prolonged diagnostic journey characterized by severe progressive weight loss.
In Plain English: The Clinical Takeaway
- Respiratory-Onset Motor Neuron Disease: A rare form of motor neuron disease (MND) where breathing muscle weakness appears before any limb or swallowing problems.
- Chronic Daytime Hypercapnia: A buildup of carbon dioxide in the blood caused by weakened respiratory muscles failing to expel air effectively.
- Diagnostic Masking: When symptoms of a rare neurological disease mimic more common lung conditions, leading to significant delays in proper care.
The Diagnostic Puzzle of Atypical Motor Neuron Disease Presentations
Motor neuron disease is a progressive neurodegenerative disorder characterized by the degeneration of upper and lower motor neurons. This cellular breakdown results in progressive muscle weakness and, eventually, respiratory failure. Amyotrophic lateral sclerosis remains the most common form, while other phenotypes like progressive muscular atrophy are also recognized. Median survival from symptom onset sits at approximately three years, with respiratory failure acting as the most frequent cause of death.
While symptom onset typically involves limb or bulbar muscles, a small proportion of patients present differently. Respiratory-onset MND accounts for approximately 1%-4% of presentations. These patients experience progressive dyspnoea, orthopnoea, sleep-related hypoventilation, and fatigue before showing any clinically apparent limb or bulbar weakness. Because respiratory muscle weakness reduces tidal volume and impairs the body’s response to rising carbon dioxide levels, patients first develop nocturnal hypoventilation. As compensatory mechanisms fail, chronic daytime hypercapnia with a compensatory rise in bicarbonate develops.
Diagnostic delays in motor neuron disease average 10-16 months. Atypical presentations like respiratory-onset disease exacerbate this delay because initial symptoms mimic more common cardiopulmonary disorders. Unintentional weight loss, driven by muscle wasting, reduced nutritional intake, and increased metabolic demand, often leads clinicians to initially investigate malignancy or systemic disease.
Clinical Timeline and Pulmonary Function Findings
The case involves a 78-year-old woman referred to the acute medical team in May 2025. She presented with a two-year history of progressive functional decline, exertional breathlessness, fatigue, generalized weakness, and severe unintentional weight loss from 75 kg to 45 kg, yielding a body mass index of 18.7 kg/m². She attributed her reduced oral intake to a changed sense of taste following a suspected COVID-19 infection in 2019.
Four months prior to admission, she experienced rapid functional deterioration, loss of appetite, and further weight loss. Extensive investigations had begun years prior. In 2023, as a lifelong non-smoker with exertional dyspnoea and a productive cough, she underwent chest radiography that showed large lung volumes. Spirometry demonstrated an obstructive pattern, and a computed tomography scan of the chest, abdomen, and pelvis revealed bilateral pulmonary nodules up to 5 mm alongside mild bronchiolitis with mucous plugging. Interval surveillance under British Thoracic Society guidance eventually led to discharge after the nodules remained stable.
Subsequent formal pulmonary function testing in February 2024 confirmed significant obstruction, with a forced expiratory volume in one second of 1.06 L and a forced vital capacity of 1.70 L. Static lung volumes demonstrated a preserved total lung capacity of 4.86 L alongside an elevated residual volume of 3.15 L, indicating gas trapping and hyperinflation rather than a restrictive process. Consequently, clinicians attributed her reduced vital capacity to air trapping from obstructive disease and commenced a long-acting beta-agonist for suspected small airways disease.
| Clinical Parameter | Initial Findings (2023–2024) | Evolving Presentation |
|---|---|---|
| Primary Symptoms | Exertional dyspnoea, productive cough, weight loss | Progressive neck pain, difficulty supporting the weight of her head, functional decline |
| Pulmonary Testing | Obstructive pattern, gas trapping, elevated residual volume | Normal fractional exhaled nitric oxide, preserved total lung capacity |
| Initial Attributions | Small airways disease, pulmonary nodules, COVID-19 sequelae | Neuromuscular respiratory failure |
Contraindications & When to Consult a Doctor
Patients presenting with unexplained progressive weight loss, exertional breathlessness, and hypercapnia that fails to resolve with standard bronchodilator therapy require comprehensive neurological evaluation. Clinicians must exercise caution before attributing carbon dioxide retention solely to obstructive airway disease, particularly when pulmonary function testing reveals preserved total lung capacity alongside abnormal respiratory mechanics.
Immediate medical consultation is warranted if individuals develop symptoms of respiratory muscle weakness, such as orthopnoea, sleep-related hypoventilation, or difficulty supporting the weight of the head. Misattributing these neuromuscular signs to pulmonary or gastrointestinal etiologies can postpone essential multidisciplinary support and palliative respiratory interventions.
The Unresolved Diagnostic Challenges in Atypical MND
The case underscores the critical vulnerability in current diagnostic pathways when neurodegenerative conditions disguise themselves as routine pulmonary pathologies. By documenting how chronic hypercapnia and obstructive spirometry patterns can misdirect medical teams away from rare neuromuscular presentations, the report highlights the necessity of maintaining a broad differential diagnosis. The fundamental question remains open regarding how primary care and acute medical pathways can better identify early neuromuscular respiratory failure before profound physical deterioration and severe weight loss occur.
References
- British Thoracic Society: Guidelines for the Investigation and Management of Pulmonary Nodules.
