
Infections can spike heart attack risk sixfold in the first week, with bloodstream infections nearing a tenfold jump, while chronic viruses such as HIV and tuberculosis raise long-term odds by roughly 50 percent, a new narrative review in Cureus shows.
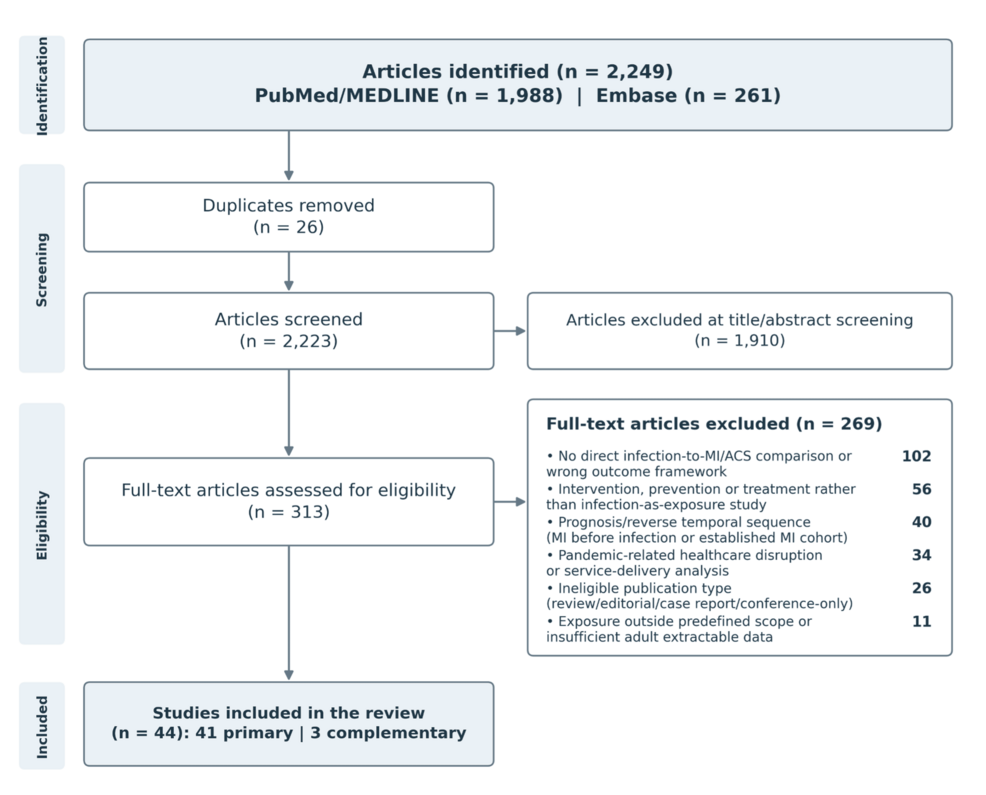
The review, published this week after a literature search finalized on October 6, 2026, analyzed 44 studies encompassing influenza, SARS-CoV-2, bacteremia, urinary tract infections, HIV, tuberculosis, and hepatitis C. It distinguishes sharply between Type 1 myocardial infarction — caused by plaque rupture and clot formation — and Type 2 infarction, driven by oxygen supply-demand mismatch without acute atherothrombosis. Earlier meta-analyses often blended these mechanisms; this review does not.
Severe Infection Raises Heart Attack Risk Within Days
- A severe infection this week can trigger a heart attack within days, especially if you already have coronary artery disease.
- Chronic infections like HIV or treated tuberculosis leave a lasting imprint on cardiovascular risk that persists for years.
- Not all troponin elevations during infection signal a heart attack; clinicians must separate demand ischemia from true plaque rupture.
Acute respiratory infections and influenza showed the steepest early hazard. A self-controlled case series by Kwong and colleagues reported an incidence ratio of 6.05 (95% CI 3.86–9.50) in days one through seven after laboratory-confirmed influenza. De Boer’s cohort mirrored that magnitude with an adjusted relative incidence of 6.16 (4.11–9.24). Bloodstream infection carried an even higher adjusted incidence rate ratio of 9.67 (6.54–14.3) in the first week, while urinary tract infection conferred a 2.49-fold rise (1.65–3.77).
COVID-19 presented a dual timeline. In the acute phase, Katsoularis et al. found an incidence rate ratio of 2.89 (1.51–5.55) during the first week excluding day zero, whereas Suzuki et al. reported 6.65 (4.66–9.48). Beyond 30 days, Xie’s Veterans Affairs cohort documented an adjusted hazard ratio of 1.63 (1.51–1.75) for myocardial infarction over 12 months, translating to an excess burden of 2.91 cases per 1,000 persons. The review flags survivor selection and coded-outcome limitations in that analysis.
| Infection Exposure | Risk Window | Effect Estimate (95% CI) | Study Design |
|---|---|---|---|
| Laboratory-confirmed influenza | Days 1–7 | IR 6.05 (3.86–9.50) | Self-controlled case series |
| Bloodstream infection | Days 1–7 | Adjusted IRR 9.67 (6.54–14.3) | Cohort |
| Urinary tract infection | Days 1–7 | IRR 2.49 (1.65–3.77) | Cohort |
| COVID-19 (post-acute) | Beyond day 30; 12-month | Adjusted HR 1.63 (1.51–1.75) | Cohort (VA) |
| HIV | Multi-year follow-up | Adjusted HR 1.48 (1.27–1.72) | Cohort |
| Latent tuberculosis infection | Survivor follow-up | Adjusted OR 1.90 (1.05–3.45) | Case-control |
| Tuberculosis survivors | From 1 year post-TB; median 3.9 yr | 341/60,602 vs 223/60,602 controls | Matched cohort |
| Hepatitis C | Median 3.2 years | Adjusted HR 1.10 (0.67–1.83) | Matched cohort |
Chronic infections told a different story. The Veterans Aging Cohort Study led by Freiberg showed HIV carried an adjusted hazard ratio of 1.48 (1.27–1.72) for myocardial infarction over multi-year follow-up, even after adjusting for antiretroviral therapy and traditional risk factors.
Latent tuberculosis infection was associated with an adjusted odds ratio of 1.90 (1.05–3.45) in Huaman’s analysis, while Lee’s Korean national cohort found a hazard ratio of 1.48 (1.23–1.78) for myocardial infarction among tuberculosis survivors followed for a median of 3.9 years. Hepatitis C did not reach statistical significance in Forde’s matched cohort: adjusted HR 1.10 (0.67–1.83), with event rates of 1.02 versus 0.92 per 1,000 person-years.
The review emphasizes that comparator choice materially shifts effect sizes. Dalager-Pedersen reported acute myocardial infarction in 1.7% of bacteremia patients versus 0.1% in population controls and 0.8% in hospitalized controls — a reminder that severity and healthcare exposure confound the association. Self-controlled designs mitigate fixed confounding but remain vulnerable to time-varying factors such as seasonal vaccination or medication changes.
The Cureus review itself reports no external funding.
The 2023 European Society of Cardiology guidelines on cardiovascular disease prevention cite chronic inflammatory conditions — including HIV and treated tuberculosis — as risk enhancers that may justify earlier statin initiation. The American Heart Association’s 2024 scientific statement on infection and cardiovascular disease echoes this, recommending clinicians document severe infections as part of the clinical risk assessment.
Troponin Elevation in Sepsis Does Not Require Catheterization
Troponin elevation alone during sepsis or severe pneumonia does not mandate catheterization; clinical context, ECG evolution, and serial troponin trends determine Type 1 versus Type 2 classification.
The review’s authors acknowledge overlapping cohorts across several national registries, lack of independent duplicate screening, and absence of a registered protocol — limitations that preclude quantitative pooling. The consistency of the acute signal across influenza, bloodstream infection, and COVID-19, and the chronic signal across HIV and tuberculosis, suggests infection belongs in the same clinical conversation as hypertension, dyslipidemia, and smoking when assessing myocardial infarction risk.
References
- Kwong JC et al. PubMed
- Xie Y et al. PubMed
- Freiberg MS et al. PubMed
