
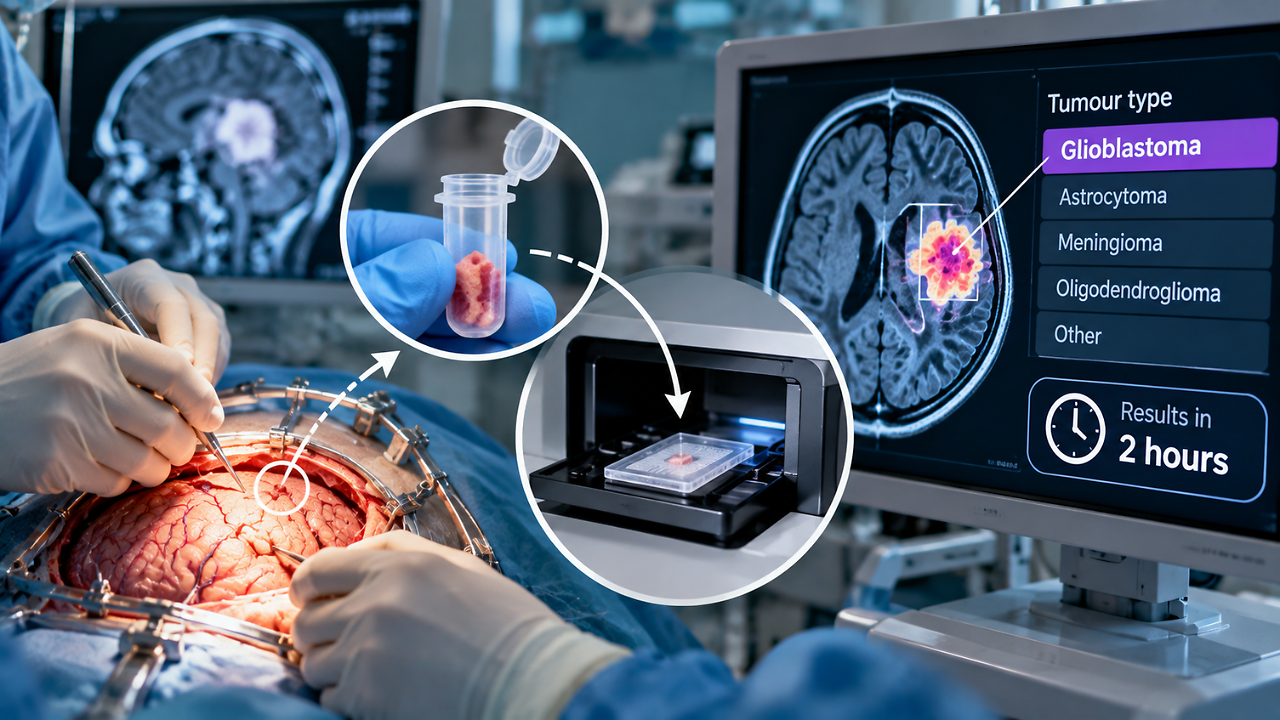
The NHS is piloting a rapid genomic test that identifies brain tumour types within two hours during surgery. Developed by the University of Nottingham and Nottingham University Hospitals NHS Trust, this technology replaces weeks of waiting with real-time molecular classification, allowing surgeons to make immediate, life-saving decisions on the operating table.
For patients facing a primary brain tumour diagnosis, the interval between surgical resection and pathological confirmation is often a period of profound psychological distress. In the UK, where over 12,000 people are diagnosed annually, this wait can stretch from 26 days to eight weeks. Because brain tumours encompass over 100 distinct types—varying from indolent, slow-growing masses to highly aggressive malignancies—the specific molecular profile dictates the entire trajectory of care. A delay in this information isn’t just an emotional burden; it is a clinical gap that can postpone the initiation of targeted chemotherapy or entry into critical clinical trials.
- In Plain English: The Clinical Takeaway
- Instant Answers: Diagnosis time drops from weeks to roughly two hours, occurring while the patient is still in surgery.
- Precision Surgery: Surgeons can use real-time data to decide exactly how much tumour to remove without damaging healthy brain tissue.
- Faster Treatment: Patients bypass the “waiting game,” starting the correct medication or joining specialized trials almost immediately.
Nanopore Sequencing: How DNA Fingerprinting Replaces the Microscope
Traditional neuropathology relies on histopathology—the process of slicing tissue and examining cell morphology under a microscope. While essential, this method can be subjective and slow. The new rapid test shifts the focus from how a cell looks to what its genetic code says.
The mechanism of action involves a “shoebox-sized” sequencing machine developed by Oxford Nanopore. During surgery, a small tissue sample is extracted and sent to the lab. The DNA molecules are passed through a nanopore—a microscopic hole. As the DNA strands move through this pore, the system reads the genomic pattern, creating a unique “genomic fingerprint” of the tumour. This molecular classification provides a level of clarity that traditional microscopy cannot match.
Dr. Simon Paine, a consultant neuropathologist at Nottingham University Hospitals NHS Trust, describes the traditional microscopic approach as “crystal ball gazing,” noting that while it is effective, it lacks the comprehensive molecular clarity provided by the nanopore technology.
Comparing Diagnostic Timelines and Clinical Impact
The shift from traditional pathology to rapid genomic sequencing represents a fundamental change in the surgical workflow. By integrating diagnosis into the operative window, the NHS aims to eliminate the “race against time” described by Prof Frankie Swords, NHS medical director.
| Feature | Traditional Pathology | Rapid Genomic Testing |
|---|---|---|
| Primary Method | Microscopic tissue examination | DNA nanopore sequencing |
| Average Wait Time | 26 days to 8 weeks | Approximately 2 hours |
| Surgical Utility | Post-operative planning | Intra-operative decision making |
| Classification | Morphological (Cell shape) | Molecular (Genetic code) |
Strategic Rollout Across UK Specialist Centres
This pilot is described as a “world first” in terms of a health service rolling out such technology across multiple hospitals simultaneously. The initiative is currently active in five specialist centres: Nottingham University Hospitals, University Hospitals Birmingham, Great Ormond Street Hospital, King’s College Hospital, and Newcastle Hospitals.

The goal is not to render traditional pathology obsolete but to complement it. The rapid test provides the immediate “fingerprint” needed for surgical and urgent triage, while traditional methods provide the broader structural context. Following the initial phase, the NHS plans to extend the pilot to sites in Bristol, Oxford, Leeds, and Manchester.
Limitations and intended use of rapid genomic testing
While rapid genomic testing is a diagnostic tool rather than a treatment, it is important to understand its limitations. This test is intended for use during surgical intervention; it is not a screening tool for the general public. It is a complement to, not a replacement for, a full pathology report.
The decision to use rapid sequencing is made by the surgical team based on the patient’s specific clinical presentation and the goals of the surgery.
The Future of Intra-operative Molecular Diagnostics
The ability to identify a glioblastoma—one of the most aggressive forms of brain cancer—within 20 minutes of the machine running is a transformative leap. By removing the agony of the waiting period, the medical community can shift the focus from “what is it?” to “how do we treat it?” as soon as the patient leaves the operating theatre.
References
