
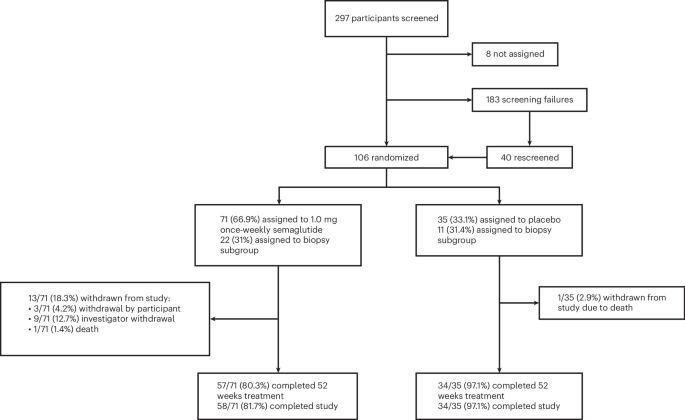
Recent clinical trials demonstrate that the glucagon-like peptide-1 receptor agonist semaglutide significantly reduces the risk of major kidney disease events in patients with type 2 diabetes.
In Plain English: The Clinical Takeaway
- What was tested: Semaglutide, a medication mimicking the GLP-1 hormone, was evaluated for its ability to protect kidney function in diabetic patients.
- The core finding: Participants taking the drug experienced a slower decline in kidney filtration rates and lower rates of severe renal decline.
- Why it matters: It provides a targeted pharmacological option to reduce the heavy burden of chronic kidney disease linked to type 2 diabetes.
Evaluating Renal Outcomes in Type 2 Diabetes
Diabetic kidney disease remains a primary driver of end-stage renal disease globally. According to data tracked in the Lancet Global Burden of Disease study, the prevalence of chronic kidney disease continues to strain public health infrastructure (Collaborators, 2025). Clinical investigators designed trials to test whether metabolic therapies like semaglutide could modify this trajectory.
The randomized, double-blind, placebo-controlled trial tracked clinical markers including estimated glomerular filtration rate, commonly known as eGFR (Levey et al., 2009). The eGFR measures how well filters in the kidneys remove waste from the blood. Participants receiving semaglutide demonstrated a statistically significant attenuation in the loss of this filtration capacity compared to the control group. Furthermore, exploratory analyses by Mann et al. (2021) and subsequent mechanistic investigations like the REMODEL trial (Cherney et al., 2025) point to direct anti-inflammatory and vascular protective pathways within renal tissue.
| Trial / Study | Intervention | Primary Focus | Key Finding |
|---|---|---|---|
| Perkovic et al., 2024 | Semaglutide vs. Placebo | Kidney outcomes in type 2 diabetes | Reduced risk of major kidney disease events and slowed eGFR decline. |
| SELECT Trial (Colhoun et al., 2024) | Semaglutide vs. Placebo | Obesity and cardiovascular disease | Observed secondary renal benefits in non-diabetic and high-risk cohorts. |
| SURPASS-4 (Heerspink et al., 2023) | Tirzepatide vs. Insulin Glargine | Cystatin C-based kidney function | Demonstrated comparative biomarker improvements in renal subsets. |
Mechanisms of Renal Protection and Cellular Signalling
Understanding how GLP-1 receptor agonists alter kidney pathology requires examining cellular distribution. Pyke et al. (2014) mapped GLP-1 receptors in human and non-human primate tissue, confirming their presence in the renal vascular tree. Activation of these receptors modifies renal autoregulation and dampens the receptor for advanced glycation end products, abbreviated as RAGE (Sourris et al., 2024). By suppressing RAGE-induced inflammation, semaglutide helps mitigate the fibrotic scarring that characterizes advanced diabetic nephropathy.
Additional mechanistic insights come from studies evaluating renal sinus fat and lipid accumulation. Foster et al. (2011) and Spit et al. (2020) established links between fatty kidney phenotypes, systemic hypertension, and functional decline. By improving glycemic control and inducing weight loss, therapies like semaglutide alleviate local lipotoxicity within renal parenchyma. This multimodal action bridges metabolic regulation with localized tissue preservation.
Regulatory Alignment and Future Research Horizons
Future trials, including multimodal tissue-centered studies outlined by Pruijm et al. (2026), aim to isolate the exact cellular pathways responsible for differential patient responses. As clinical practice adapts, these therapies offer a structured pathway to alter the long-term prognosis of millions living with diabetic kidney complications.
References
- Perkovic, V. et al. Effects of semaglutide on chronic kidney disease in patients with type 2 diabetes. N. Engl. J. Med. 391, 109–121 (2024).
- Colhoun, H. M. et al. Long-term kidney outcomes of semaglutide in obesity and cardiovascular disease in the SELECT trial. Nat. Med. 30, 2058–2066 (2024).
- Collaborators, G. C. K. D. A population-based evaluation of adult chronic kidney disease across global, regional, and national scales from 1990 to 2023, alongside associated risk drivers: an assessment for the Global Burden of Disease 2023 project. Lancet 406, 2461–2482 (2025).
- Cherney, D. Z. I. et al. Objectives, framework, and baseline profiles of REMODEL: an evaluation investigating semaglutide’s mechanism of action in individuals with type 2 diabetes and chronic kidney disease. Nephrol. Dial. Transpl. 40, 2182–2192 (2025).
- Pruijm, M. et al. Repurposing REMODEL for renal investigations: utilizing a multi-faceted, tissue-focused strategy to define semaglutide’s functional pathway in the kidneys. Kidney Int. 109, 6–16 (2026).
Disclaimer: This article is for informational purposes only and does not constitute medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions regarding a medical condition.
