
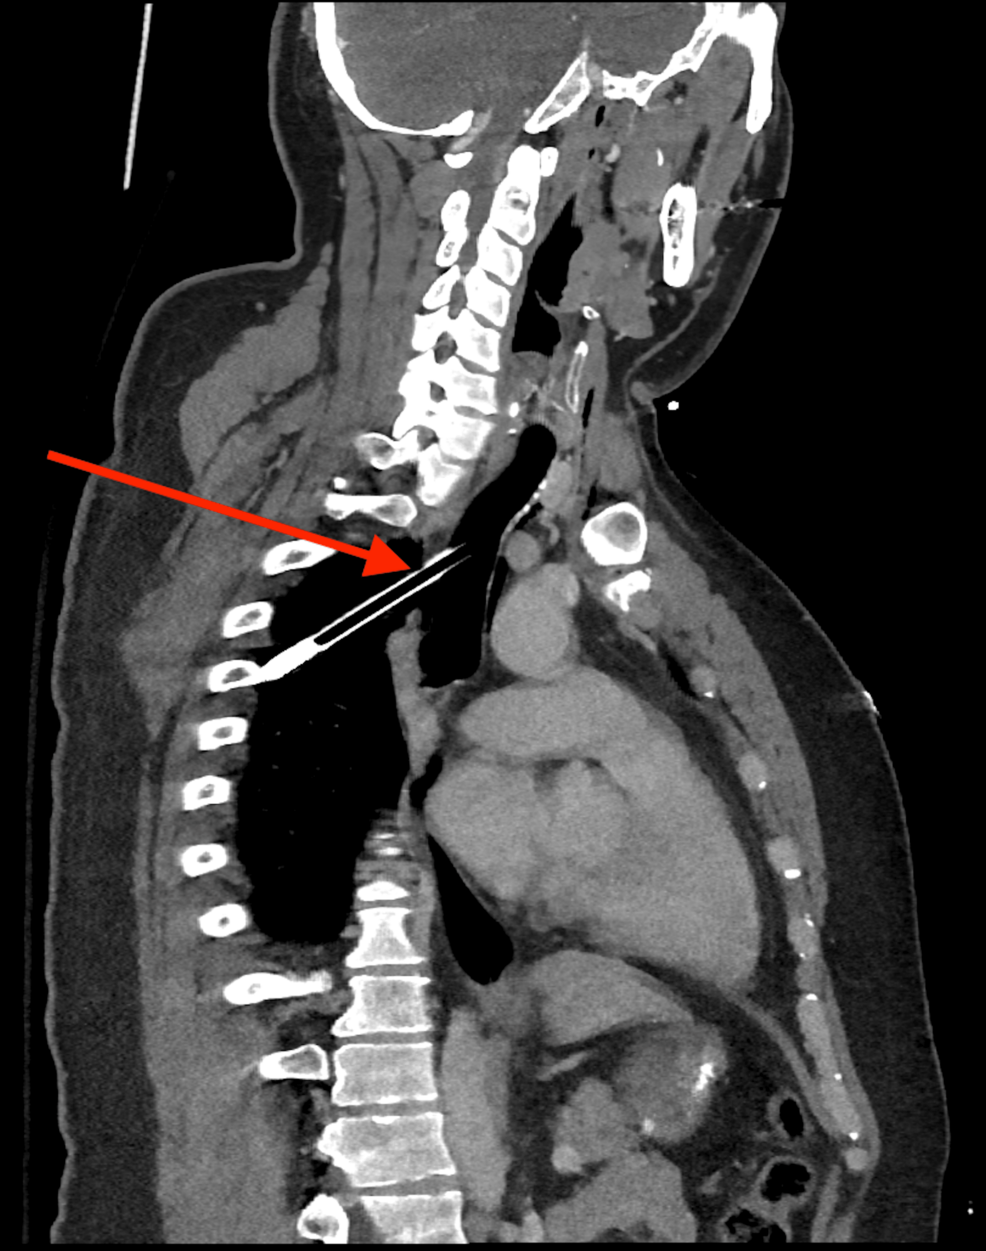
A 34-year-old man who sustained a penetrating neck injury from a crossbow arrow was successfully managed using early venovenous extracorporeal membrane oxygenation (VV ECMO) as a bridge to awake bronchoscopy and robotic surgical extraction, according to a case report.
Penetrating tracheal injuries present challenges for airway management, ventilation, and surgical repair due to the risk of rapid airway decline. Standard intubation or mechanical ventilation can exacerbate tissue damage, create false passages, or precipitate acute respiratory failure. By initiating VV ECMO prior to anesthesia, the medical team maintained oxygenation and ventilation without manipulating the injured airway.
In Plain English: The Clinical Takeaway
- VV ECMO: A means to maintain oxygenation and ventilation without manipulating a tracheal injury prior to surgical repair. In this case, it allowed doctors to keep the patient oxygenated without manipulating the damaged trachea.
- Awake Bronchoscopy: A diagnostic procedure where a flexible lighted tube is inserted, letting clinicians map out the exact location of the tracheal trauma safely.
- Mediastinum: The central compartment of the chest cavity, which was traversed by the arrow in this patient.
Patient Presentation and Radiological Findings
The patient arrived at the emergency department after a crossbow accident at home. He had removed the exposed portion of the arrow himself prior to arrival, leaving the arrowhead and remaining shaft embedded in his neck and thorax. Upon physical examination, clinicians noted a 1 cm midline anterior neck wound with visible crepitus.
Computed tomography (CT) of the chest revealed a 7 cm arrow fragment traveling through the anterior midline chest into the superior mediastinum and terminating within the right superior lower lobe. Initial laboratory values, including a complete blood count and comprehensive metabolic panel, remained largely within normal parameters. A plain film chest X-ray confirmed the missile embedded within the right upper lung parenchyma alongside a small right apical pneumothorax and subcutaneous emphysema.
Surgical Intervention and ECMO Deployment
Given the risk of airway compromise with induction or movement, the clinical team deployed early VV ECMO. Awake bronchoscopy confirmed the precise path of the tracheal injury with the embedded foreign body still in place. The patient subsequently underwent a successful tracheal repair paired with robotic-assisted arrow extraction under ongoing ECMO support.
Intraoperatively, the patient was successfully weaned off the extracorporeal circuit. He was discharged from the hospital without complications.
Contraindications & When to Consult a Doctor
Extracorporeal membrane oxygenation is an option to consider in managing complex airway trauma.
Penetrating neck and chest trauma constitute emergency medical events. Any individual experiencing difficulty breathing, subcutaneous crepitus, or symptoms of thoracic injury following trauma must seek immediate emergency medical evaluation.
Unresolved Questions in Penetrating Airway Trauma
While the case highlights the utility of early VV ECMO in selected high-risk trauma presentations, the precise incidence of these injuries is unknown. Published case literature regarding ECMO utilization specifically for penetrating tracheal trauma remains limited. Future clinical reporting will need to determine standardized criteria for incorporating extracorporeal support routines into pre-hospital and early emergency department triage protocols.
Medical Data Summary
| Clinical Parameter | Patient Result | Reference Range |
|---|---|---|
| White Blood Cell Count (WBC) | 13.46 bil/L | 4.80 – 11.80 bil/L |
| Hemoglobin (Hgb) | 15.1 g/dL | 11.0 – 16.0 g/dL |
| Platelets | 232 bil/L | 140 – 340 bil/L |
| International Normalized Ratio (INR) | 0.9 | 0.8 – 1.1 |
| Venous Lactate | 2.6 mMol/L | 0.5 – 2.0 mMol/L |
References
- Cureus: Venovenous Extracorporeal Membranous Oxygenation for Tracheoparenchymal Trauma: A Case Report.
Disclaimer: This article is intended for informational and educational purposes only and does not substitute for professional medical advice, diagnosis, or emergency intervention.
