
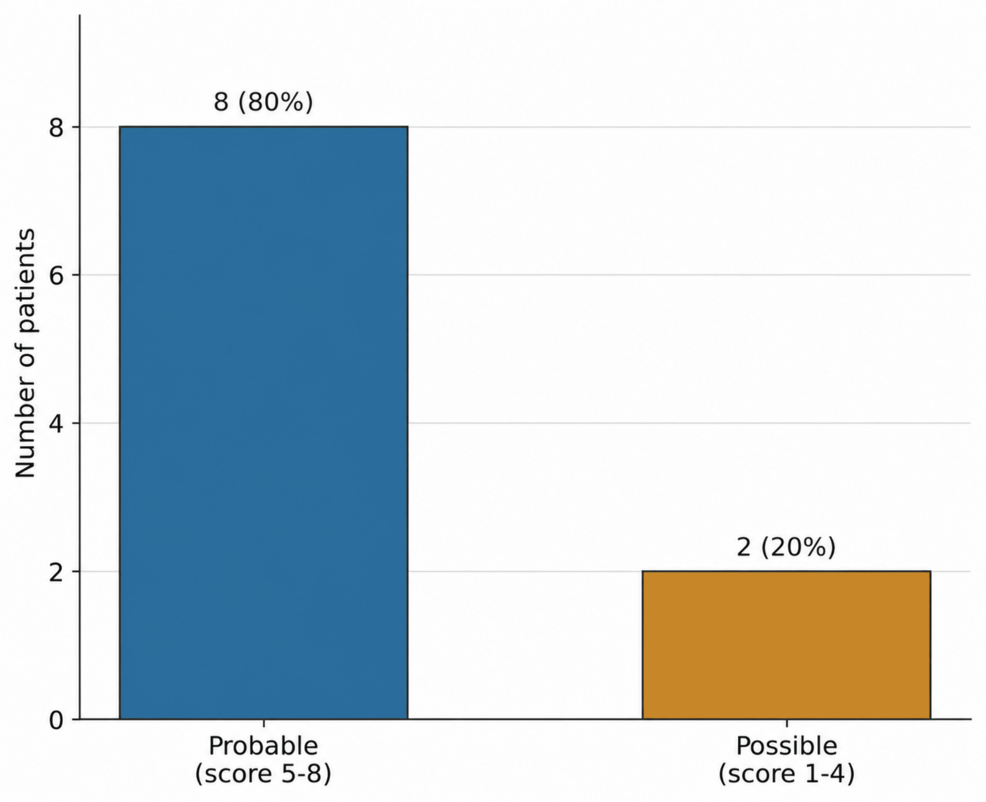
Polypharmacy—the concurrent use of five or more medications—poses severe, under-recognized risks to the oral cavity, according to a prospective observational case series published in Cureus. Researchers at a tertiary care teaching hospital tracked ten adult patients and found that 80% of drug-induced oral adverse reactions were classified as probable, with antihypertensives and anticholinergics most frequently implicated.
The consequences of taking multiple medications extend far beyond systemic pharmacokinetic and pharmacodynamic interactions. While internal medicine frameworks routinely monitor renal, hepatic, and cardiovascular parameters, the oral mucosa and salivary glands remain largely neglected during routine medication reconciliation. Drug-induced oral manifestations severely compromise oral health-related quality of life, leading to secondary complications such as accelerated dental caries, opportunistic infections, and nutritional deficiencies caused by impaired chewing and swallowing.
- Look beyond internal organs: Daily medications for blood pressure, mood, or seizures frequently cause dry mouth or gum changes that require dental oversight.
- Medication counts matter: Taking five or more drugs simultaneously significantly raises the statistical probability of developing localized mucosal and functional oral toxicities.
- Interdisciplinary care is essential: Routine dental check-ups paired with pharmacist-led medication reviews can catch adverse reactions before they cause permanent structural damage.
Clinical Spectrum of Drug-Induced Oral Toxicity
The prospective case series evaluated ten adult patients with a mean age of 67.8 years, where 60% of the cohort were male. Each participant was actively taking between five and eight concurrent systemic medications and presented with new-onset oral lesions or functional oral impairments. Using a structured evaluation protocol, the interdisciplinary team—comprising dental specialists, pharmacologists, and community medicine physicians—documented a diverse range of adverse reactions.
Functional salivary impairment, specifically xerostomia (chronic dry mouth), and structural modifications such as gingival overgrowth each accounted for 20% of the observed cases. Persistent dry mouth drastically reduces natural salivary protection, leaving dental enamel vulnerable to rapid decay. Other documented manifestations in broader clinical literature include lichenoid drug eruptions, erythema multiforme, angioedema, and the severe condition known as medication-related osteonecrosis of the jaw (MRONJ).
| Clinical Parameter | Observed Finding / Assessment Scale | Percentage of Cohort / Score |
|---|---|---|
| Cohort Demographics | Mean Age 67.8 years (60% Male) | N = 10 patients (5–8 drugs each) |
| Most Frequent Oral ADRs | Xerostomia and Gingival Overgrowth | 20% each |
| Causality Assessment | Naranjo Probability Scale (Probable vs. Possible) | 80% Probable, 20% Possible |
| Severity Index | Modified Hartwig and Siegel Scale (Moderate) | 70% Moderate severity |
| Preventability Metric | Schumock and Thornton Criteria (Probably Preventable) | 60% Probably preventable |
Causality, Severity, and Preventability Metrics
To establish objective scientific rigor, the investigators utilized validated clinical pharmacology tools. Causality assessment via the Naranjo Adverse Drug Reaction Probability Scale classified eight of the reactions as probable and two as possible, with none deemed doubtful or definitive. The drug classes most frequently implicated in these adverse events were antihypertensives—specifically calcium channel blockers and angiotensin-converting enzyme inhibitors—alongside anticholinergics and anticonvulsants.
Severity was measured using the Modified Hartwig and Siegel scale, which revealed that 70% of the reactions fell into the moderate category. Furthermore, application of the Schumock and Thornton criteria for preventability identified that over half of the documented oral adverse drug reactions—specifically 60%—were probably preventable. These metrics highlight a critical window for clinical intervention before minor mucosal irritations escalate into debilitating systemic or local pathologies.
Contraindications and When to Consult a Doctor
Patients managing multiple chronic conditions—particularly those prescribed calcium channel blockers, mood stabilizers, or anticholinergic agents—should remain vigilant for sudden changes in oral health. Individuals experiencing persistent dry mouth, unexplained gum tissue enlargement, painful mucosal ulcerations, or sudden alterations in taste (dysgeusia) must not abruptly discontinue prescribed therapies. Instead, patients should immediately consult their primary care physician, a clinical pharmacist, or a dentist to request a comprehensive medication reconciliation and safe therapeutic adjustment.
Interdisciplinary Pharmacovigilance Pathways
Diagnosing oral adverse drug reactions within a polypharmacy regimen remains a complex clinical challenge requiring coordinated oversight. The findings emphasize that active interdisciplinary collaboration among dental professionals, pharmacologists, and community health physicians is essential for early detection. Integrating routine dental evaluations into geriatric and chronic disease care frameworks can mitigate drug-induced oral morbidity, preserve masticatory function, and protect overall patient well-being.
References
- World Health Organization. International Drug Monitoring: The Role of National Centres. Technical Report Series No. 498.
- Cureus. Oral Adverse Drug Reactions in Patients Receiving Polypharmacy: A Prospective Interdisciplinary Case Series.
- Hartwig SC, Siegel J, Schneider PJ. Preventability and severity assessment in adverse drug reaction management. Am J Health Syst Pharm.
- Schumock GT, Thornton JP. The relative preventability of adverse drug reactions. Hosp Pharm.
- Naranjo CA, Busto U, Sellers EM, et al. A method for estimating the probability of adverse drug reactions. Clin Pharmacol Ther.
