
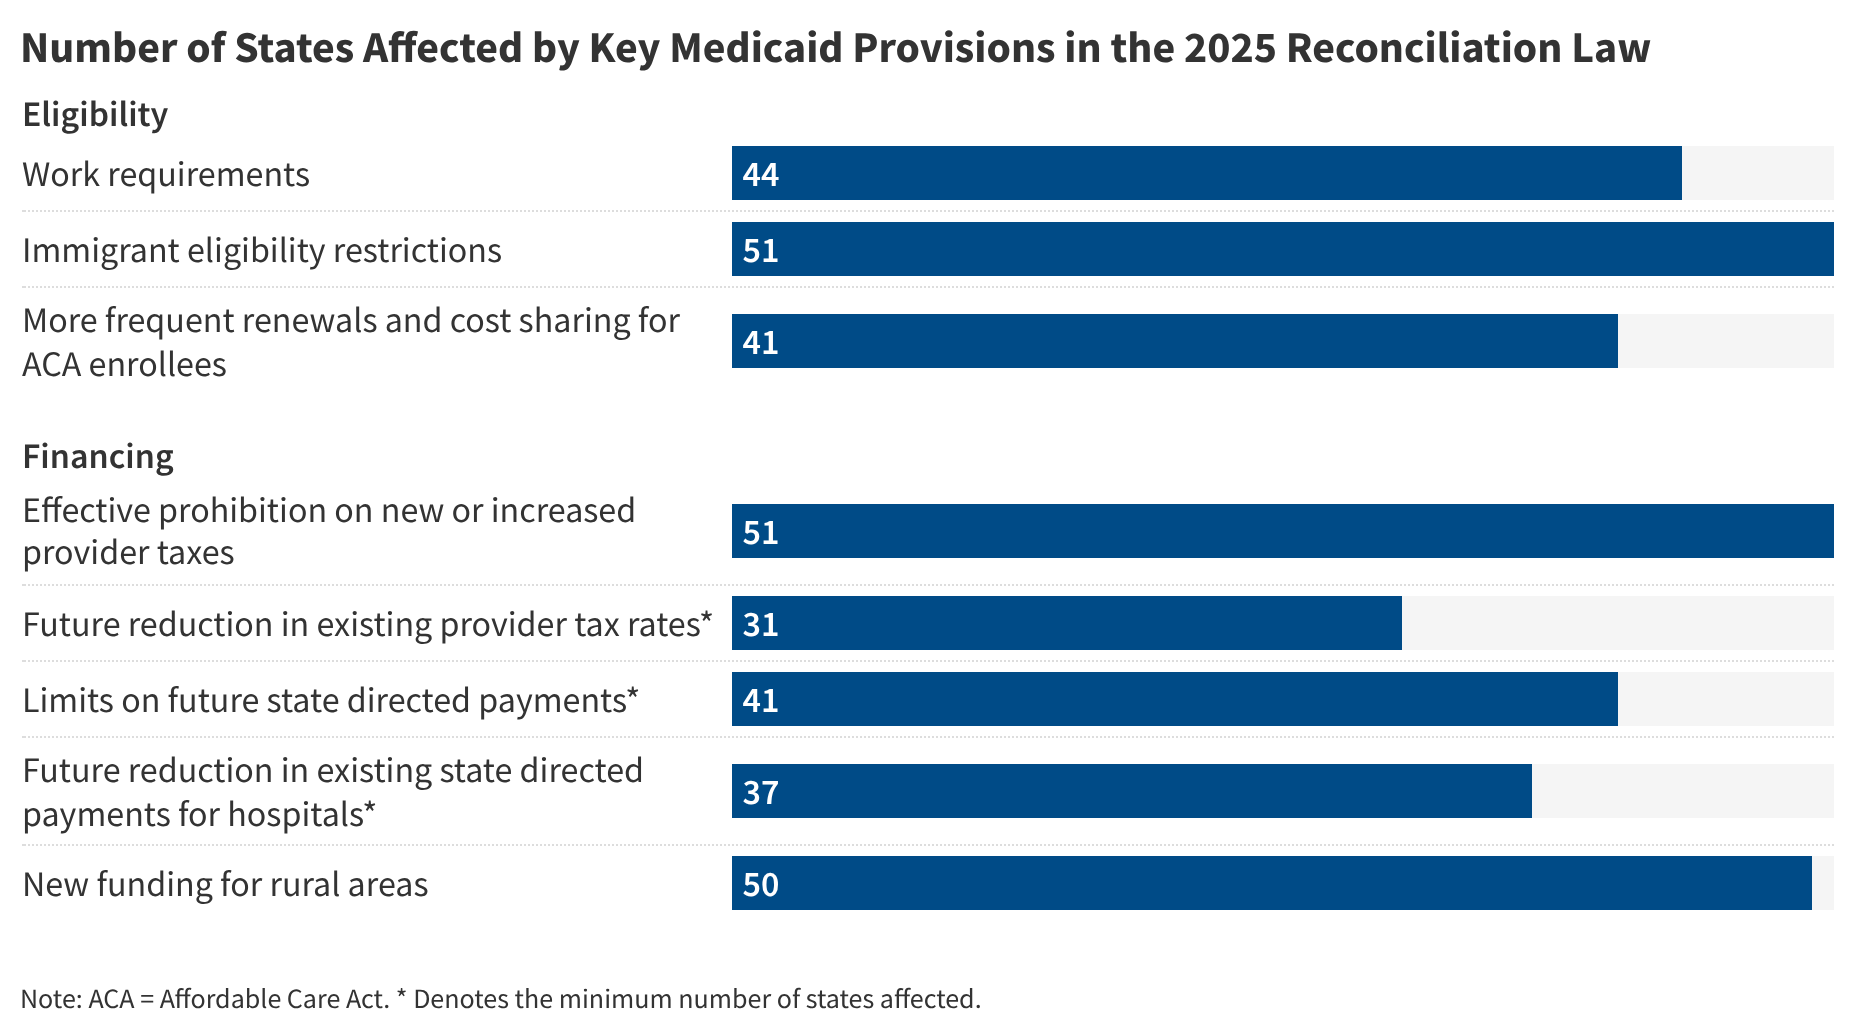
The 2025 reconciliation law is projected to reduce federal Medicaid spending by $911 billion between 2025 and 2034, increasing the uninsured population by 7.5 million in the final year while introducing severe financial and administrative strains across state healthcare systems, according to policy analyses.
In Plain English: The Clinical Takeaway
- Eligibility Reductions: New federal rules shorten renewal periods to every six months for expansion adults, alongside strict work requirements and tighter immigrant eligibility caps.
- Provider Reimbursement Cuts: Caps on state directed payments limit hospital reimbursement rates to near-Medicare levels, risking clinical staffing shortages and service cutbacks.
- Rural Health Grants: A temporary $50 billion rural health transformation fund provides five-year allotments to all 50 states, though these grants do not replace lost federal Medicaid revenue.
States Must Enforce Work Requirements and Frequent Redeterminations
The reconciliation law implements sweeping federal eligibility changes that alter how states administer safety-net healthcare. Forty-four states must now enforce work requirements for specific adult enrollees, conditioning coverage on employment or qualified exemptions. Forty-one Medicaid expansion states face the administrative mandate to conduct eligibility redeterminations every six months instead of annually for expansion adults.
These policy adjustments apply alongside stricter limits on lawfully present immigrants, restricting eligibility to only certain lawfully present immigrants, eliminating eligibility for many other groups such as refugees and asylees without a green card. The legislation also curtails retroactive healthcare coverage. Traditional enrollees are limited to two months of retroactive reimbursement for incurred medical expenses, while expansion enrollees receive only one month.
Payment Caps Decrease Hospital Reimbursement Rates
Beyond eligibility restrictions, the legislation imposes strict constraints on Medicaid financing mechanisms. New limitations cap state directed payments—which dictate how managed care organizations pay healthcare providers—at or near Medicare reimbursement rates. Starting in January 2028, hospital payment rates will decrease in at least 37 states that currently exceed these new thresholds.
Federal spending on state directed payments reaches approximately $93 billion annually, with $78 billion directed toward hospital services. Within that hospital allocation, an estimated $60 billion exceeds the new federal limits and faces impending reductions.
| Medicaid Provision | Scope of Impact | Effective Timeline |
|---|---|---|
| Work Requirements | 44 states (41 expansion, 3 non-expansion) | |
| 6-Month Eligibility Redeterminations | 41 Medicaid expansion states | |
| Immigrant Eligibility Restrictions | All 50 states and Washington D.C. | Active as of October 1, 2026 |
| State Directed Payment Caps | At least 37 states with payments exceeding limits | Effective January 1, 2028 |
Fiscal Constraints and Rural Health Fund Distribution
State budgets face compounding pressures from reduced provider tax revenues and declining overall Medicaid enrollment. The law restricts states from establishing new provider taxes or increasing existing rates. For ACA expansion states, the maximum percentage of net patient revenues collected from provider taxes decreases by 0.5 percentage points annually starting October 1, 2027, until reaching a floor of 3.5%.
To mitigate rural healthcare vulnerabilities, the legislation establishes a $50 billion rural health transformation fund distributed over five years. All 50 states receive first-year allocations, though per capita funding varies dramatically.
Electoral Trends and Administrative Execution
References
- Congressional Budget Office (CBO). Cost Estimate for Reconciliation Legislation. Federal Spending and Coverage Projections.
- Kaiser Family Foundation (KFF). Policy Analysis: State-Level Impacts of Medicaid Provisions in the 2025 Reconciliation Law.
