

Millions of children and adults in England live with obesity, yet a new parliamentary report reveals that NHS provision of life-changing weight-loss drugs remains severely restrictive. Published in response to sluggish rollouts, the findings urge the government to immediately streamline access by integrating regulated online pharmacies to curb a dangerous private black market.
In Plain English: The Clinical Takeaway
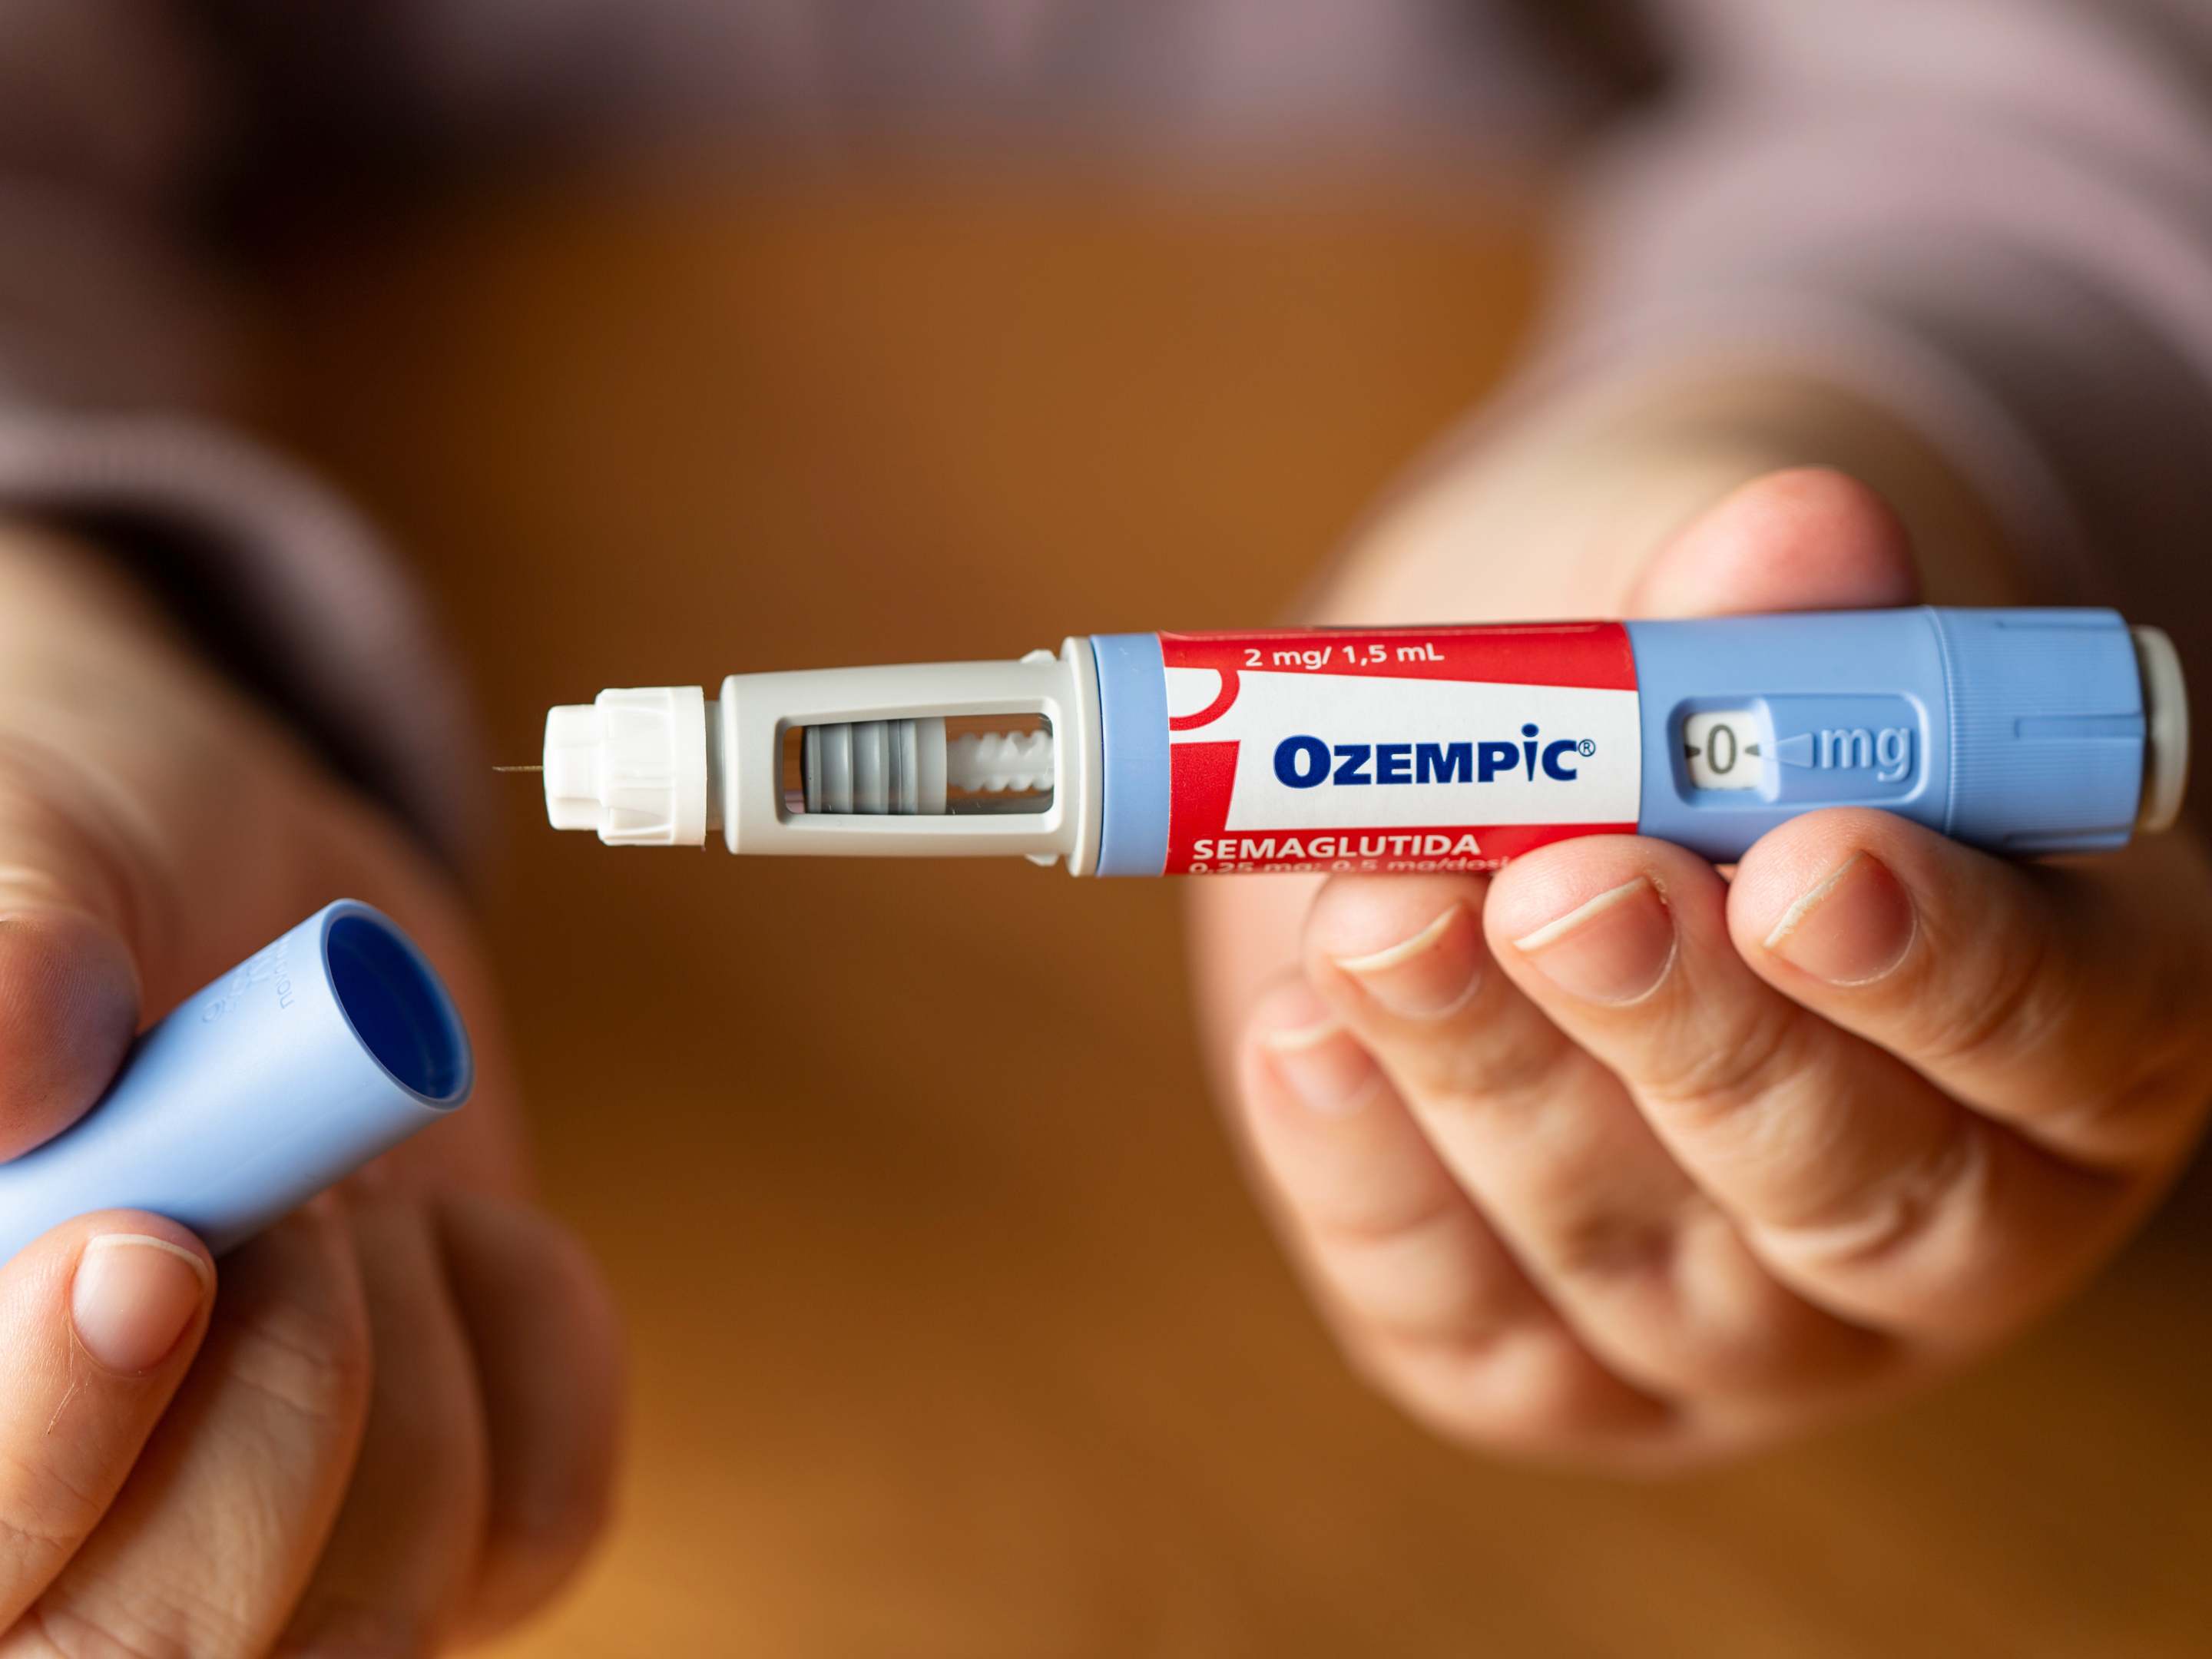
- GLP-1 Receptor Agonists: Injectable medications like tirzepatide (Mounjaro) and semaglutide mimic natural gut hormones to regulate insulin release, delay gastric emptying, and suppress appetite centers in the brain.
- The Two-Tier System: Disparities in supply have created a fractured landscape where patients who can afford private fees up to £300 a month bypass NHS waitlists entirely.
Health and Social Care Select Committee Urges Overhaul of Mounjaro NHS Rollout
Current plans to distribute effective weight-loss treatments across the National Health Service reach woefully few eligible patients, according to a report from the Health and Social Care Select Committee (HSCSC). Committee chair Layla Moran noted that obesity is a chronic, relapsing condition requiring structured support, yet the current implementation has inadvertently fostered a two-tier system dictated by personal wealth. During committee proceedings, patients described severe distress in accessing basic diet and exercise programs, bariatric surgery, or pharmaceutical interventions through standard NHS pathways.
Compounding this shortfall, an investigation by The Pharmacist in March revealed that integrated care boards (ICBs) across England are imposing localized thresholds far stricter than national guidelines. Certain regions mandate supervised weight-loss attempts prior to considering tirzepatide authorization, while other districts explicitly disqualify individuals presenting with unstable mental illnesses.
Private Pharmacies and the Rising Black Market Threat
With statutory provision lagging, many individuals turn to private channels, where out-of-pocket costs regularly scale up to £300 monthly. Industry leaders argue that community pharmacies could safely absorb a significantly larger patient volume if fully mobilized. Henry Gregg, chief executive of the National Pharmacy Association, stated in the report that community pharmacy is prepared to support a wider rollout to mitigate public health impacts and combat illicit supply chains. Malcolm Harrison, chief executive of the Company Chemists’ Association, added that independent prescribing pharmacists could establish a national pharmacy-led pathway alongside private services without delay.
However, this demand-supply mismatch has directly fueled a dangerous black market. Unlicensed and counterfeit GLP-1 alternatives circulate widely via social media platforms, often bypassing medical oversight. The HSCSC warned that the Medicines and Healthcare products Regulatory Agency (MHRA) appears to be playing catch up rather than proactively intercepting illegal traders, noting that several patients have already experienced acute medical harm.
Patient Efficacy Metrics Versus Gastrointestinal Tolerance
While regulators grapple with distribution bottlenecks, research published in the Journal of Medical Internet Research provides vital context regarding user adherence. Investigating real-world use of anti-obesity medications like semaglutide, Rutgers Health researchers utilized infoveillance methods to analyze public patient reviews. The findings indicate that perceived treatment efficacy—measured by tangible reductions in body weight and food cravings—serves as the primary driver of patient satisfaction and treatment continuation.
A key finding is that gastrointestinal adverse events such as nausea and vomiting affected 62% of respondents, yet these side effects did not significantly deter users who observed positive weight-loss outcomes. Conversely, individuals experiencing minimal weight reduction or non-gastrointestinal complications frequently terminated regimens. This behavioral data shows why demand remains exceptionally high despite high costs and physical discomfort.
| Clinical Parameter | Semaglutide Data (Rutgers Health Study) | Tirzepatide Context (HSCSC Report) |
|---|---|---|
| Primary Mechanism | GLP-1 Receptor Agonist | Dual GIP/GLP-1 Receptor Agonist |
| Reported GI Side Effects | 62% of users (nausea, vomiting) | Common; monitored via regulated channels |
| Primary Dropout Predictor | Lack of perceived efficacy | Prohibitive private cost (£300/mo) or strict NHS thresholds |
Next Steps for Regulatory Alignment
To bridge the divide between public need and private accessibility, the committee has formally recommended that the government convene a summit on GLP-1 access involving healthcare providers and clinical specialists. The report also states that regulated digital pharmacies require secure access to shared patient health records to update treatment status safely. As the government prepares its formal response, public health officials face mounting pressure to establish effective digital integration, reinforce MHRA enforcement powers, and eliminate the postcode lottery currently defining obesity care in England.
References
- Health and Social Care Select Committee. (2026). Report on weight-loss drug rollout and online pharmacy utilization. UK Parliament.
- Armanious, A., & James, M. (2025). Why People Won’t Quit a Weight Loss Drug – Even When It Makes Them Feel Sick. Journal of Medical Internet Research. Rutgers School of Public Health.
- The Pharmacist. (2026). Investigation into integrated care board prescribing thresholds for tirzepatide.
- Medicines and Healthcare products Regulatory Agency (MHRA). Guidance on counterfeit GLP-1 products and online safety enforcement.
