
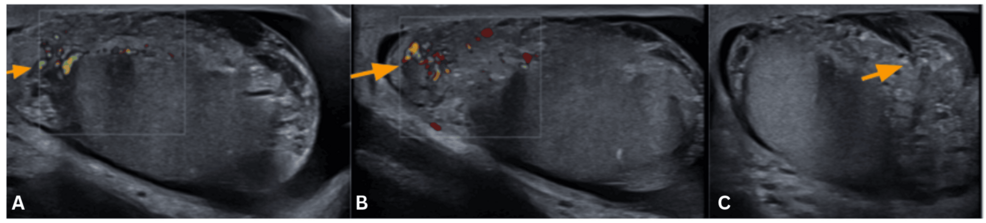
A 19-year-old male patient experienced a delayed diagnosis of subacute testicular torsion initially misidentified as epididymitis, as reported in Cureus. Despite antibiotic treatment and initial ultrasound findings showing preserved blood flow, serial imaging over three months revealed complete testicular infarction, documented through magnetic resonance imaging and contrast-enhanced ultrasound.
In Plain English: The Clinical Takeaway
- Subacute Torsion: When a testicle twists slowly rather than suddenly, blood flow can look normal on early scans, leading doctors to mistake the condition for a standard infection like epididymitis.
- Advanced Imaging: If initial treatments fail or symptoms persist, specialized scans like contrast-enhanced ultrasound and MRI are critical to spot hidden vascular blockages before permanent damage sets in.
- Conservative Management: Once complete tissue death (infarction) occurs and the patient is free of cancer risk and pain, doctors may choose to monitor the condition rather than operate immediately.
Initial Presentation and Misdiagnosis of Scrotal Pain
The 19-year-old patient originally arrived at the emergency department reporting a one-day history of left testicular pain and swelling, accompanied by normal vital signs and a white blood cell count of 6.7 × 10⁹/L. According to the case documentation in Cureus, a regional urology team was consulted immediately.
Scrotal Doppler ultrasound performed at initial assessment revealed a swollen, hyperemic left epididymis alongside preserved intratesticular blood flow. Medical staff established a working diagnosis of acute left epididymitis. The patient was discharged with a course of antibiotics and scheduled for an outpatient follow-up at a surgical ambulatory clinic two weeks later.

Clinical Deterioration and Three-Month Imaging Findings
The patient returned five days after his initial visit reporting worsening left testicular pain, while his C-reactive protein levels had climbed to 24 mg/L. Despite these worsening inflammatory markers and increased discomfort, the clinical team maintained the diagnosis of epididymitis, advised him to finish his antibiotics, and did not order a repeat ultrasound or immediate surgical exploration.
At the three-month mark, a follow-up ultrasound displayed a dramatic structural shift. The head of the left epididymis was replaced by a solid mass measuring 25 by 24 millimeters, and the left testicle appeared diffusely hypoechoic. This unusual appearance prompted an urgent MRI scan, which revealed uniformly low T2-weighted and high T1-weighted signal intensities characteristic of hemorrhagic infarction, alongside a distinct whirlpool sign.
Multidisciplinary Review and Contrast-Enhanced Ultrasound Confirmation
Following the MRI results, a local multidisciplinary team comprising radiology, urology, and histopathology specialists convened in Month 4 to rule out testicular germ cell tumors. Tumor markers including alpha-fetoprotein, human chorionic gonadotropin, and lactate dehydrogenase all returned within normal limits.
To definitively assess microvascular perfusion, the care team performed a contrast-enhanced ultrasound in Month 4, Week 2. The scan confirmed a complete absence of intratesticular microvascular perfusion, leaving only capsular vessels visible. With tumor markers normal and advanced imaging confirming tissue death, the patient was cleared from the cancer pathway and managed conservatively given that he was asymptomatic.
| Investigation Parameter | Patient Result | Reference Range |
|---|---|---|
| White Cell Count (Day 0) | 6.7 × 10⁹/L | 4.0–11.0 × 10⁹/L |
| C-Reactive Protein (Day 0) | <1 mg/L | <5 mg/L |
| C-Reactive Protein (Day 5) | 24 mg/L | <5 mg/L |
| Alpha-Fetoprotein (Month 4) | 1.5 kU/L | <7.5 kU/L |
Contraindications & When to Consult a Doctor
Patients presenting with acute scrotal pain, swelling, or lower abdominal discomfort should seek immediate medical evaluation at an emergency department. Testicular torsion is a time-critical urological emergency where delays can lead to irreversible ischemia. Conservative management, as seen in this chronic, late-stage case where the tissue had already undergone complete infarction and the patient was asymptomatic, is strictly reserved for specialized clinical scenarios ruled safe by a multidisciplinary team. Active torsion requires emergency surgical intervention to save the testicle; patients must never ignore acute scrotal symptoms or rely solely on antibiotic therapy if pain persists.
References
- Cureus: Subacute Testicular Torsion Initially Diagnosed As Epididymitis: MRI and Contrast-Enhanced Ultrasound Findings of Complete Testicular Infarction.
