
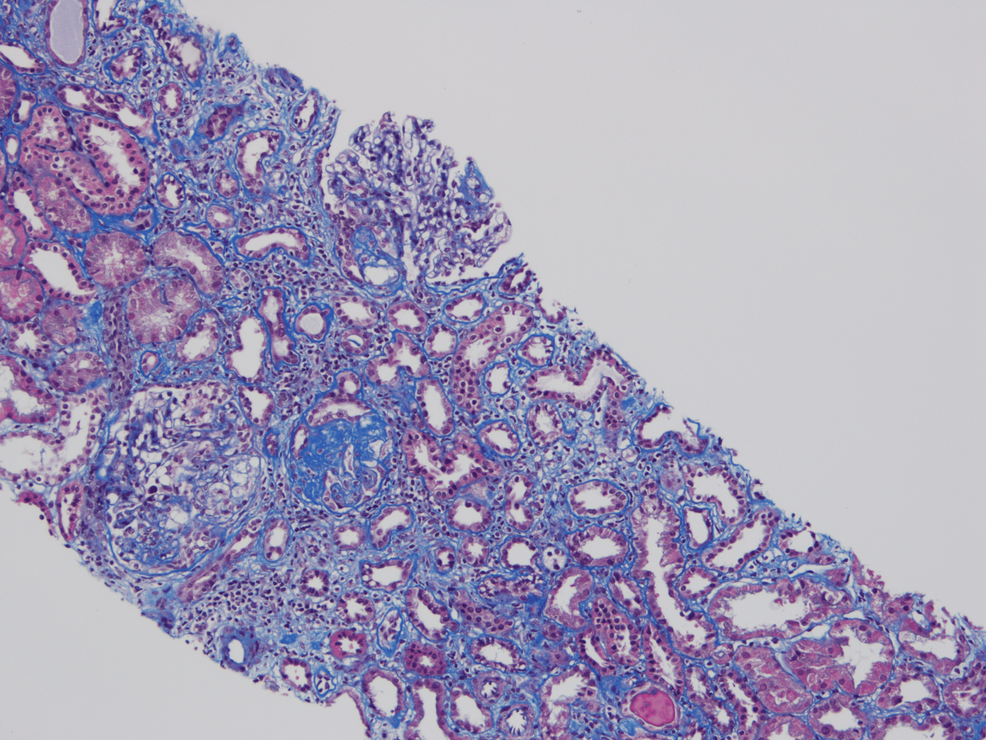
A 20-year-old woman presented with severe arterial hypertension and heavy nephrotic-range proteinuria of 14 grams per 24 hours, ultimately culminating in end-stage kidney disease. reported that despite initial management targeting focal segmental glomerulosclerosis, comprehensive ultrastructural re-evaluation revealed immunoglobulin A nephropathy, demonstrating how diagnostic challenges in atypical presentations can complicate clinical outcomes.
In Plain English: The Clinical Takeaway
- The Core Condition: IgA nephropathy usually causes blood in the urine, but in rare cases, it manifests as nephrotic syndrome—a heavy loss of protein through the kidneys accompanied by severe swelling and high cholesterol.
- The Diagnostic Pitfall: Initial light microscopy can sometimes misidentify the primary damage as focal segmental glomerulosclerosis (FSGS), which changes how doctors approach treatment and delays the correct identification of immune deposits.
- The Long-Term Outcome: Even when patients show a partial response to corticosteroids and immunosuppressive drugs like cyclosporine, advanced scarring on a kidney biopsy can lead to progressive renal decline and the eventual need for dialysis.
Unraveling the Initial Presentation and Diagnostic Shift
The clinical picture began when the 20-year-old patient was referred for evaluation of severe arterial hypertension accompanied by occipital headaches, photophobia, and vomiting. Baseline laboratory testing confirmed severe nephrotic syndrome, highlighted by a 24-hour urinary protein excretion of 14 grams, a serum albumin level of 2.1 grams per deciliter, and profound dyslipidemia with a total cholesterol reading of 825 milligrams per deciliter.
Initial renal biopsy demonstrated focal segmental glomerulosclerosis. Interstitial fibrosis and tubular atrophy impacted approximately 60 percent of the sampled cortex. Based on this working diagnosis, clinicians initiated corticosteroid therapy with prednisolone at 1 milligram per kilogram daily. While this intervention reduced proteinuria and improved serum albumin, heavy protein loss persisted, prompting the addition of cyclosporine at 100 milligrams twice daily.

Advanced Histopathology and Treatment Evolution
Subsequent ultrastructural analysis using electron microscopy changed the clinical trajectory. The re-evaluation revealed diffuse podocyte foot-process effacement alongside mesangial expansion and immune-type electron-dense deposits. These findings confirmed that the underlying pathology was IgA nephropathy—featuring marked chronic damage rather than primary focal segmental glomerulosclerosis. Immunofluorescence evaluation was non-contributory because no glomeruli remained in that specific submitted specimen block.
Throughout the treatment timeline, kidney function continued to drift downward despite therapeutic cyclosporine trough levels and ongoing renin-angiotensin system blockade with irbesartan at 300 milligrams daily. In July 2023, the patient’s serum creatinine sat at 1.33 milligrams per deciliter with an estimated glomerular filtration rate of 51.4 milliliters per minute. By January 2024, a relapse during corticosteroid tapering led clinicians to increase the prednisolone dose and add cyclosporine. Although proteinuria dropped temporarily, renal function deteriorated further.

Contraindications & When to Consult a Doctor
Patients presenting with sudden, unexplained edema, severe fatigue, or frothy urine must seek prompt nephrological evaluation to rule out nephrotic-range proteinuria. When advanced renal biopsies reveal extensive interstitial fibrosis and tubular atrophy—indicating irreversible chronic structural damage—high-dose immunosuppressive therapies like corticosteroids or calcineurin inhibitors such as cyclosporine are typically discontinued. Continuing aggressive immunosuppression in the face of established scarring risks severe drug-induced nephrotoxicity without offering functional renal recovery. Clinicians must carefully weigh biopsy-proven chronicity before committing patients to prolonged, potentially harmful immunomodulatory regimens.
Long-Term Prognostic Implications and Renal Replacement Therapy
Following a prolonged period of loss to follow-up, the patient returned in August 2024 with recurrent nephrotic-range proteinuria and uncontrolled hypertension, requiring an intensification of antihypertensive medications including diltiazem. A comprehensive biopsy review in January 2025 confirmed advanced chronic changes, prompting the complete discontinuation of immunosuppressive medications in favor of a conservative management strategy focusing on blood pressure optimization and dietary sodium restriction. Despite these intensive supportive measures, the structural damage proved irreversible, and the patient progressed to end-stage kidney disease, requiring hemodialysis initiation in September 2025 and transition to peritoneal dialysis in October 2025, approximately 26 months after her initial clinical presentation.
References
- Cureus. Nephrotic Syndrome as the Initial Presentation of IgA Nephropathy: A Case Report.
