
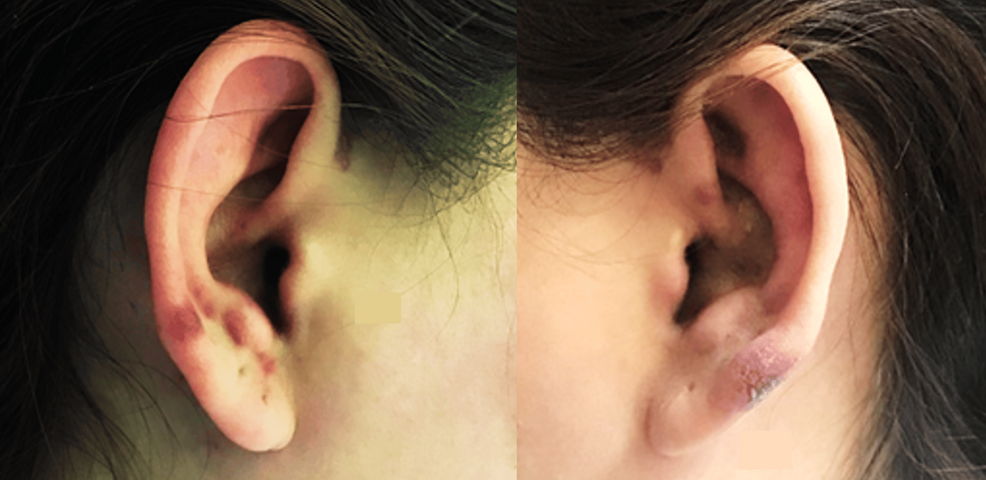
A 31-year-old woman in East Asia presented to an emergency department with purple earlobe lesions measuring 2 to 10 millimeters, driven by severe thrombocytopenia and anemia.
Key Medical Terms for SLE and HLH
- Systemic Lupus Erythematosus (SLE): A chronic autoimmune disease where the immune system mistakenly attacks healthy tissues across multiple organ systems.
- Thrombocytopenia: A dangerously low blood platelet count that impairs normal blood clotting, leading to unexpected bleeding and purpura (purple skin spots).
- Hemophagocytic Lymphohistiocytosis (HLH): A rare, hyperinflammatory syndrome marked by an overactive immune response that can cause multi-organ failure if left untreated.
Diagnostic Challenges of Atypical Cutaneous Manifestations
The patient arrived at the emergency department with a two-week history of purple discoloration on both earlobes, unaccompanied by trauma or skin lesions elsewhere on the body. Initial questioning revealed systemic symptoms including fatigue, gum bleeding, epistaxis, and intermenstrual bleeding. A full blood count displayed a critical platelet count of 8 x 10⁹/L and normocytic anemia with a hemoglobin level of 92 g/L. Because isolated earlobe purpura without facial rashes is exceptionally rare in adult SLE presentation, the initial medical team suspected immune thrombocytopenia and administered intravenous immunoglobulin and tranexamic acid.
Further investigation via peripheral blood smear showed dysplastic neutrophils, prompting computed tomography imaging that revealed generalized lymphadenopathy. Bone marrow aspiration, trephine biopsy, and a cervical lymph node biopsy were subsequently performed. Rheumatology consultation confirmed that vasculitis alone could not account for the severe hematological abnormalities. Subsequent autoimmune serology revealed a strongly positive speckled antinuclear antibody titer of 1:5120, alongside elevated anti-Sm and anti-dsDNA antibodies exceeding 350 IU/mL. Complement levels for C3 and C4 were profoundly suppressed, and urinalysis indicated elevated protein-creatinine ratios, satisfying criteria for a working diagnosis of systemic lupus erythematosus.
Escalation to Secondary Hemophagocytic Lymphohistiocytosis
Despite the administration of intravenous immunoglobulin and a three-day methylprednisolone pulse starting at 60 mg daily, the patient’s hematological markers failed to improve. By Day 7 of admission, laboratory findings showed a rapidly escalating ferritin level paired with declining fibrinogen, signaling the onset of secondary hemophagocytic lymphohistiocytosis. Clinicians calculated an HScore of 172 points on Day 8, corresponding to an estimated 54% to 70% probability of hemophagocytic syndrome, driven by a ferritin spike to 5,823 µg/L and a triglyceride elevation to 7.4 mmol/L.
To target the underlying autoimmune trigger and suppress the hyperinflammatory cascade, local specialists urgently authorized treatment with rituximab, a monoclonal antibody designed to deplete CD20-positive B-cells and reduce autoantibody production. Within four days of receiving a 1,000 mg intravenous dose of rituximab, the patient’s platelet count more than tripled from 19 x 10⁹/L to 68 x 10⁹/L. Her hemoglobin stabilized, and ferritin levels dropped to 993 µg/L. She was discharged on Day 16 of admission.
| Clinical Parameter | Patient Value (Day 1) | Patient Value (Peak/Day 8) | Reference Range |
|---|---|---|---|
| Platelet Count | 8 x 10⁹/L | 22 x 10⁹/L | 150–400 x 10⁹/L |
| Serum Ferritin | 347 µg/L | 5,823 µg/L | 13–150 µg/L |
| Triglycerides | — | 7.4 mmol/L | 0–2.2 mmol/L |
Patient Maintains Stability on Outpatient Medication Regimen
Ten months following her initial hospital admission, the patient maintains clinical stability on an outpatient regimen of mycophenolate mofetil at 1,000 mg twice daily and hydroxychloroquine at 200 mg once daily, having successfully tapered off oral prednisolone. Recent laboratory evaluations confirm a stable hemoglobin level of 127 g/L and sustained platelet counts exceeding 200 x 10⁹/L. The case shows that doctors must maintain a broad differential diagnosis when atypical dermatological findings coincide with unexplained cytopenias.
References
- Cureus.
- Annals of Neurology.
