
An eight-year-old girl in Singapore presenting with unconfirmed migraine-type headaches, neck pain, and functional gastrointestinal symptoms experienced clinical improvement after 16 months of knee chest upper cervical chiropractic care, according to a case report published in Cureus by S. Rai. Because no neuroimaging or validated outcome measures were used, the case report cannot establish a causal link or rule out the natural history of an undiagnosed condition.
In Plain English: The Clinical Takeaway
- Unconfirmed Diagnosis: The patient’s headache was categorized as a differential diagnosis (tension-type versus possible migraine) rather than a definitive medical diagnosis, and her gastritis was identified via symptoms and stool analysis without endoscopic confirmation.
- Knee Chest Upper Cervical Chiropractic (KCUC): This specialized chiropractic approach focuses on the atlanto-occipital and atlanto-axial regions of the upper neck, utilizing postural analysis, leg-length assessments, and low-force adjustments delivered while the patient is in a prone knee-chest position.
- Correlation Versus Causation: While the patient’s family reported relief in posture, arm symptoms, and abdominal pain during treatment—with symptoms returning during a period of missed appointments—the lack of advanced imaging means researchers cannot rule out spontaneous recovery.
Clinical Presentation and Diagnostic Workup in Singapore
The pediatric patient was brought to an upper cervical chiropractic clinic in Singapore by her mother, exhibiting a multi-month history of central abdominal pain, morning headaches featuring temporal pain, neck pain radiating down the arm with associated numbness, and episodic vomiting. Prior to seeking chiropractic intervention, the child underwent evaluations by both a general practitioner and a gastroenterologist. The general practitioner noted the headaches as a differential between tension-type headaches and possible migraines, stopping short of a confirmed diagnosis. Meanwhile, the gastroenterologist established a working diagnosis of gastritis based strictly on clinical presentation and stool analysis, bypassing advanced diagnostic procedures such as endoscopy or tissue biopsy because the attending physician deemed them unnecessary.
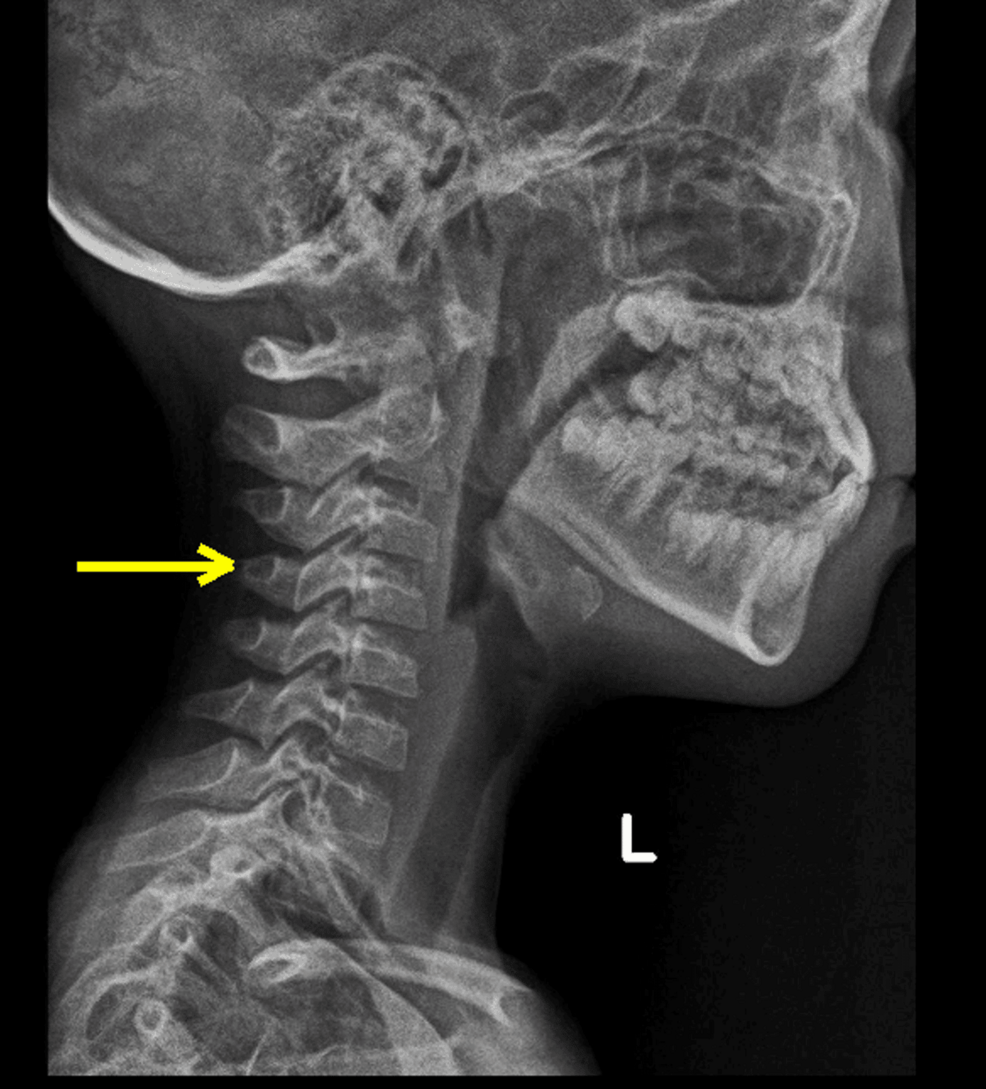
Physical examination at the chiropractic clinic revealed distinct postural and biomechanical abnormalities, including anterior head carriage, a right head tilt, restricted left lateral flexion, and limited right rotation. Prone testing demonstrated a short right leg that normalized upon cervical rotation, alongside manual muscle testing weakness linked to neck rotation. Radiographic imaging confirmed a loss of normal cervical lordosis—the natural inward curve of the neck—though no bony fractures or disc abnormalities were detected. These clinical signs aligned with upper cervical joint dysfunction, though they remained non-diagnostic for the patient’s primary pain complaints.
Mechanics of Knee Chest Upper Cervical Chiropractic Care
The patient was managed using knee chest upper cervical chiropractic (KCUC) care over an approximate 16-month period prior to her family relocating overseas. KCUC protocol is an analysis and technique-specific intervention directed specifically at the atlanto-occipital and atlanto-axial regions located at the top of the spinal column. Initial assessment involves postural analysis, leg-length evaluation, manual muscle testing, balance testing, and thermography to detect bilateral paraspinal skin temperature differentials, followed by radiographic confirmation before any physical adjustment is executed.
For this pediatric case, treatment began with an instrument-assisted technique before transitioning to gentle manual corrections as the patient tolerated them. The manual adjustments are delivered with the patient positioned prone in a knee-chest posture with the head rotated to one side, utilizing a precise, low-force, high-velocity low-amplitude thrust. According to the published case report, the family noted sustained improvements in posture, arm symptoms, and abdominal discomfort. Notably, a recurrence of the child’s abdominal symptoms coincided with a period of reduced visit adherence, though authors emphasized that these observations remain strictly hypothesis-generating.
| Clinical Parameter | Initial Assessment Findings | Observed Response to KCUC Care |
|---|---|---|
| Headache & Neck | Morning headaches with temporal pain; neck pain radiating to arm with numbness. | Reported improvement in arm symptoms and posture over 16 months. |
| Gastrointestinal | Central abdominal pain and episodic vomiting (working diagnosis of gastritis). | Reported reduction in abdominal pain; symptoms recurred during periods of low visit adherence. |
| Biomechanical | Anterior head carriage, right head tilt, restricted lateral flexion, loss of cervical lordosis. | Addressed via instrument-assisted and gentle manual upper cervical adjustments. |
Broader Pediatric Context and Evidence Landscape
Migraines and recurrent headaches are increasingly recognized within the pediatric demographic, frequently presenting alongside gastrointestinal manifestations such as recurrent abdominal pain, nausea, and vomiting. These overlapping complaints are clinically classified within the spectrum of episodic syndromes associated with migraine. Managing these presentations often requires navigating multiple pediatric subspecialists and prolonged trials of symptomatic medications before a unified underlying pattern is identified.
Existing literature explores various manual therapies for headache subtypes with varying levels of methodological rigor. Systematic review data indicate that manual therapies, including chiropractic spinal manipulation, may offer effectiveness comparable to pharmacological prophylaxis for migraines. Furthermore, a multi-center randomized trial demonstrated that upper cervical and upper thoracic spinal manipulation outperformed mobilization and exercise in treating cervicogenic headaches in adults, while an observational pilot study reported enhanced migraine-specific quality of life following atlas realignment. Specific to younger cohorts, a randomized, sham-controlled trial found that chiropractic spinal manipulation reduced recurrent headache frequency, and prior case reports have documented the resolution of chronic cervicogenic headaches in young children following similar care.
Because the clinical encounter lacked neuroimaging and validated standardized outcome measures, medical researchers cannot definitively distinguish the reported symptomatic improvements from the natural history of an undiagnosed pediatric condition. The case report published in Cureus explicitly stops short of establishing a causal or therapeutic claim, framing the account instead as a foundation for future academic inquiry. It remains unknown whether targeted upper cervical adjustments directly influence autonomic pathways affecting gastrointestinal function or if the observed clinical changes reflect unrelated spontaneous remission in a developing child.
References
- Rai, S. (2026). Migraine-Type Headache and Functional Gastrointestinal Symptoms of Unconfirmed Aetiology in a Paediatric Patient Managed with Knee Chest Upper Cervical Chiropractic Care: A Case Report. Cureus, 18(10), e117285. doi:10.7759/cureus.117285.
Disclaimer: This article is for informational purposes only and does not constitute medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition.
