
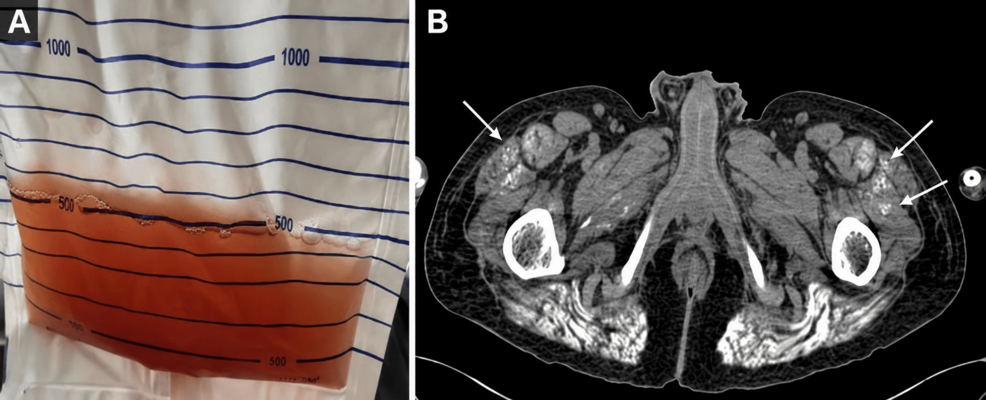
Two male patients presenting with dark-colored urine, severe muscle pain, and acute kidney injury were diagnosed with amphetamine-associated rhabdomyolysis requiring intensive hemodialysis. The findings underscore the severe renal and metabolic risks linked to amphetamine exposure.
In Plain English: The Clinical Takeaway
- Rhabdomyolysis: A serious medical condition involving the rapid breakdown of damaged skeletal muscle tissue, which releases muscle proteins and electrolytes directly into the bloodstream.
- Acute Kidney Injury (AKI): A sudden decline in kidney function that prevents the body from properly filtering waste products, frequently requiring temporary or prolonged dialysis (renal replacement therapy).
- Myoglobinuria: The presence of myoglobin—a muscle protein—in the urine, which causes a characteristic dark-brown discoloration and can directly damage kidney tubules.
Clinical Manifestations and Diagnostic Profiles of the Two Cases
The first patient, a 46-year-old man with no known medical history, arrived at the emergency department exhibiting high-grade fever, delirium, and severe diffuse myalgia. Initial laboratory evaluations revealed an extraordinarily high serum creatine kinase (CK) level of 947,699 U/L, far exceeding the normal clinical threshold. He also presented with a serum creatinine of 734 µmol/L and severe hyperkalemia of 6.8 mmol/L. Urine toxicology screens confirmed the presence of amphetamines. Despite undergoing eleven intermittent hemodialysis sessions alongside aggressive intravenous hydration, his renal function failed to recover. On hospital day 28, he developed severe hypercalcemia with a corrected calcium level of 4.10 mmol/L, accompanied by muscular calcifications visible on computed tomography. He suffered a refractory cardiac arrest and died shortly thereafter.
The second patient, a 42-year-old man, presented following a twenty-day history of flu-like symptoms, dark urine, and progressive deterioration. Transferred to the nephrology department after failing to respond to initial care at a peripheral facility, he displayed serum CK levels peaking at 525,796 U/L and an initial serum creatinine of 544 µmol/L, which subsequently rose to 875 µmol/L. Toxicological screening was similarly positive for amphetamines. After receiving ten intermittent hemodialysis sessions, this patient achieved a near-complete recovery of his renal function.
Pathophysiological Mechanisms and Exclusion of Alternative Etiologies
Amphetamines act as potent central nervous system stimulants. Their sympathomimetic properties induce profound psychomotor agitation, hyperthermia, and increased muscular activity. These physiological stressors directly predispose patients to rhabdomyolysis. Once muscle breakdown occurs, the massive efflux of intracellular constituents, particularly myoglobin and potassium, overwhelms the body’s clearance mechanisms. Myoglobin induces acute kidney injury via direct tubular toxicity, intrarenal vasoconstriction, and the formation of obstructive intratubular casts.
Because rhabdomyolysis stems from a diverse array of traumatic and non-traumatic triggers, establishing amphetamine exposure as the root cause requires systematic clinical evaluation. In both reported cases, clinicians investigated and ruled out alternative etiologies such as severe trauma, prolonged immobilization, recent strenuous exercise, alcohol binging, seizures, and myotoxic medications like statins. Urine toxicology served as the diagnostic confirmation, identifying the presence of amphetamines in tandem with clinical presentations marked by extreme enzyme elevations and dark urine.
When to Consult a Doctor
Prompt triage, toxicology screening, and early initiation of fluid resuscitation or renal replacement therapy are critical to mitigating life-threatening electrolyte imbalances and organ damage.
Therapeutic Interventions and Prognostic Heterogeneity
The management of severe amphetamine-associated rhabdomyolysis centers on aggressive supportive care, early restoration of intravascular volume, and aggressive correction of electrolyte disturbances such as hyperkalemia. When kidney injury progresses to anuric or oligoanuric states, intermittent hemodialysis becomes mandatory to manage fluid overload and clear toxic metabolic byproducts. The clinical trajectories of these two patients highlight the prognosis of the syndrome, demonstrating that outcomes can range from successful renal recovery to fatal cardiovascular and metabolic complications, including delayed hypercalcemia and metastatic muscular calcinosis.
