
Distal renal tubular acidosis is classically characterized by a normal anion gap, but two pediatric cases recently detailed in a medical report published by Cureus reveal an unusual presentation featuring high anion gap metabolic acidosis driven by co-existing organic acid metabolic disturbances.
In Plain English: The Clinical Takeaway
- Distal Renal Tubular Acidosis (dRTA): A condition where the kidneys fail to properly excrete acid into the urine, causing the body’s blood to become too acidic.
- High Anion Gap Metabolic Acidosis (HAGMA): A specific type of acid buildup in the blood usually linked to toxins, severe infection, or metabolic disorders, rather than typical kidney tubular defects.
- Organic Acids: Chemical compounds that accumulated abnormally in the urine of these young patients, explaining the rare high anion gap component of their illness.
Clinical Profiles and Biochemical Findings in Pediatric Patients
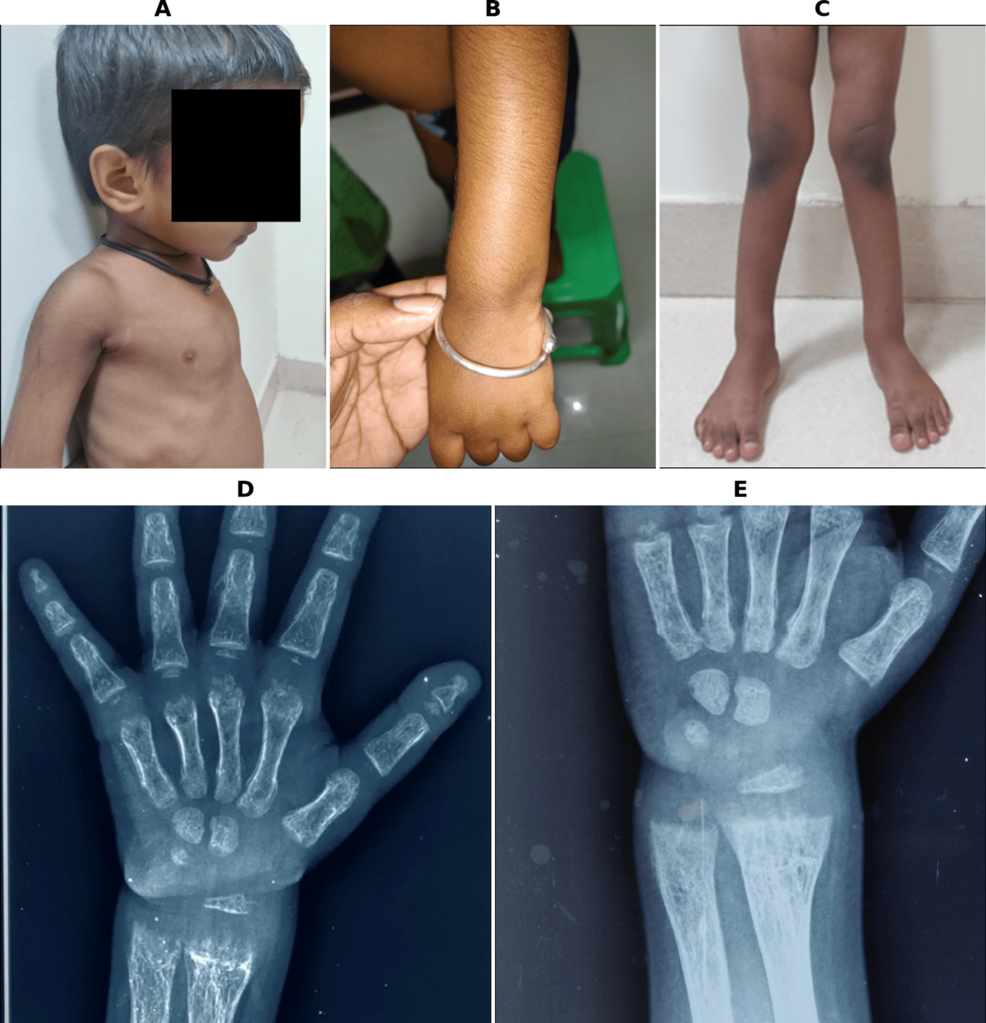
The first patient outlined in the Cureus report was a female child who presented with a one-year history of poor linear growth, weight stagnation, and bilateral wrist and ankle swelling. Despite receiving calcium and vitamin D supplementation for approximately one year, she showed no significant clinical improvement. Physical examination revealed significant growth retardation with a weight of 8.3 kilograms, frontal bossing, widened wrists, and genu valgum deformity. Radiographs confirmed active rickets with metaphyseal cupping, fraying, and splaying.
Arterial blood gas analysis for the first patient demonstrated a pH of 7.28, a bicarbonate level of 14 millimoles per liter, and an anion gap of 20 millimoles per liter, pointing clearly to HAGMA. Her urine pH remained inappropriately high at 8.0 despite systemic acidosis, accompanied by hypokalemia and hypercalciuria. Abdominal ultrasonography confirmed bilateral medullary nephrocalcinosis, which is the deposition of calcium in the renal medullary tissues.
The second patient, a five-year-and-seven-month-old female child, exhibited a similar presentation of delayed growth and bone deformities spanning three and a half years. She had a documented history of a lower-end left femur fracture and arm bending following trivial trauma six months prior to evaluation. Laboratory testing revealed a blood pH of 7.27, a bicarbonate level of 12.1 millimoles per liter, and an anion gap of 18.9 millimoles per liter. Urinary screening for both children ruled out common systemic causes of high anion gaps like lactic acidosis or ketoacidosis, instead uncovering elevated urinary organic acids.
| Clinical Parameter | Case 1 Baseline | Case 2 Baseline |
|---|---|---|
| Blood pH (7.35–7.45) | 7.28 | 7.27 |
| Bicarbonate (22–26 mmol/L) | 14 | 12.1 |
| Anion Gap (8–12 mmol/L) | 20 | 18.9 |
| Serum Potassium (3.5–5.2 mEq/L) | 2.6 | 2.8 |
Metabolic Intervention and Multi-Agent Treatment Protocol
Managing complex pediatric tubular disorders requires addressing both systemic acidity and underlying metabolic disruptions.
Historical context provided by a parallel review on renal transport mechanisms highlights that tracking acid-base regulation in these disorders builds on decades of renal physiology research. As early as 1935, researchers characterized calcium deposits in infant kidneys, while subsequent decades refined the classification of proximal and distal tubular defects.
Contraindications & When to Consult a Doctor
At the follow-up evaluation reported by Cureus, both pediatric patients demonstrated marked clinical recovery. Rachitic bone features improved visibly, and repeat radiographs showed clear resolution of metaphyseal and epiphyseal abnormalities.
References
- Cureus. Renal Tubular Acidosis With High Anion Gap: A Report of Two Cases.
- PubMed Central. Renal Tubular Acidosis: H+/Base and Ammonia Transport. PMC6128697.
