
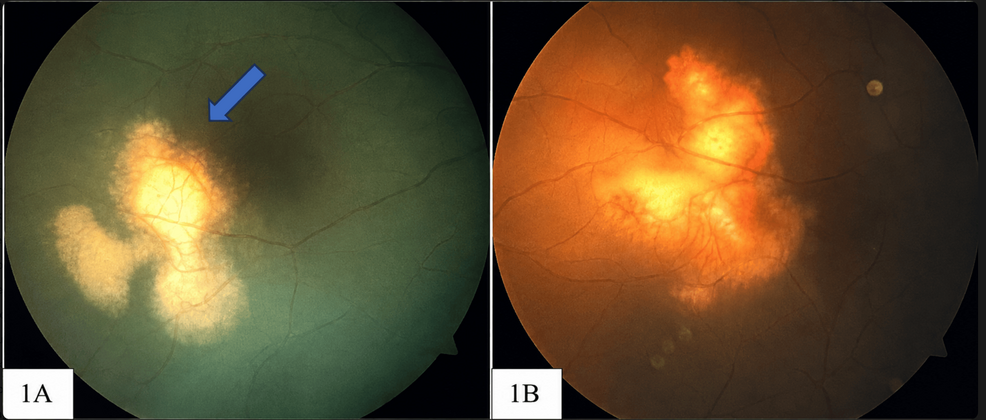
A 46-year-old male patient with advanced HIV and a history of recurrent tuberculosis developed progressive left eye blurring, pain, and redness. Initially diagnosed with cytomegalovirus retinitis and treated with intravenous ganciclovir, his condition worsened. A revised diagnosis of presumed ocular tuberculosis led to anti-tuberculous therapy, resulting in rapid lesion regression.
For clinicians managing severely immunocompromised patients, overlapping opportunistic infections present a profound diagnostic hazard. When standard antiviral regimens fail against rapidly expanding intraocular lesions, medical teams must re-evaluate baseline pathogen exposures. This case underscores how diagnostic ambiguity in ocular inflammation can delay life-saving therapies.
In Plain English: The Clinical Takeaway
- Contraindications: Specific medical conditions or factors that make a particular treatment or drug dangerous for a patient.
- Mechanism of Action: The exact biochemical process through which a drug produces its therapeutic effect in the body.
Diagnostic Complexities in Coexisting Systemic Infections
The patient presented to the hospital with disseminated cutaneous sporotrichosis, a subcutaneous fungal infection caused by Sporothrix species, alongside advanced human immunodeficiency virus infection with a critically low CD4 count of 6 cells/µL. While hospitalized, he developed progressive blurring of vision in the left eye over a two-week period. Initial ophthalmologic examination revealed grade 1+ inflammatory cells and multiple elevated yellow-white subretinal lesions nasal to the optic disc. Based on a positive cytomegalovirus polymerase chain reaction test (CMV PCR), clinicians initiated intravenous ganciclovir 250 mg twice daily. Instead of improving, his visual acuity deteriorated from 6/18 to 6/60 over six days, and the subretinal lesions enlarged and coalesced.
Concurrently, supplementary diagnostic evaluations revealed a strongly positive tuberculin skin test measuring 20 mm of induration, alongside a positive QuantiFERON-TB Gold assay. The patient had a documented history of pulmonary tuberculosis treated previously in 2014 and 2020, having completed six-month and one-year courses of anti-tuberculous therapy respectively. Due to the failure of antiviral therapy and the patient’s strong tuberculosis history, the clinical team abandoned the cytomegalovirus retinitis hypothesis. They revised the working diagnosis to presumed ocular tuberculosis.
Clinical Response to Anti-Tuberculous Therapy
Following consultation with the infectious diseases team, the patient was started on a multi-drug anti-tuberculous regimen consisting of once-daily rifabutin 300 mg, isoniazid 250 mg, pyrazinamide 1.2 g, ethambutol 1,000 mg, and pyridoxine 20 mg. Microbiological confirmation from ocular fluid sampling was deferred due to the patient’s poor general condition, meaning diagnosis relied entirely on clinical morphology, historical exposures, and treatment response. Two weeks after initiating the regimen, his left-eye visual acuity rebounded from 6/60 to 6/18, and further improved to 6/9 using pinhole correction. Fundus examinations confirmed marked anatomical regression, displaying flatter choroidal lesions with sharper margins and diminished vitritis.
| Treatment Phase | Primary Medication | Left-Eye Visual Acuity | Anatomical Outcome |
|---|---|---|---|
| Initial Presentation | Intravenous Ganciclovir | 6/18 deteriorating to 6/60 | Enlargement and coalescence of subretinal lesions |
| Revised Diagnosis | Rifabutin, Isoniazid, Pyrazinamide, Ethambutol | 6/60 improving to 6/9 | Marked regression of choroidal lesions and vitritis |
In parallel diagnostic contexts, intersecting systemic pathologies frequently confound medical evaluations. A case of systemic lupus erythematosus presenting with retinal vasculitis and chorioretinitis initially mimicked pulmonary tuberculosis and ocular tuberculosis. That patient received empiric anti-tubercular therapy and oral corticosteroids before worsening neuropsychiatric symptoms and positive anti-double-stranded DNA antibody panels confirmed neuropsychiatric systemic lupus erythematosus, necessitating a complete pivot in immunosuppressive management.
Future Trajectory of Ocular Tuberculosis Management
The convergence of advanced immunosuppression and latent bacterial reservoirs continues to challenge standard diagnostic algorithms in clinical practice. As demonstrated by these findings, maintaining a high index of suspicion remains critical even when patients have previously completed full courses of anti-tuberculous therapy. Future clinical protocols must balance the rapid initiation of targeted antimicrobials against the risks of overlapping opportunistic pathogens.
Disclaimer: This article is intended for informational and educational purposes only and does not substitute for professional medical advice, diagnosis, or treatment.
