
The case highlights how advanced metabolic bone disease can mimic skeletal malignancy in young adults.
Parathyroid Adenoma Causes Bone Breakdown and Superscans
- Parathyroid Adenoma: A benign, non-cancerous tumor on one of the parathyroid glands that overproduces parathyroid hormone (PTH), disrupting calcium and bone balance.
- Osteolytic Lesions and Superscan: Excessive PTH causes the body to break down bone rapidly, creating holes (lytic lesions) and an intensely bright bone scan (superscan) that can easily be mistaken for widespread cancer.
Uncovering Severe Primary Hyperparathyroidism Behind Unexplained Back Pain
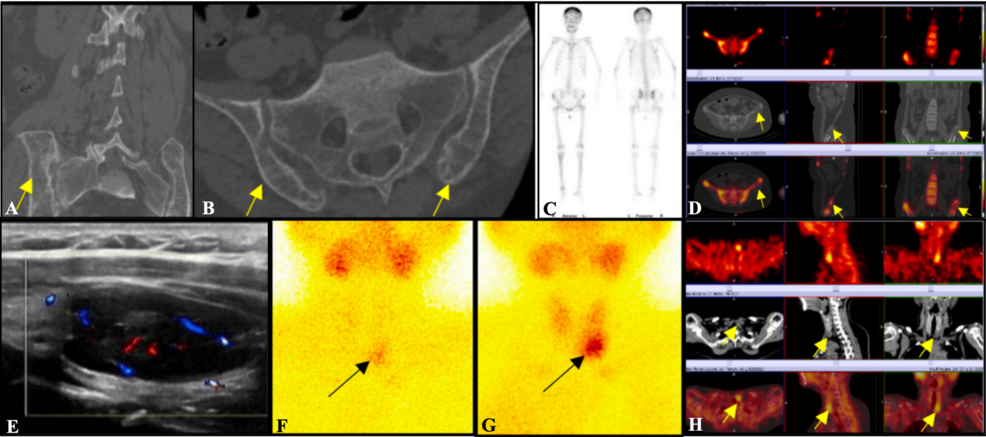
The patient sought care at an orthopedic department for persistent low back pain that had lasted for one year without any history of trauma. Initial lumbar computed tomography (CT) scans revealed multiple irregular osteolytic lesions involving the lumbar vertebrae, sacrum, and bilateral iliac bones. Because these bone defects resembled metastatic disease, clinicians initially considered malignancy in their differential diagnosis.
Subsequent biochemical evaluation shifted the clinical picture entirely. Laboratory tests showed a parathyroid hormone level of 1,807.3 pg/mL against a reference range of 12.4 to 76.8 pg/mL. Whole-body bone scintigraphy using technetium-99m methylene diphosphonate demonstrated a metabolic superscan, characterized by diffusely increased skeletal uptake and poor renal visualization. These findings confirmed that the structural bone damage stemmed from severe metabolic bone disease driven by parathyroid hormone excess rather than primary cancer.
Diagnostic Imaging and Surgical Localization of the Adenoma
To pinpoint the source of the excess hormone, the medical team utilized cervical color Doppler ultrasound and dual-phase single-tracer technetium-99m sestamibi scintigraphy combined with single-photon emission computed tomography/computed tomography (SPECT/CT). Ultrasound revealed a well-defined hypoechoic, hypervascular solid nodule measuring 2.84 by 1.29 centimeters posterior to the inferior pole of the left thyroid lobe. Sestamibi scans confirmed persistent focal uptake at the same site, which SPECT/CT localized precisely to a hyperfunctioning parathyroid adenoma.
The patient underwent surgical resection of the left inferior parathyroid gland alongside a bilateral partial thyroidectomy, which was required due to coexisting thyroid nodules identified on preoperative imaging. Histopathological analysis of the resected parathyroid tissue confirmed a neoplasm composed of chief cells, with no signs of significant atypia or mitotic activity.
| Biochemical Parameter | Patient Value | Reference Range |
|---|---|---|
| Parathyroid Hormone (PTH) | 1807.3 pg/mL | 12.4–76.8 pg/mL |
| Total Calcium | 3.06 mmol/L | 2.11–2.52 mmol/L |
| Phosphate | 0.56 mmol/L | 0.85–1.51 mmol/L |
| Alkaline Phosphatase (ALP) | 1489 U/L | 35–100 U/L |
Patient Develops Neuropsychiatric Episode During Follow-Up
By day 64, her PTH level rose while total calcium remained mildly depressed, though a neck ultrasound showed no sonographically evident residual parathyroid lesion.
Thirteen months after the operation, the patient experienced an acute neuropsychiatric episode characterized by incoherent speech and behavioral changes, leading to an outpatient psychiatric and neurologic evaluation. While the event occurred in the patient’s later follow-up timeline, no immediate biochemical testing was performed during that visit, leaving the precise physiological relationship between the episode and her prior primary hyperparathyroidism uncertain.
