Bundang CHA Medical Center has officially launched a cryoanalgesia program for thoracic procedures, utilizing extreme cold to interrupt intercostal nerve signaling. Clinical data show this targeted intervention reduces 48-hour postoperative pain scores by 44 percent compared to conventional management, helping patients breathe deeply and recover mobility without requiring continuous catheters.
In Plain English: The Clinical Takeaway
- What it is: Cryoanalgesia is a technique where surgeons apply extreme cold directly to the intercostal nerves—the nerves running between the ribs—inside the chest cavity to temporarily block pain signals.
- How long it lasts: The local nerve disruption typically provides sustained pain relief for two to three months, covering the most acute post-surgical recovery window.
- Patient benefit: Because it eliminates the need for a separate pain catheter and significantly lowers post-surgical pain scores, patients can cough, take deep breaths, and walk sooner.
Expanding Cryoanalgesia Across Major Thoracic Procedures
The Lung and Esophagus Center at Bundang CHA Medical Center announced the full-scale clinical deployment of cryoanalgesia for thoracic surgery patients. Severe pain following chest operations frequently restricts deep breathing, coughing, and early ambulation—vital movements that accelerate physical rehabilitation.
Dr. Gong-Min Im and clinical teams at the center have previously investigated various regional anesthetic modalities, including intercostal nerve blocks and serratus anterior plane blocks. Building on this extensive research into postoperative pain control, the center is now extending cryoanalgesia beyond pectus excavatum correction surgeries to selective applications in major thoracic procedures, including lung cancer and esophageal cancer resections.
According to findings published in the European Journal of Pediatric Surgery, a randomized clinical trial tracking 48 pectus excavatum patients demonstrated clear statistical advantages for the cold-based nerve interruption technique. Patients who received intraoperative cryoanalgesia reported a mean pain score of 3.17 at 48 hours post-surgery, compared to 5.67 in the conventional pain management control group—representing a 44 percent reduction in early postoperative discomfort.
Clinical Protocol Integration and International Collaboration
Unlike continuous epidural infusions or regional pain catheters that require ongoing clinical maintenance and site monitoring, cryoanalgesia is executed entirely during the primary operation. It can be used as a method of multi-modal pain management where clinicians utilize it alongside other pain control methods depending on the patient’s condition.
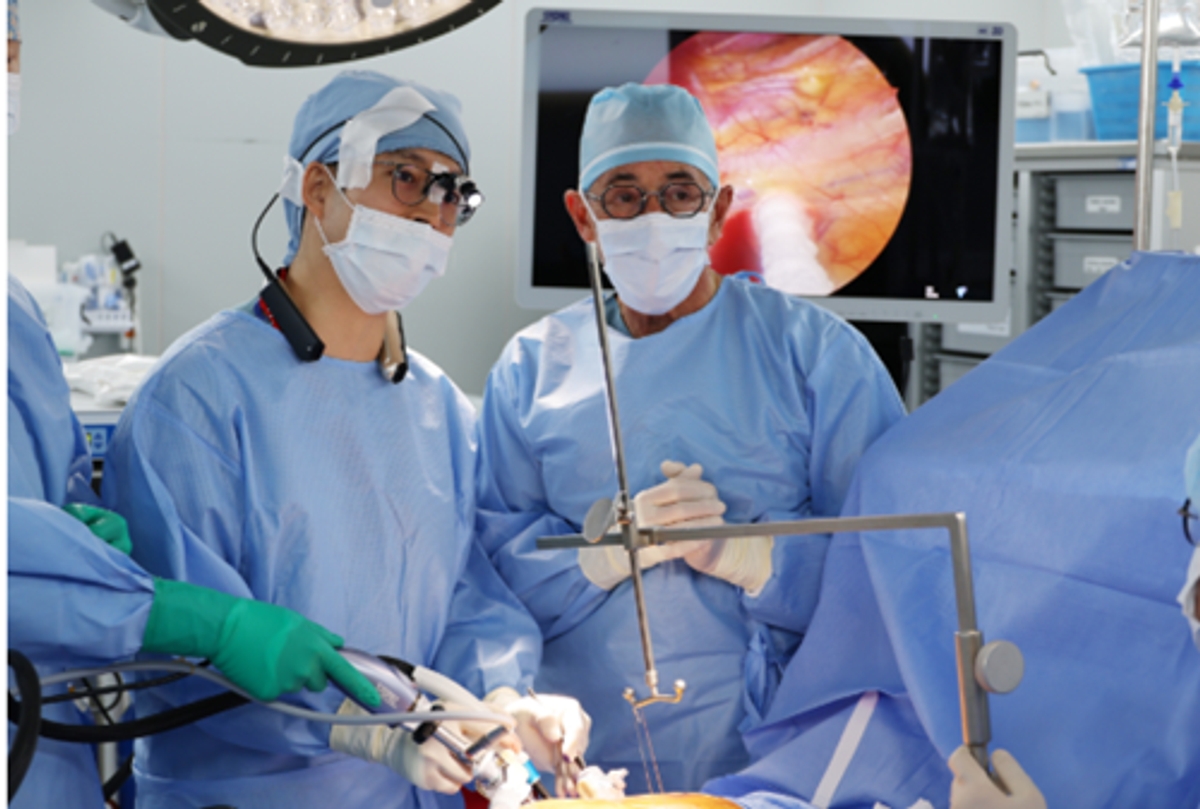
To refine patient selection and intraoperative technique, the Bundang CHA Medical Center center hosted U.S. thoracic surgeon Dr. Curtis C. Quinn for a dedicated collaborative program. Working alongside Dr. Im, Dr. Quinn participated in live surgical applications of the cryoanalgesia, sharing multidisciplinary expertise spanning patient candidacy assessments, precise intrathoracic nerve freezing maneuvers, and post-surgical pain management.
Medical teams emphasize that cryoanalgesia does not replace traditional systemic analgesics or localized nerve blocks entirely. Instead, clinicians utilize it as one method within a multi-modal analgesia framework tailored to individual patient physiologic responses and surgical parameters.
Toward Personalized Recovery Pathways
As thoracic surgery centers look beyond mere technical success toward functional recovery, minimizing opioid consumption and reducing early respiratory friction remain primary clinical objectives. By standardizing cryoanalgesia protocols for complex chest wall and oncological interventions, medical teams aim to streamline patient rehabilitation and mitigate the systemic side effects of high-dose narcotics during the critical post-surgical recovery phase.