
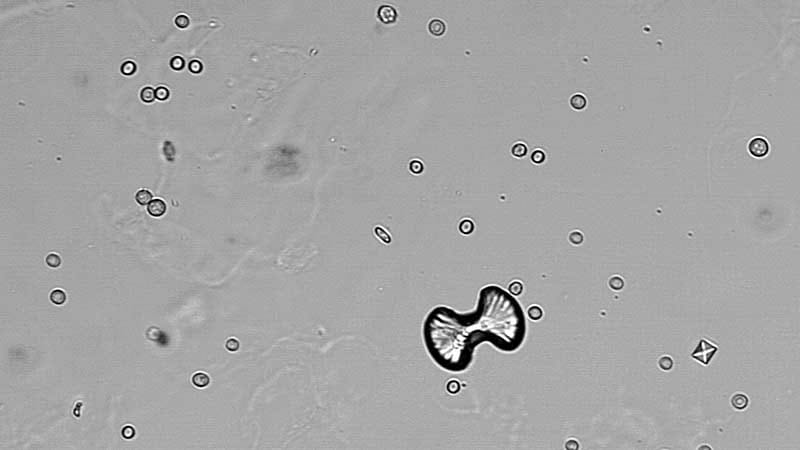
A 46-year-old patient with no history of kidney stones receives an elevated urine oxalate result from the portal, prompting her to compile a restrictive diet eliminating spinach and almonds while fearing stored oxalate “dumping.” This clinical scenario occurs amid rising traditional Medicare billing data for oxalate tests.
Billed tests for oxalate, or oxalic acid, in traditional Medicare climbed from roughly 46,800 in 2013 to about 69,900 in 2024, marking a 49% increase according to Centers for Medicare & Medicaid Services (CMS) figures. While raw volume has been roughly flat since 2019, Part B enrollment fell about 15% from 2019 to 2024 as beneficiaries transitioned to Medicare Advantage, driving the testing rate per enrollee from 1.4 per 1,000 in 2013 to two in 2019 and 2.5 in 2024.
Clinical Realities of Urine Oxalate Testing and Urinalysis
People without kidney stones typically do not get urine oxalate results. David Goldfarb, MD, professor of medicine and physiology at NYU Grossman School of Medicine and clinical chief of nephrology at NYU Langone Health in New York City, explained that measured urine oxalate comes from a 24-hour collection ordered to work up stones. Routine urinalysis frequently identifies calcium oxalate crystals in individuals without a history of stones, an unremarkable result that crystals alone do not mean disease.
When clinicians do order a 24-hour urine oxalate collection, laboratory reference ranges introduce critical variability. Mayo Clinic Laboratories utilizes a range of 9.7 to 40.5 mg per day for both sexes, whereas Labcorp establishes parameters at 4 to 31 mg per day for women and 7 to 44 mg per day for men. A female patient excreting 35 mg per day registers as high at one facility while remaining within normal limits at another. Furthermore, exogenous substances interfere with assay accuracy; Mayo Clinic instructs patients to avoid more than 2 g per day of vitamin C before and during collection to prevent falsely elevated measurements.
Unsubstantiated Functional Medicine Claims Versus Renal Dietetics
One commercial entity, Mosaic Diagnostics, advises cutting dietary oxalates gradually on its website to prevent alleged pain increases from oxalate “dumping.” Melanie Betz, MS, RD, a Chicago-based renal dietitian and founder of The Kidney Dietitian, dismissed oxalate dumping as a “false phenomenon.” Goldfarb characterized the use of functional medicine panels to assess clinical oxalate status as “very nonevidence-based.”
The 2026 American Urological Association (AUA) guideline addresses metabolic evaluations specifically for adult patients with verified stone histories, leaving an evidence gap for asymptomatic adults with elevated urinary excretion. Consequently, clinical assessment must prioritize medication and supplement histories. Betz and the AUA emphasize screening for vitamin C, herbal extracts, plant products, collagen, green superfood powders, turmeric, and cinnamon. Academic center case series show that dietary supplements accounted for 44% of oxalate nephropathy diagnoses between 2020 and early 2022, and cessation of the causative agent successfully improved renal parameters in eight of nine identified patients.
| Data Variable | Traditional Medicare Baseline (2013) | Traditional Medicare Recent Data (2024) |
|---|---|---|
| Billed Oxalate Tests | ~46,800 | ~69,900 |
| Testing Rate per 1,000 Enrollees | 1.4 tests | 2.5 tests |
| Part B Enrollment Trend | Higher baseline volume | Decreased 15% from 2019 peak |
Contraindications & When to Consult a Doctor
Patients must consult a qualified nephrologist or urologist before undertaking dietary modifications, particularly if they present with high-risk clinical markers. Individuals with a personal or familial history of nephrolithiasis, a history of bariatric procedures such as Roux-en-Y gastric bypass, inflammatory bowel disease, or unexplained chronic kidney disease (CKD) require formal metabolic workups rather than self-directed dietary restrictions. Betz cautions against blanket low-oxalate diets, noting they lack supportive trial data for stone recurrence prevention, restrict vital fiber and micronutrients, and remain exceptionally difficult for patients to maintain.
For confirmed elevations in urinary oxalate, clinical management mirrors stone prevention protocols. Experts recommend fluid intake sufficient to generate at least 2.5 liters of urine daily and maintaining normal dietary calcium consumption timed concurrently with meals. Calcium binds unabsorbed enteric oxalate in the gastrointestinal tract, preventing systemic absorption. Betz advises one serving of dairy or a calcium-fortified substitute per meal, which can successfully reduce elevated urine oxalate in approximately 90% of patients without enteric malabsorption. Supplemental vitamin C should be limited or avoided, as data from the Health Professionals Follow-up Study demonstrate a 43% higher risk of stone formation in men consuming 1,000 mg or more daily from food and supplements combined.
